Comprehensive Single-Cell Analysis of Colorectal Cancer Reveals Key Cellular and Molecular Alterations in the Tumor Microenvironment
This report details a single-cell RNA-seq analysis of human colon tissue, delineating profound changes in cellular composition, genomic integrity, and intercellular communication within colorectal cancer. UMAP visualizations show clear segregation of tumor versus adjacent normal cells and a strong association of aneuploidy with malignant Intestinal Epithelial cells. The tumor microenvironment is characterized by shifts in immune cell populations, notably an increase in immunosuppressive T cell subsets and specific pro-tumorigenic macrophage populations, along with extensive cell-cell interaction reprogramming. Key signaling pathways and surface markers identified in tumor cells, macrophages, and fibroblasts provide novel insights into disease progression and potential therapeutic avenues.
Contents
- Dataset overview
- UMAP Visualization of Colon Single-Cell RNA-seq Data by Condition, Sample, Cell Type, and Ploidy
- UMAP Visualization of Major Cell Type Scores, Ploidy Status, and Cell Type Annotations
- Marker Expression Dot Plot for Cell Subsets
- Genomic Copy Number Variation Analysis in Colorectal Intestinal Epithelial Cells
- CNV-Aware UMAP Visualization of Cell Type, Ploidy, Condition, and Sample Distribution in Colon Tissue
- Minor Cell Type Population Bar Plot Across Conditions
- T Cell and Innate Lymphoid Cell Subpopulation Analysis in Colorectal Cancer
- T Cell Subset Population Dynamics in Colorectal Cancer
- Macrophage Subset Population Dynamics in Colorectal Cancer
- Differential Macrophage Subpopulation Proportions in Colorectal Cancer
- Ploidy Status of Intestinal Epithelial Cells in Colorectal Cancer
- Analysis of Cell-Cell Interaction Patterns in Colorectal Cancer
- Cell-Cell Interaction Analysis of Immune Checkpoint and Cell Cycle Pathways in Colorectal Cancer
- Condition-Specific Cell-Cell Interaction Patterns in Colorectal Cancer
- Surfaceome Marker Expression in Intestinal Epithelial Cells of Colorectal Cancer
- Macrophage Condition-Specific Surfaceome Markers in Colorectal Cancer
- Fibroblast Condition-Specific Surfaceome Marker Expression in Colorectal Cancer
- T cell CD4+ Condition-Specific Surfaceome Marker Expression in Colorectal Cancer
- Analysis of Cell Cycle Pathway Gene Expression in Colorectal Cancer Intestinal Epithelial Cells
- Gene Ontology (GSA) Analysis of Intestinal Epithelial Cells in Colorectal Cancer
- Gene Set Enrichment Analysis Across Cell Types in Colorectal Cancer
- Discussion
- Query List
0. Dataset overview
데이터셋 요약
- 데이터 규모: 총 85,038개 세포와 27,779개 유전자를 포함합니다.
- 종 및 조직: 인간(human) 대장(Colon) 조직 데이터입니다.
- 조건: 'Tumor'(종양) 및 'Adj_normal'(인접 정상) 두 가지 조건이 분석에 사용되었습니다.
세포 유형:
- Major Celltypes: Intestinal Epithelial cell, Myeloid cell, T cell, Mast cell, B cell, Endothelial cell, Stromal cell 등 8가지 주요 세포 유형이 분류되어 있습니다.
- Minor Celltypes: Macrophage, T cell CD4+, Plasma cell, Fibroblast 등 13가지 세부 세포 유형이 분류되어 있습니다.
- Subset Celltypes: Enterocyte, Goblet cell, Macrophage (M1), T cell (Tfh), B cell (Follicular) 등 34가지 더 미세한 세포 아형이 분류되어 있습니다.
- 종양 세포 식별: 데이터셋에서 'Intestinal Epithelial cell'이 종양 기원 세포로 식별되었습니다.
염색체 이수성 (CNV 및 Ploidy):
- CNV(Copy Number Variation) 추정치가 사용 가능합니다.
- 세포의 약 13.4%가 이수성(Aneuploid)으로 관찰되었습니다.
- 'Adj_normal' 조건은 DEG, GSEA, GSA_up 분석의 참조 조건으로 사용됩니다.
사전 계산된 분석 결과
- 세포 간 상호작용 (CCI): 조건별 또는 샘플별 CellPhoneDB 결과가 저장되어 있습니다.
- 차등 발현 유전자 (DEG): 각 celltype_minor에서 한 조건을 다른 조건과 비교한 DEG 결과가 저장되어 있습니다.
- 유전자 세트 농축 분석 (GSEA): 각 celltype_minor에서 조건 간 비교를 수행한 GSEA 결과가 저장되어 있습니다.
- 유전자 온톨로지 (GSA_up): 각 celltype_minor에서 조건 간 비교를 수행한 GSA (GO) 결과가 저장되어 있습니다.
추론된 생물학적 맥락
- 이 데이터셋은 대장암(Colorectal Cancer) 연구와 관련된 것으로 추정됩니다. 이는 'Colon' 조직, 'Tumor' 및 'Adj_normal' 조건, 'TumorStage', 'MetastasisStatus' 등의 환자 관련 메타데이터, 그리고 이수성 세포의 존재 및 'Intestinal Epithelial cell'의 종양 기원 세포 지정 등을 바탕으로 추론되었습니다.
1. UMAP Visualization of Colon Single-Cell RNA-seq Data by Condition, Sample, Cell Type, and Ploidy
[Analysis Visualization Results]...
Analysis Overview
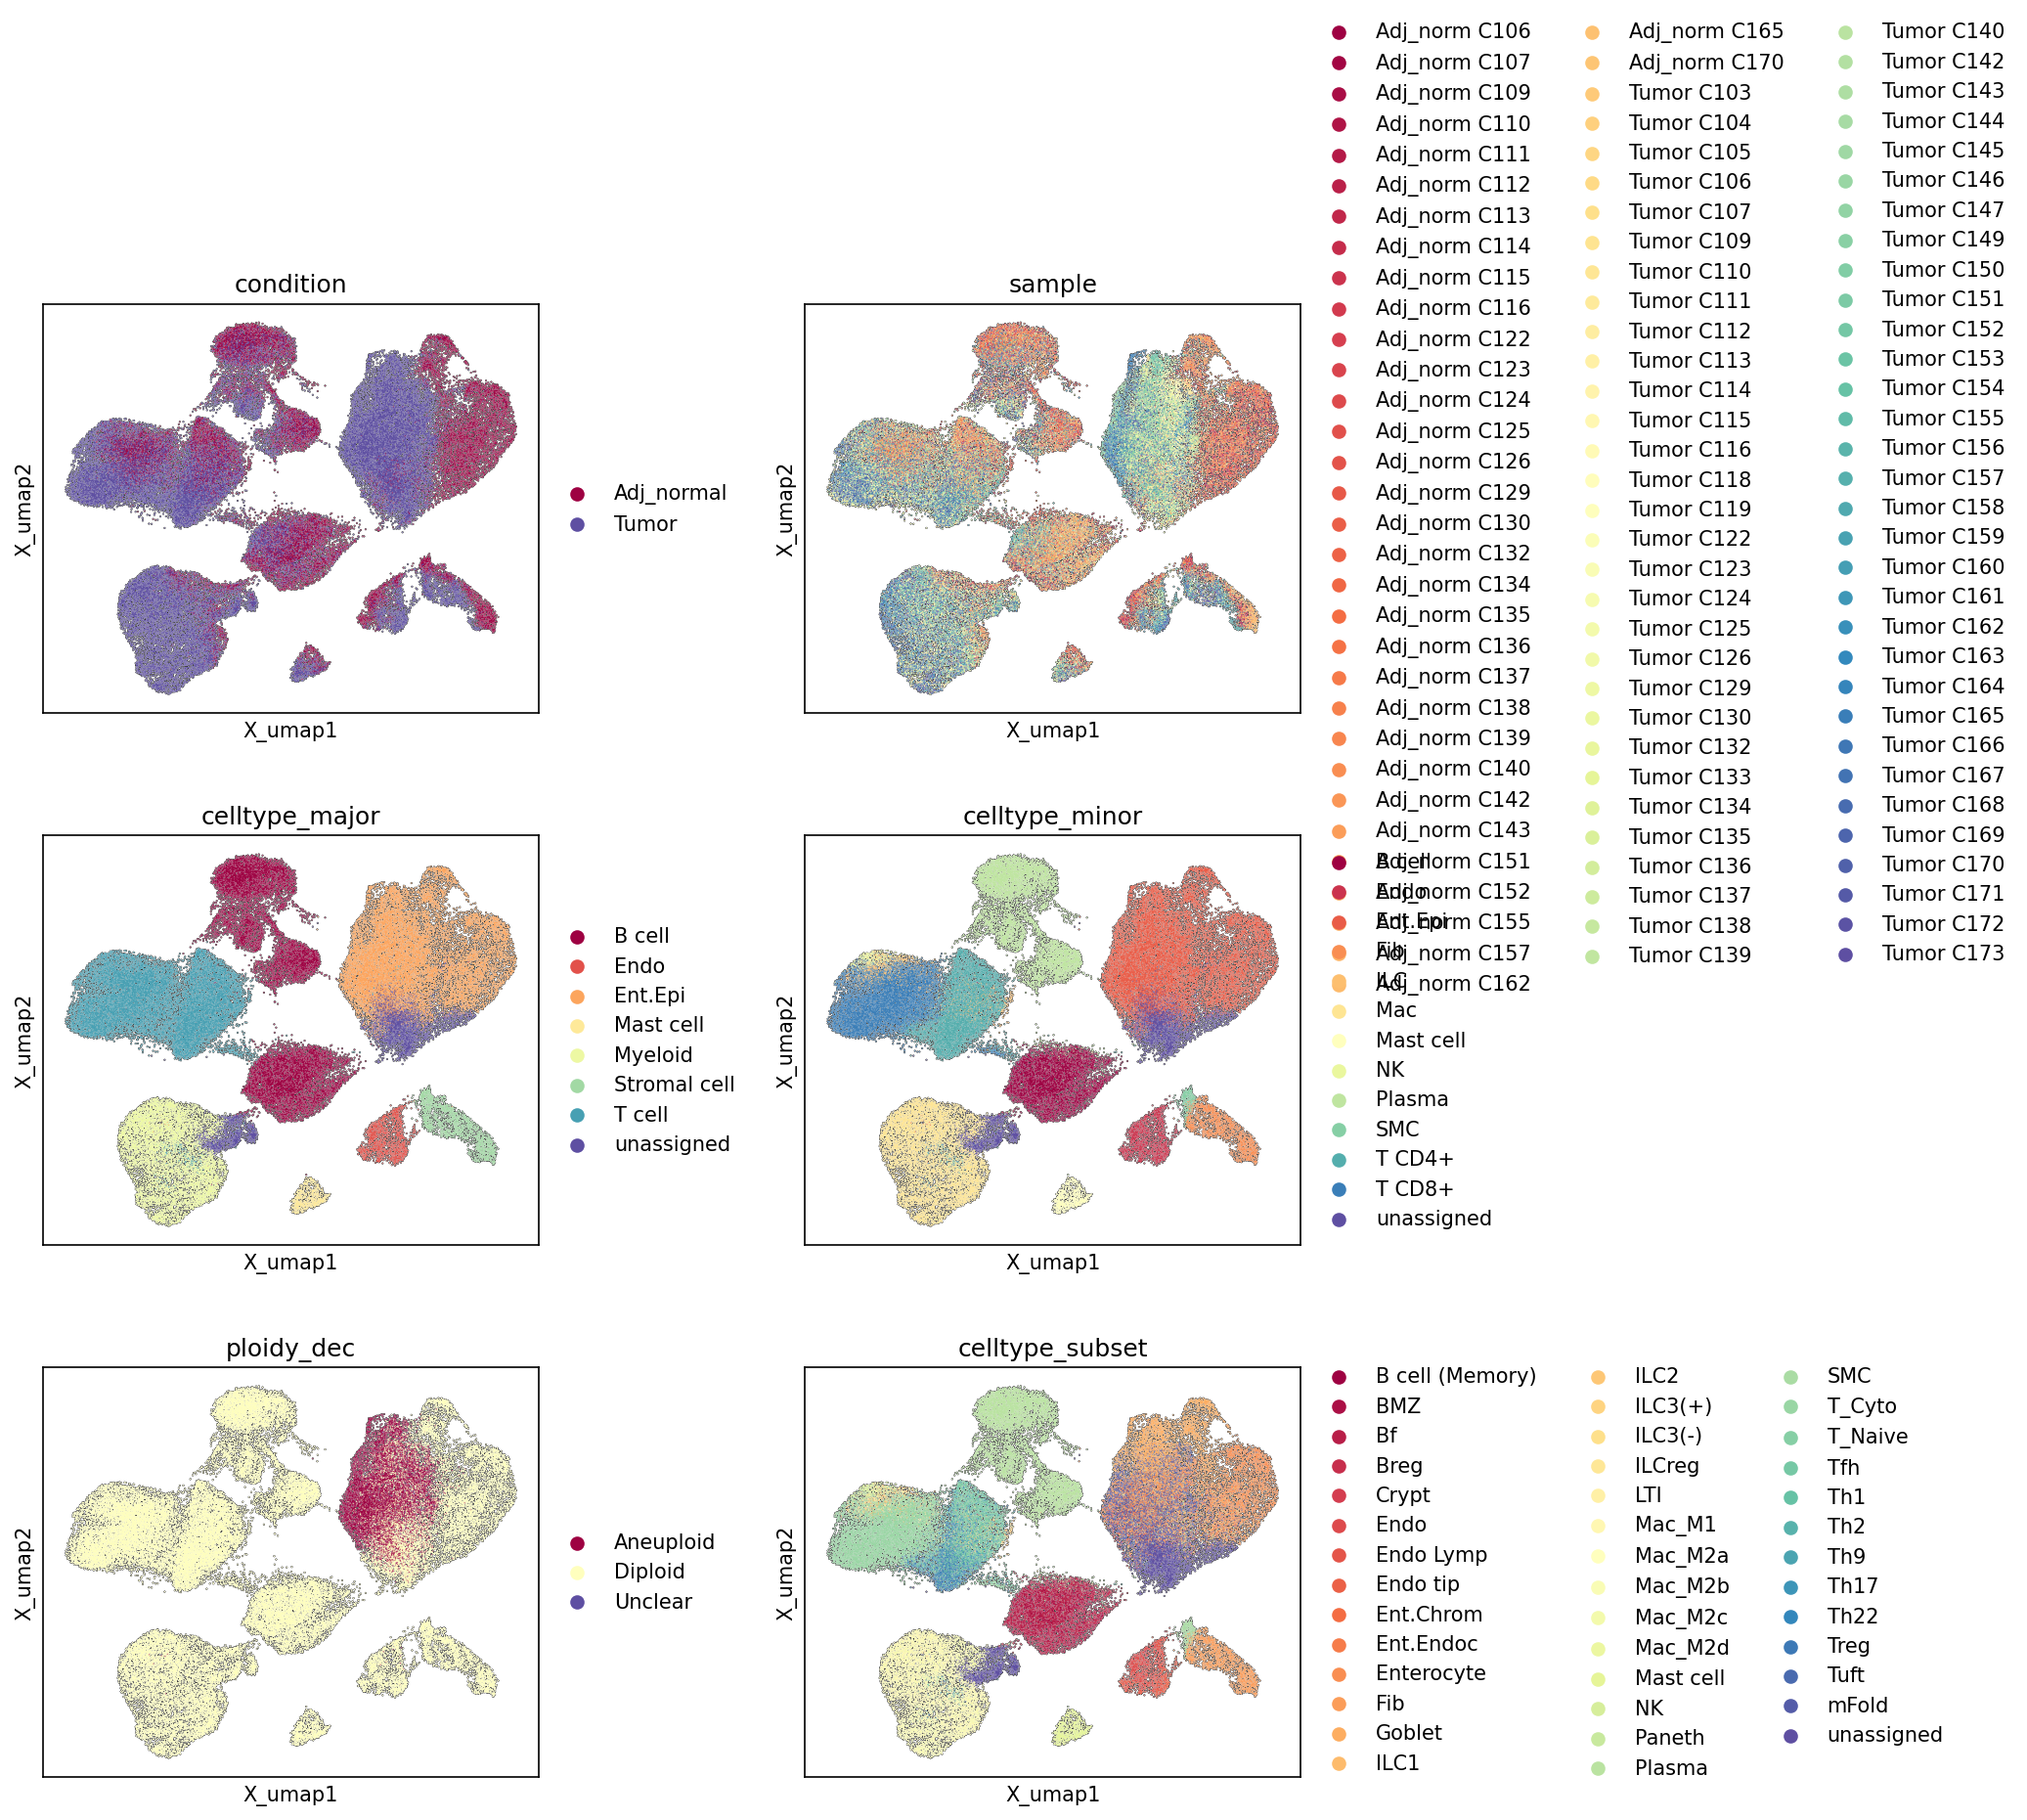
This analysis presents Uniform Manifold Approximation and Projection (UMAP) plots for single-cell RNA-sequencing data from colon tissue. These visualizations are colored by various metadata features: condition (Tumor vs. Adj_normal), sample (individual patient samples), celltype_major, celltype_minor, ploidy_dec (Aneuploid, Diploid, Unclear), and celltype_subset. The purpose is to evaluate the overall data structure, assess the quality of cell clustering and annotation, and reveal the distribution of different biological features across the cell landscape. The data is derived from human colon tissue, and the context strongly suggests the study of Colorectal Cancer.
Visual Summary
Condition
The UMAP colored by condition (Tumor vs. Adj_normal) reveals a striking separation between cells from tumor and adjacent normal tissues. The plot shows distinct clusters predominantly composed of either "Adj_normal" (e.g., the large cluster on the right) or "Tumor" cells (e.g., the large cluster in the top-middle/left). This clear segregation indicates significant transcriptional differences between cells originating from the tumor microenvironment compared to the healthy adjacent tissue.
Sample
When colored by individual sample, the UMAP displays a diverse distribution of colors across most major clusters. This intermingling of samples suggests that batch effects or sample-specific variations do not heavily dominate the overarching transcriptional landscape, indicating effective integration across different patient samples. While some small regions may show localized enrichment for specific samples, the overall impression is one of robust sample mixing, which is crucial for generalizing findings.
Cell Type (Major, Minor, Subset)
The UMAPs colored by celltype_major, celltype_minor, and celltype_subset demonstrate a hierarchical and biologically coherent clustering structure.
- Major Cell Types: Distinct clusters are observed for key cell populations such as "Intestinal Epithelial cell" (a large cluster on the right), "Myeloid cell", "T cell", "B cell", and "Stromal cell", indicating successful broad classification. "unassigned" cells form a noticeable cluster on the far left, suggesting populations requiring further investigation or potentially representing rare cell states.
- Minor and Subset Cell Types: As we move to celltype_minor and celltype_subset, the plots reveal more granular populations within the major clusters. For example, "T cell CD4+" and "T cell CD8+" are clearly resolved from the broader "T cell" cluster, and various epithelial cell types (e.g., "Enterocyte", "Goblet cell", "Crypt cell") and immune cell subtypes (e.g., "Macrophage (M1/M2A/M2B/M2C/M2D)", specific T helper and regulatory T cell subtypes) form identifiable sub-clusters. The presence of the "unassigned" group persists across all levels of cell type annotation, indicating a subset of cells whose identity remains ambiguous.
Ploidy Status
The UMAP colored by ploidy_dec provides critical insights into the genomic stability of the cells. "Diploid" cells (yellow) are widely distributed across the manifold, particularly enriched in regions corresponding to "Adj_normal" tissue and "Intestinal Epithelial cell" clusters. In stark contrast, "Aneuploid" cells (maroon) primarily localize to specific clusters that largely overlap with the "Tumor" condition and specific "Intestinal Epithelial cell" populations. This strong association of aneuploidy with the tumor compartment is a hallmark of malignancy. "Unclear" cells are sparsely scattered.
Biological Interpretation
The UMAP plots provide a foundational overview of the cellular heterogeneity in colon tissue, particularly highlighting the dramatic changes associated with colorectal cancer.
- Tumor Microenvironment Remodeling: The clear separation of "Tumor" and "Adj_normal" cells in the condition UMAP underscores the extensive transcriptional alterations occurring in the cancerous state. This indicates a profound reprogramming of the cellular landscape in the presence of malignancy, affecting both epithelial cells and components of the tumor microenvironment (TME).
- Identification of Malignant Cells: The ploidy_dec UMAP is particularly informative. The strong co-localization of "Aneuploid" cells with the "Tumor" condition and the "Intestinal Epithelial cell" cluster strongly supports the identification of these aneuploid epithelial cells as the primary malignant population. This aligns with the resolved tumor-origin cell type: Intestinal Epithelial cell and the common understanding that colorectal carcinomas originate from epithelial cells that accumulate genomic instability, leading to aneuploidy. GeneCards: Colorectal Neoplasms
- Immune Cell Infiltration and Heterogeneity: The detailed celltype_minor and celltype_subset UMAPs reveal the rich diversity of immune cells (T cells, B cells, macrophages) within the tissue. Their distribution relative to the tumor and normal compartments can indicate aspects of the immune response to cancer, such as the presence of different macrophage polarization states (M1 vs. M2 subtypes), T cell activation states, or immunosuppressive populations (e.g., regulatory T cells, Tregs) within the tumor microenvironment.
- Stromal Contribution to Tumor: The presence and clustering of "Stromal cell" populations (Fibroblasts, Smooth muscle cells, Endothelial cells) suggest their role in shaping the tumor architecture and influencing tumor progression. Their specific localization within the UMAP, particularly relative to the tumor clusters, could hint at tumor-associated stromal remodeling.
Annotation Notes
- Robust Clustering: The consistent clustering patterns observed across different levels of cell type annotation (major, minor, subset) suggest a robust underlying transcriptional structure in the dataset, supporting the quality of the cell type assignments.
- Batch Effect Mitigation: The effective mixing of samples across the UMAP indicates successful integration of data from multiple individuals, minimizing the confounding effects of inter-sample variability on the major biological groupings.
- Unassigned Populations: The persistent presence of an "unassigned" cell cluster across different annotation levels highlights populations that may require further in-depth characterization. These could represent novel cell states, rare cell types, or cells with challenging or ambiguous transcriptional profiles. Future analyses could focus on deconvoluting these unassigned populations to fully understand the cellular landscape.
2. UMAP Visualization of Major Cell Type Scores, Ploidy Status, and Cell Type Annotations
[Analysis Visualization Results]...
Analysis Overview
This analysis presents several UMAP (Uniform Manifold Approximation and Projection) plots, which visualize the single-cell RNA-seq data in a lower-dimensional space. The plots display:
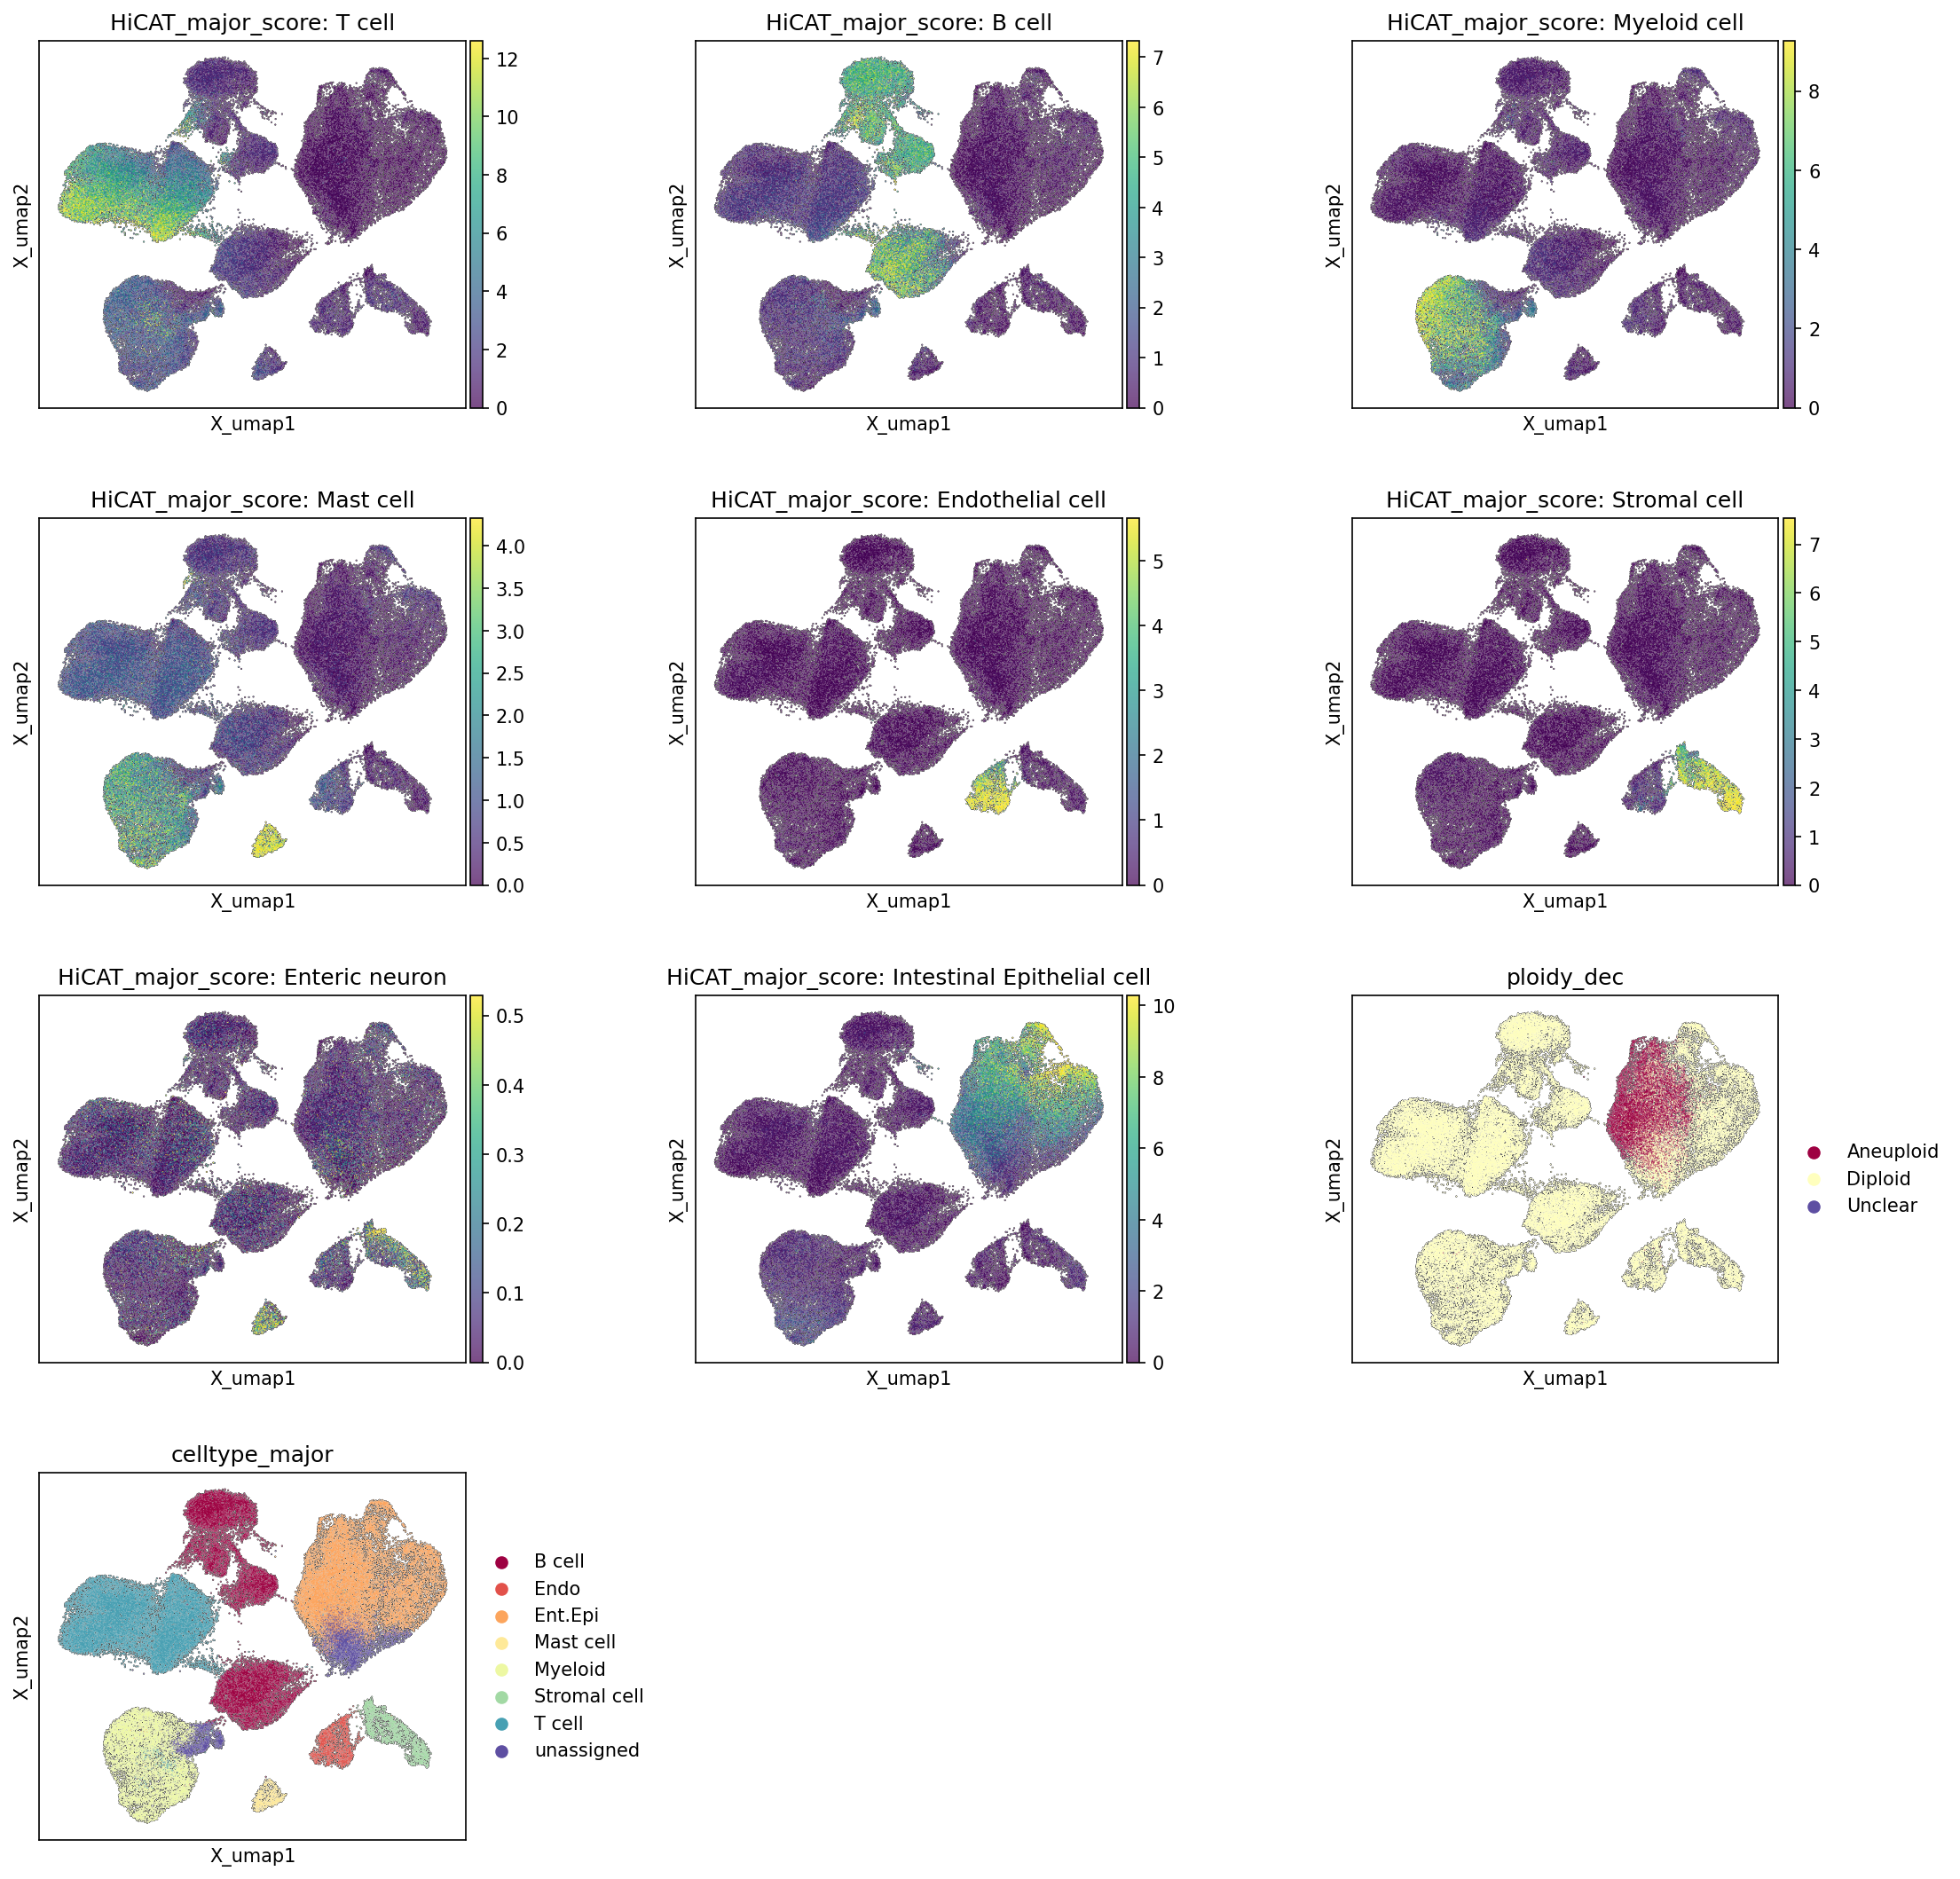
- Major Cell Type Scores: Individual plots show the confidence score (HiCAT_major_score) for each cell belonging to a specific major cell type (T cell, B cell, Myeloid cell, Mast cell, Endothelial cell, Stromal cell, Enteric neuron, Intestinal Epithelial cell). Higher scores (yellow/light green) indicate stronger confidence in the cell's assignment to that type.
- Ploidy Status: A UMAP colored by ploidy_dec (ploidy decision) categorizes cells as Aneuploid, Diploid, or Unclear. Aneuploidy is a hallmark of cancer cells.
- Major Cell Type Annotation: A final UMAP colored by the celltype_major annotation, showing the assigned identity for each cell.
The purpose of these visualizations is to assess the quality of cell type annotation, confirm distinct clustering of cell populations, and investigate the spatial relationship between specific cell types (especially Intestinal Epithelial cells) and aneuploid status within the UMAP embedding.
Visual Summary
Major Cell Type Score UMAPs:
- T cell: Shows a distinct cluster with high scores (yellow) predominantly on the left side of the UMAP embedding, indicating a well-separated population.
- B cell: Displays high scores in a cluster located in the upper-left region, distinct from the T cell cluster.
- Myeloid cell: Exhibits high scores in a broad cluster in the lower-left region of the UMAP, separate from T and B cells.
- Mast cell: Shows a smaller, more diffuse region of high scores, mostly within the myeloid cell cluster or adjacent to it.
- Endothelial cell: Forms a relatively compact cluster with high scores in the central-right part of the UMAP.
- Stromal cell: Shows a distinct cluster with high scores towards the lower-right side of the UMAP.
- Enteric neuron: Displays very low scores across the UMAP (max ~0.5), suggesting this cell type is either very rare or not well-represented by specific markers in this dataset for a major cell type assignment.
- Intestinal Epithelial cell: Forms a large, prominent cluster with high scores in the upper-right quadrant of the UMAP. This cluster appears to be heterogeneous in terms of score intensity.
Ploidy Status UMAP (ploidy_dec):
- Aneuploid cells (red) are primarily localized to a distinct large cluster within the upper-right region of the UMAP.
- Diploid cells (light yellow) make up the vast majority of the remaining cells, occupying most of the other cell type clusters.
- Unclear cells (purple) are very sparse and scattered, indicating a low number of ambiguous ploidy calls.
Major Cell Type Annotation UMAP (celltype_major):
- This plot consolidates the cell type assignments. Distinct, well-separated clusters are observed for B cells (red, upper-left), Endothelial cells (orange, central-right), Intestinal Epithelial cells (light orange, upper-right), Mast cells (yellow, lower-left within myeloid), Myeloid cells (light green, lower-left), Stromal cells (dark green, lower-right), T cells (light blue, left), and a minor 'unassigned' population (purple, scattered).
- The locations of the celltype_major clusters align very well with the regions of high scores observed in the individual HiCAT_major_score plots for each corresponding cell type.
Biological Interpretation
The UMAP visualizations provide a clear landscape of the cellular heterogeneity within the human colon tissue samples, differentiating between Tumor and Adj_normal conditions, which is consistent with the inferred Colorectal Cancer context.
- Robust Cell Type Identification: The distinct clustering and high confidence scores for major cell types like T cells, B cells, Myeloid cells, Endothelial cells, Stromal cells, and Intestinal Epithelial cells suggest a robust and accurate cell type annotation. Each major cell type forms a largely contiguous region in the UMAP, indicating good separation of transcriptomically distinct populations. This robust annotation is crucial for downstream differential expression and pathway analyses.
- Identification of Malignant Epithelial Cells: The ploidy_dec UMAP shows a prominent cluster of aneuploid cells specifically localized to the region occupied by Intestinal Epithelial cells. This observation strongly supports the resolution of "Intestinal Epithelial cell" as the tumor-origin cell type, as cancer cells are frequently characterized by aneuploidy. The clear segregation of aneuploid cells within the epithelial compartment helps delineate the tumor epithelial cells from non-malignant epithelial cells (potentially from adjacent normal tissue). This segregation is a critical step in isolating and characterizing the true tumor compartment.
- Composition of the Tumor Microenvironment: The presence of diverse immune cells (T cells, B cells, Myeloid cells, Mast cells), stromal cells (Fibroblasts, Smooth muscle cells implied by 'Stromal cell' major type), and Endothelial cells, alongside the Intestinal Epithelial cells, highlights the complexity of the colorectal cancer tumor microenvironment. Each of these cell types plays a critical role in tumor progression, immune response, and therapeutic resistance. For example, Myeloid cells, particularly Macrophages, are known to be highly plastic and contribute to pro- or anti-tumor immunity in CRC, depending on their polarization (e.g., M1 vs. M2).
- Minor Cell Populations/Unassigned Cells: The low scores for 'Enteric neuron' suggest this population is either very rare in these samples or its transcriptomic profile is not strongly represented by the chosen markers, leading to its absence as a major identified cluster. The 'unassigned' cluster might represent cells with ambiguous profiles, technical artifacts, or rare cell types not well-captured by the major categories.
Annotation Notes
- The consistency between individual HiCAT_major_score plots and the aggregated celltype_major UMAP indicates high confidence in the automated cell type assignments. The algorithms correctly identify and cluster cells based on their transcriptomic profiles.
- The clear visual distinction between aneuploid cells and diploid cells, with aneuploid cells predominantly co-localizing with Intestinal Epithelial cells, serves as strong validation for the identification of tumor cells within the dataset. This is a critical step for accurately studying tumor-specific biology.
- The dataset exhibits good coverage of the major cell types expected in the colon and its associated tumor microenvironment, supporting comprehensive downstream analyses.
- Further investigation of the 'unassigned' cells might be warranted if they represent a substantial population, to determine if they contain novel or poorly characterized cell types.
3. Marker Expression Dot Plot for Cell Subsets
[Analysis Visualization Results]...
Analysis Overview
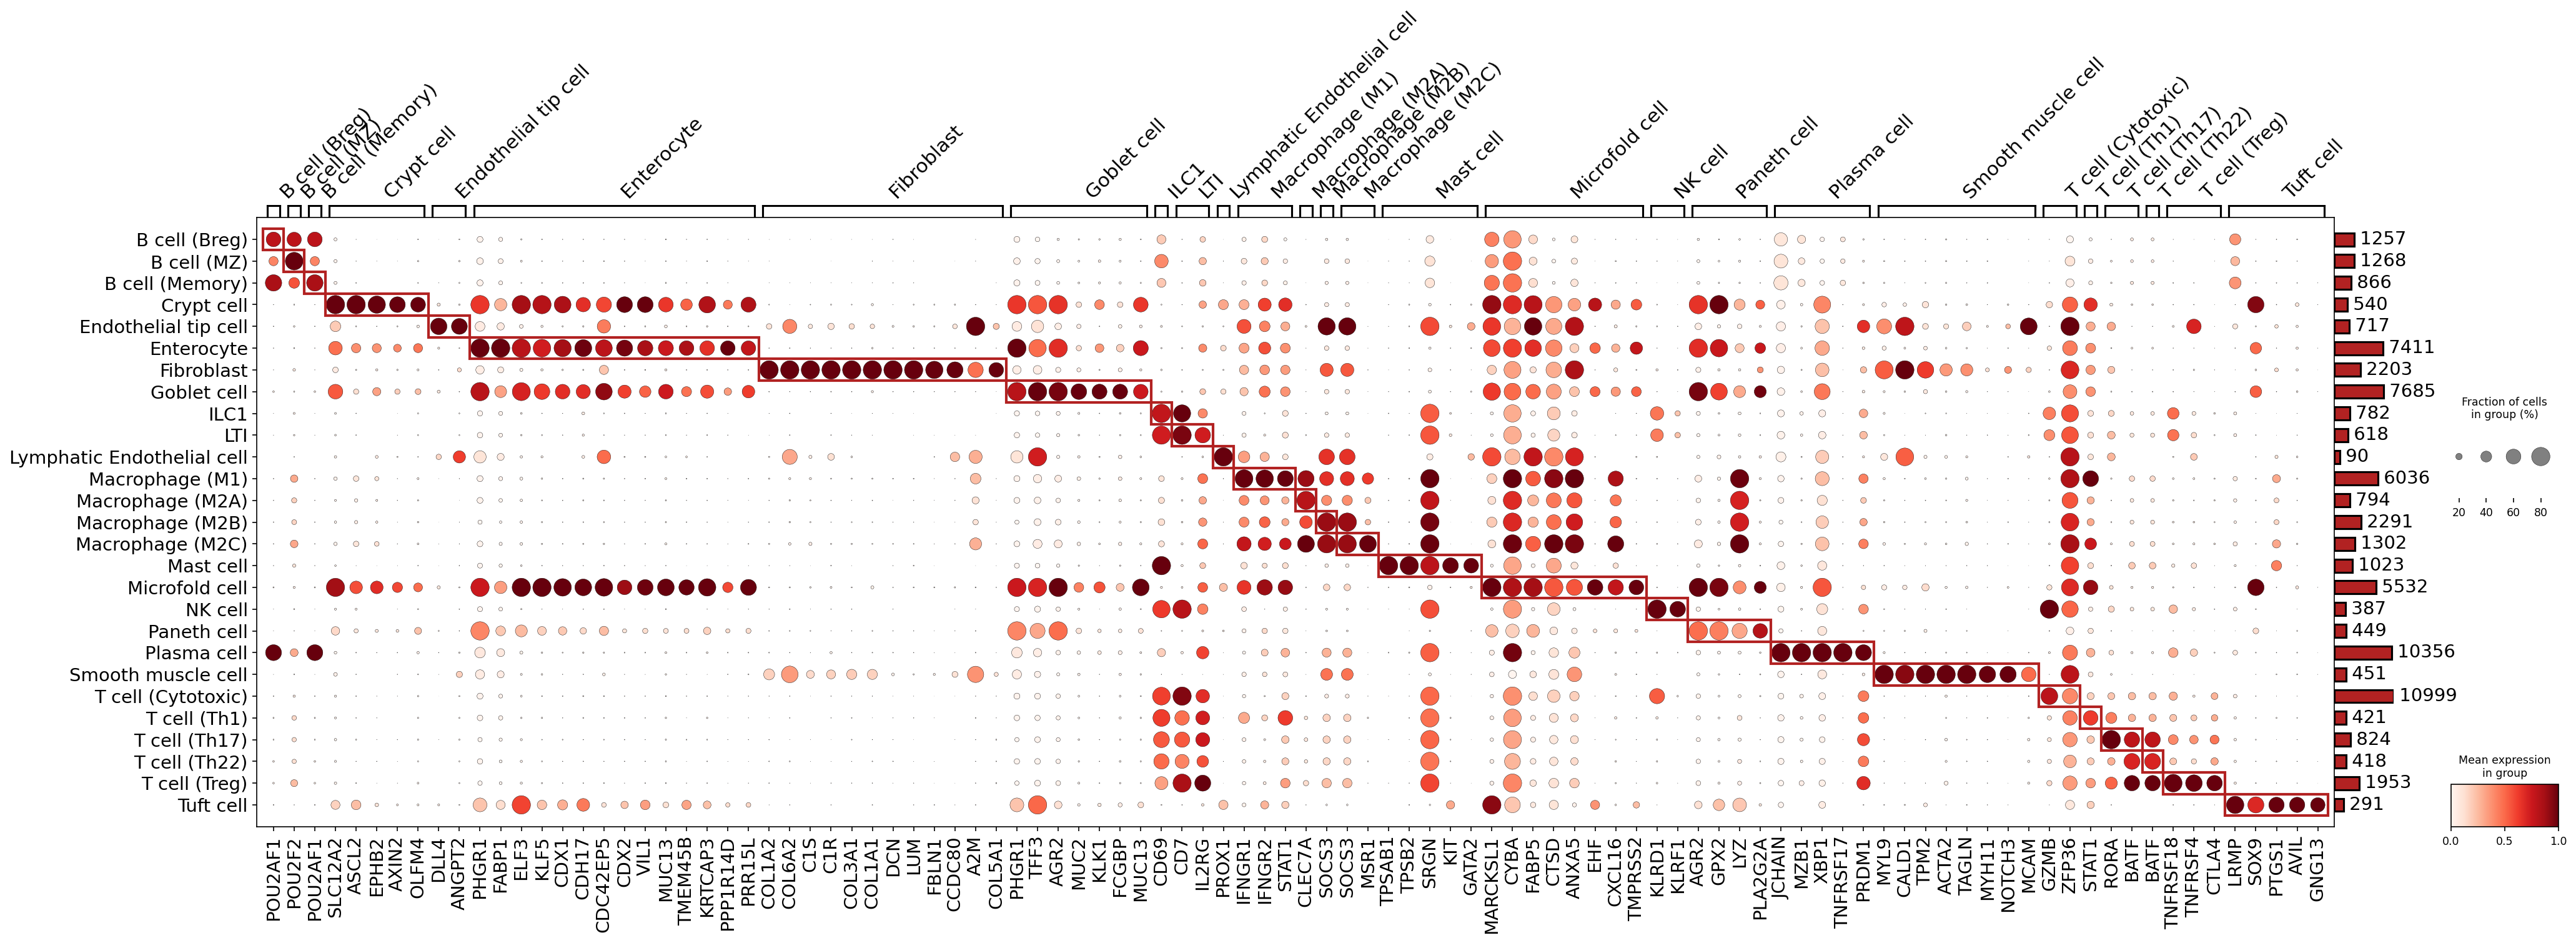
This analysis presents a dot plot illustrating the expression of marker genes across different cell subsets (celltype_subset) identified in the single-cell RNA-seq data from human colon tissue. The plot serves as a critical step in validating cell type annotations by visualizing the specificity and expression levels of known or computationally derived marker genes within each cellular population. This helps confirm whether the assigned cell identities are supported by characteristic gene expression profiles.
Visual Summary
The dot plot displays cell types (celltype_subset) on the y-axis and marker genes on the x-axis. Each dot represents the expression of a specific gene within a particular cell type:
- Dot size indicates the percentage of cells within that celltype_subset that express the gene (fraction of cells in group). Larger dots signify a higher proportion of expressing cells.
- Dot color intensity (ranging from light red to dark red) reflects the mean expression level of the gene in that cell type. Darker red indicates higher average expression.
- Genes are grouped by the celltype_subset they primarily mark, and these groups are visually delimited by horizontal red rectangles, highlighting distinct marker signatures for each cell type.
- A bar chart on the right side indicates the total number of cells within each celltype_subset, providing context on the size of each population.
- The x-axis labels (gene symbols) are rotated by 45 degrees for readability, as specified by the var_group_rotation parameter.
Biological Interpretation
The dot plot reveals distinct and largely specific marker gene expression patterns across the various celltype_subset categories, providing strong support for the current cell type annotations.
Key observations by cell type group include:
- B cells: POU2AF1, POU2F2, CD79A, and MZB1 show highly specific and strong expression across B cell subsets (B cell (Breg), B cell (MZ), B cell (Memory)), consistent with their roles in B cell development and function. TNFRSF17 (BCMA), critical for plasma cell survival, is also observed in B cell (Memory) and Plasma cells, which aligns with the continuum of B cell differentiation.
Intestinal Epithelial cells:
- Crypt cells are characterized by markers like ASCL2, EPHB2, AXIN2, OLFM4, and DLL4, which are known components of the Wnt signaling pathway and are crucial for intestinal stem cell maintenance and proliferation in the crypts.
- Enterocytes display robust expression of FABP1, KLF5, CDX1, CDH17, CDC42EP5, CDX2, VIL1, TMEM45B, KRTAP3, and PPP1R14D, consistent with their absorptive functions and differentiation state. CDX1 and CDX2 are important caudal-related homeobox transcription factors regulating intestinal development and differentiation.
- Goblet cells are clearly identified by high expression of MUC2 (a major mucin component) and TFF3 (trefoil factor 3), both vital for mucus production and barrier function.
- Paneth cells show very strong and specific expression of LYZ (lysozyme), a key antimicrobial peptide produced by these cells.
- Tuft cells exhibit markers such as SOX9, PTGS1, AVIL, and GNG13, reflecting their chemosensory and immune-modulatory roles.
- Fibroblasts: These stromal cells are distinctly marked by high expression of extracellular matrix components like COL3A1, COL1A1, COL1A2, COL6A2, and DCN (decorin), along with LUM (lumican), supporting their role in tissue structure and remodeling.
Endothelial cells:
- Endothelial tip cells show markers like ANGPT2 (angiopoietin 2) and PHGR1, involved in angiogenesis.
- Lymphatic Endothelial cells are specifically identified by PROX1, a canonical master regulator of lymphatic endothelial cell identity [1]. The expression of IL2RG is also noted here, though less specific as it's typically associated with lymphocyte signaling.
- Myeloid cells (Macrophages): Macrophage subsets (M1, M2A, M2B, M2C) display a shared expression of typical macrophage markers such as MSR1 (macrophage scavenger receptor 1), A2M (alpha-2-macroglobulin), CTSD (cathepsin D), FABP5 (fatty acid binding protein 5), ANXA5 (annexin A5), MARCKSL1, CYBA, and EHF. While some of these are pan-macrophage markers, the specific combinations and intensities may hint at functional polarization within the different M1/M2 subtypes.
- Mast cells: KIT (stem cell factor receptor), TPSAB1 (tryptase alpha/beta 1), and SRGN (serglycin) are highly specific markers, confirming the identity of mast cells involved in immune responses and inflammation.
- NK cells: KLRD1 (CD94) and KLRF1 (NKG2D) are expressed specifically in NK cells, consistent with their cytotoxic functions.
- Plasma cells: JCHAIN (joining chain of immunoglobulins), XBP1 (X-box binding protein 1), PRDM1 (BLIMP1), and TNFRSF17 (BCMA) are key markers for terminally differentiated B cells that secrete antibodies.
- Smooth muscle cells: ACTA2 (alpha-smooth muscle actin), TAGLN (transgelin), MYH11 (myosin heavy chain 11), NOTCH3, MCAM, MYL9, TPM2, and CALD1 (caldesmon 1) are all characteristic markers for smooth muscle, indicating their contractile and structural roles.
T cells:
- T cell (Cytotoxic) shows strong expression of GZMB (granzyme B), a primary effector molecule in cytotoxic T lymphocyte-mediated killing.
- Various T cell subsets (Th1, Th17, Th22, Treg) show expression of CD69 (early activation marker), CD7, and transcription factors or receptors such as STAT1, RORA, BATF, TNFRSF18 (GITR), CTLA4, and TNFRSF4 (OX40). The presence of CTLA4 and TNFRSF18 in T cell (Treg) is particularly notable, as these are crucial for Treg suppressive functions [2].
Overall, the observed marker gene expression patterns are highly consistent with the known biology of the assigned celltype_subset annotations for colon tissue, reinforcing the quality and reliability of the single-cell clustering and labeling.
Annotation Notes
The dot plot strongly validates the current celltype_subset annotations. The identified marker genes largely correspond to well-established markers for these cell types in the human colon, confirming the accuracy of the cell identity assignments. The distinct expression profiles for each subset, characterized by high specificity and robust expression levels (dark, large dots), suggest that the resolution of cell types is appropriate and biologically meaningful. No significant inconsistencies or misattributions were immediately apparent from this marker analysis.
---
References:
[1] PROX1 (PubMed search): https://pubmed.ncbi.nlm.nih.gov/?term=PROX1+lymphatic+endothelial+marker
[2] CTLA4 and TNFRSF18 (GITR) in T regulatory cells (PubMed search): https://pubmed.ncbi.nlm.nih.gov/?term=CTLA4+TNFRSF18+Treg
4. Genomic Copy Number Variation Analysis in Colorectal Intestinal Epithelial Cells
[Analysis Visualization Results]...
Analysis Overview
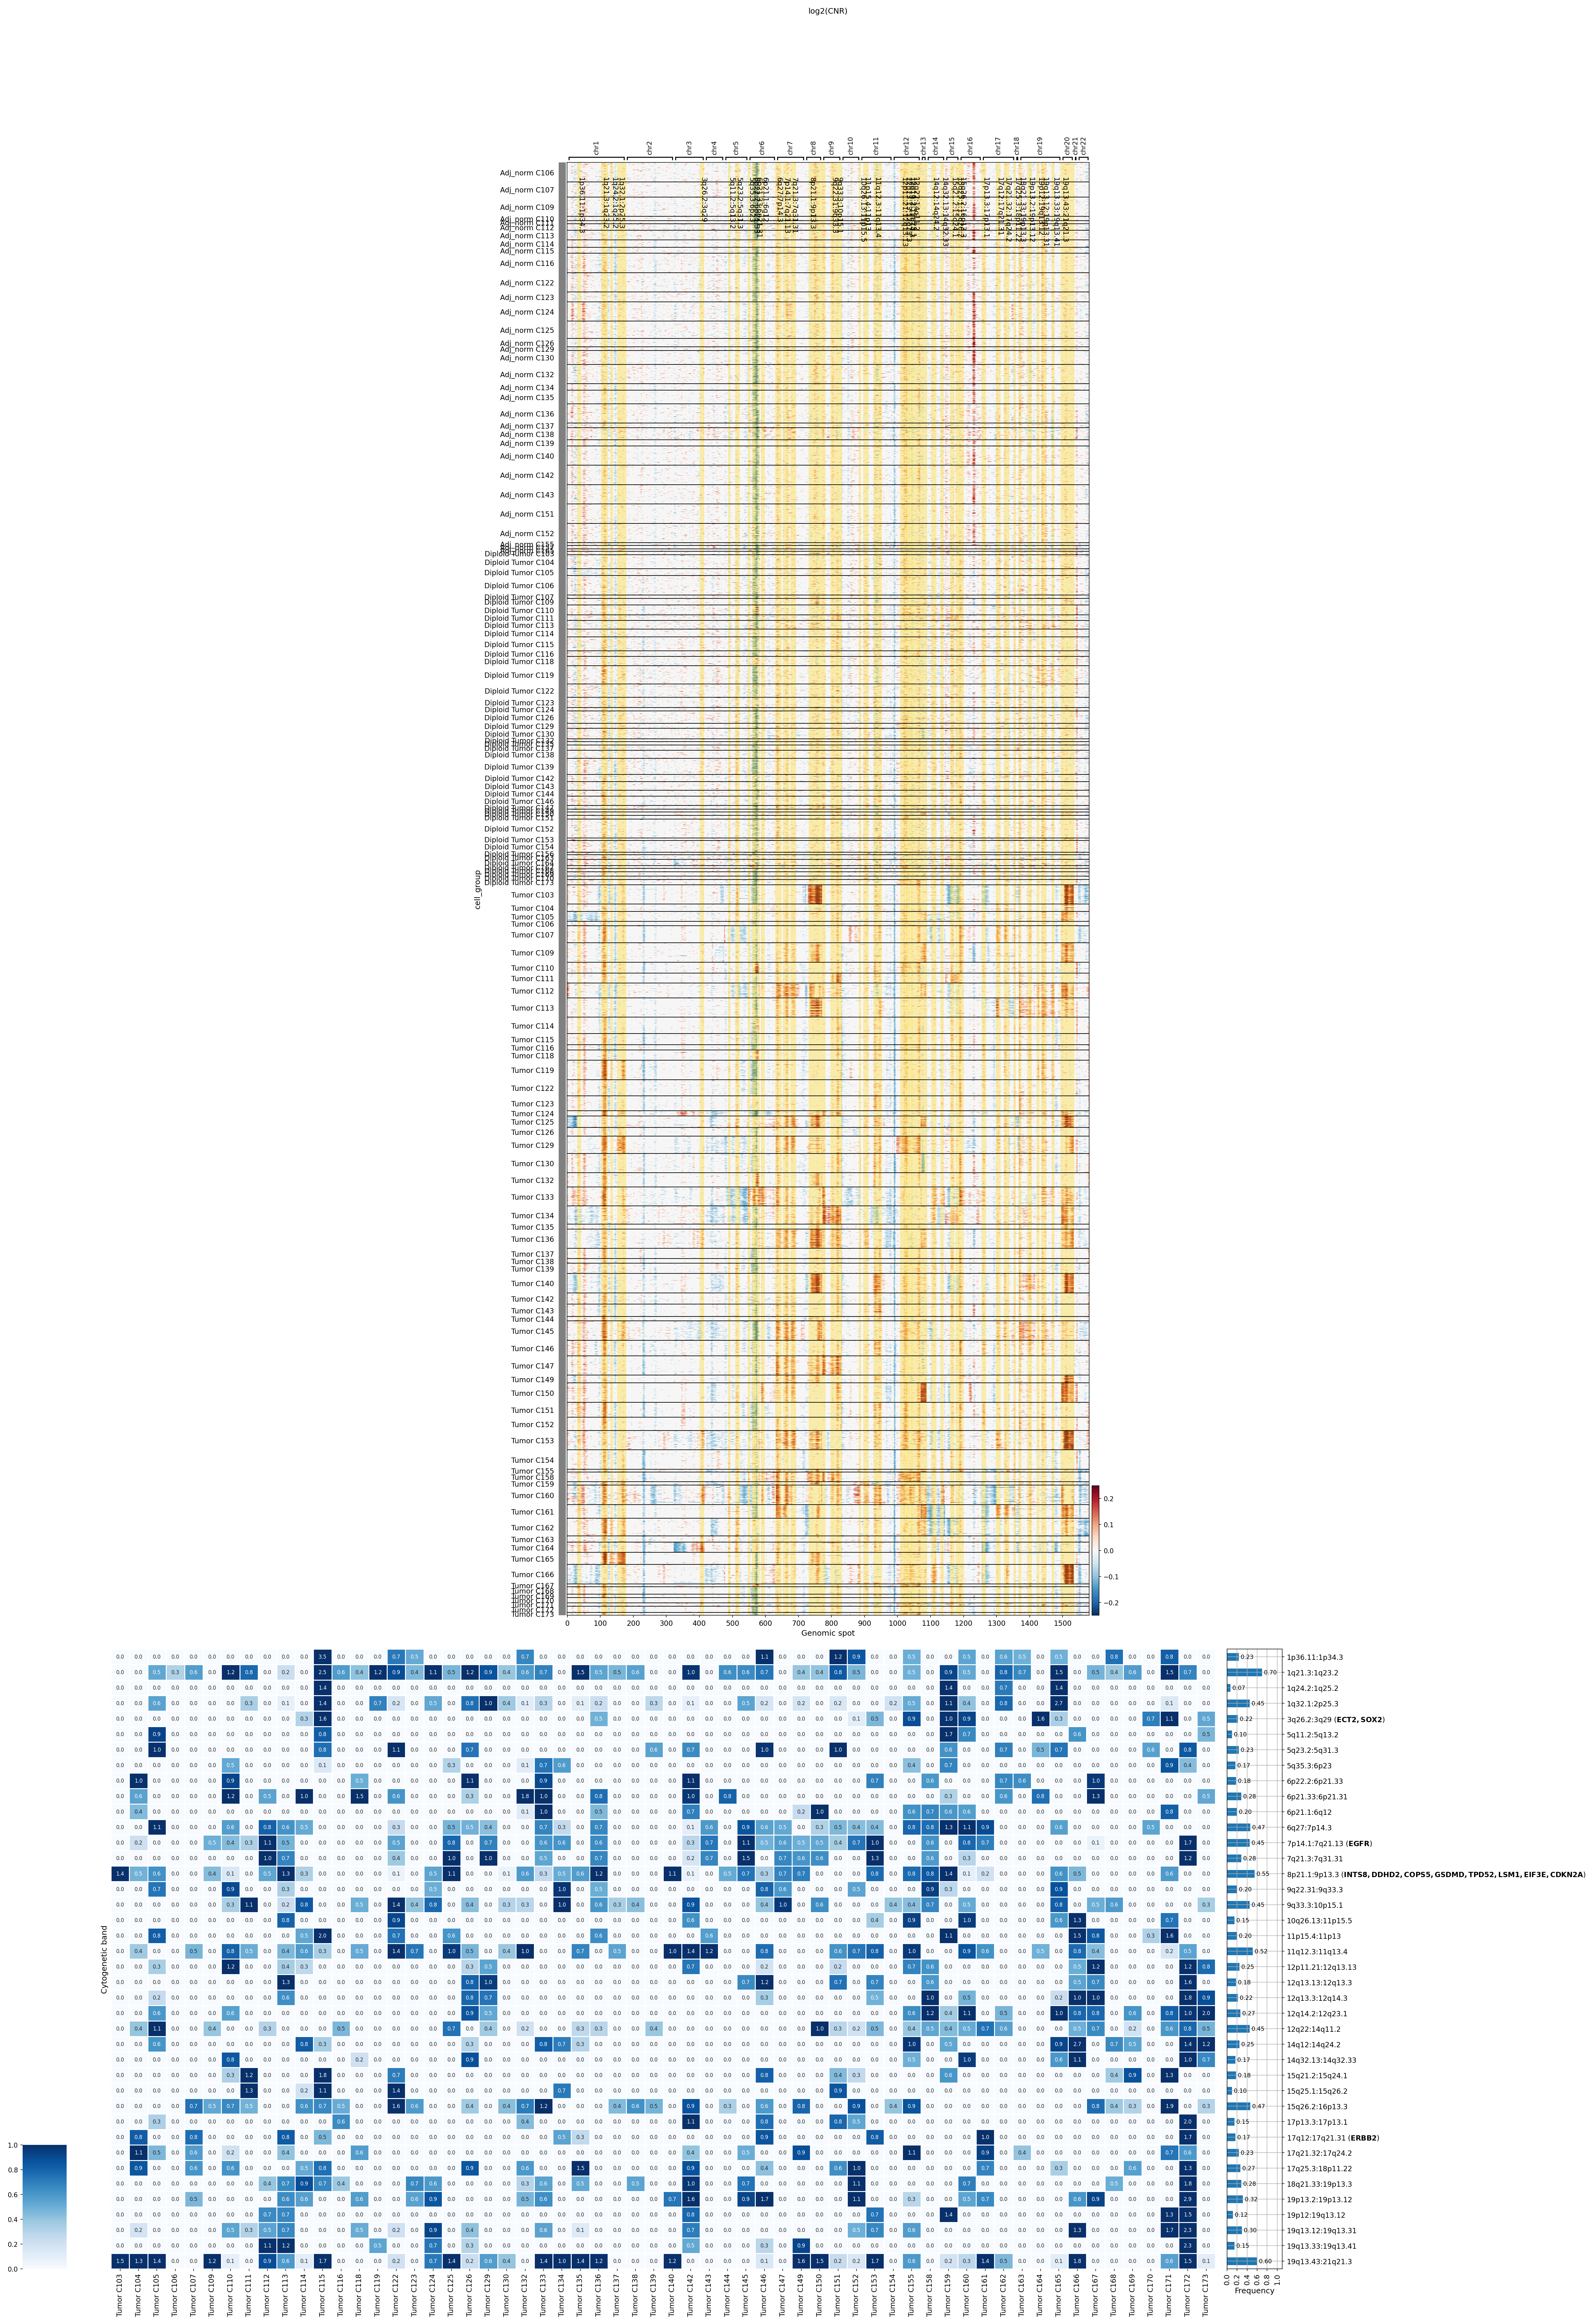
This analysis investigates Copy Number Variations (CNVs) in Intestinal Epithelial cells from human colon tissue, comparing 'Tumor' and 'Adj_normal' conditions. The plot_cnv_heatmap tool was used to visualize log2(Copy Number Ratio) across genomic spots for individual cell groups, clustered by sample. A summary heatmap of significantly amplified regions and their frequency across tumor samples was also generated. The primary goal is to identify and characterize genomic alterations characteristic of colorectal cancer in the presumed tumor-origin cell type.
Visual Summary
CNV Heatmap (log2(CNR))
The main heatmap displays log2(Copy Number Ratio) values, where red signifies amplification, blue signifies deletion, and yellow/white indicates a near-diploid state.
- Adjacent Normal Samples: The 'Adj_norm' samples (e.g., Adj_norm C106 to C157) generally exhibit a relatively uniform, near-diploid (yellow/white) pattern across most genomic regions, with some minor, sporadic variations. This indicates genomic stability typical of healthy tissue.
- Tumor Samples - Diploid vs. Aneuploid: Within the 'Tumor' condition, a clear distinction is observed between cells labeled as 'Diploid Tumor' and 'Aneuploid Tumor'.
- Diploid Tumor Cells: These cells often show patterns more similar to adjacent normal cells, or present with more focal and less extensive CNVs. This might represent early stages of transformation, specific tumor subclones, or cells that maintain a near-diploid state despite being part of the tumor microenvironment.
- Aneuploid Tumor Cells: These cells (e.g., Aneuploid Tumor C104 to C161) demonstrate extensive and widespread copy number alterations, characterized by large contiguous regions of both amplifications (red) and deletions (blue). This finding strongly validates the aneuploidy calls and highlights the genomic instability commonly associated with malignancy.
- Recurrent Alterations: Across multiple tumor samples, recurrent patterns of amplification are noticeable, particularly on chromosomes such as 7, 8, 13, and 20. These patterns suggest common drivers of genomic instability and tumorigenesis in colorectal cancer.
CNV Amplification Frequency Summary Heatmap
This heatmap summarizes the frequency of significantly amplified regions at the cytogenetic band level across individual tumor samples. Darker blue indicates higher frequency of amplification for a given region in a given sample.
- Widespread Amplifications in Tumor: Numerous cytogenetic bands show high frequencies of amplification (dark blue) across a substantial number of tumor samples, reinforcing the observation of extensive CNVs in malignant cells.
- Key Recurrent Amplified Regions: Several regions exhibit high and frequent amplification across many tumor samples:
- 7p11.2 (EGFR): A well-known oncogene, frequently amplified in various cancers, including colorectal cancer.
- 8q24.21 (MYC, KDEL2): MYC is a potent proto-oncogene, and its amplification is a common driver in many cancers.
- 13q14.2 (RB1): While RB1 is a tumor suppressor gene typically inactivated by deletion, its presence in an amplified region indicates that other genes within this band might be subject to amplification or that the region is generally prone to amplification events.
- 17q21.31-17q21.32 (ERBB2): ERBB2 (HER2) is another significant oncogene, amplification of which is a therapeutic target in a subset of cancers.
- 20q13.33 (TPX2): TPX2 is a mitotic spindle assembly factor often overexpressed in cancers.
- Other frequently amplified regions include 1q21.3 (S100A8, S100A9), 5p15.33 (TERT), and 12q13.3 (MDM2).
- Sample-Specific Heterogeneity: While recurrent patterns exist, each tumor sample exhibits a unique combination and extent of amplifications, reflecting inter-patient genomic heterogeneity.
Biological Interpretation
The CNV analysis of Intestinal Epithelial cells strongly supports the inference of colorectal cancer pathology.
- Genomic Instability as a Hallmark of Cancer: The stark contrast in CNV profiles between adjacent normal and tumor Intestinal Epithelial cells, particularly the extensive amplifications and deletions in aneuploid tumor cells, is a hallmark of cancer progression. This genomic instability drives tumor evolution, heterogeneity, and adaptation.
- Oncogenic Amplifications in Colorectal Cancer: The observed recurrent amplifications are highly relevant to colorectal cancer biology:
- EGFR (7p11.2) amplification: Epidermal Growth Factor Receptor is a receptor tyrosine kinase that promotes cell proliferation, survival, and migration. Its amplification is a known driver in colorectal cancer and a target for therapies. GeneCards: EGFR
- MYC (8q24.21) amplification: The MYC proto-oncogene is a central regulator of cell growth, metabolism, and proliferation. Amplification and overexpression of MYC are associated with aggressive tumor phenotypes and poor prognosis in many cancers, including CRC. GeneCards: MYC
- ERBB2 (17q21.31-17q21.32) amplification: ERBB2 (HER2) is another oncogenic receptor tyrosine kinase. HER2 amplification defines a subset of colorectal cancers that can respond to HER2-targeted therapies. GeneCards: ERBB2
- TERT (5p15.33) amplification: Telomerase Reverse Transcriptase, TERT, maintains telomere length, contributing to cellular immortality—a critical cancer hallmark. TERT amplification and overexpression are frequently observed in various cancers. GeneCards: TERT
- MDM2 (12q13.3) amplification: MDM2 is an E3 ubiquitin ligase that targets the p53 tumor suppressor for degradation. MDM2 amplification can lead to functional inactivation of p53, thereby promoting cell survival and proliferation. GeneCards: MDM2
- Regions containing tumor suppressors: The identification of amplification in regions like 13q14.2 (RB1), 1p34.3 (CDKN2A), and 18q21.33 (SMAD4) is interesting. While RB1, CDKN2A, and SMAD4 are well-established tumor suppressor genes typically inactivated by deletion or mutation in cancer, these cytogenetic bands are broad and can contain other genes. It is plausible that other oncogenic drivers within these amplified regions are contributing to tumor progression, or this may reflect complex genomic rearrangements.
- Role of Diploid Tumor Cells: The presence of 'Diploid Tumor' cells with less pronounced CNVs suggests the possibility of cellular plasticity, early evolutionary stages of malignancy, or distinct tumor subpopulations within the same patient. These cells might still harbor driver mutations not detectable as large-scale CNVs or contribute to tumor heterogeneity.
Clinical or Translational Implications
- Biomarker and Prognostic Value: The identified recurrent CNVs, particularly amplifications of known oncogenes such as EGFR, MYC, and ERBB2, can serve as potential diagnostic, prognostic, and predictive biomarkers for colorectal cancer patients. Their presence and extent could correlate with disease aggressiveness and response to therapy.
- Therapeutic Targeting: The amplification of therapeutically targetable genes like EGFR and ERBB2 in Intestinal Epithelial cells highlights potential avenues for precision medicine in colorectal cancer. Patients whose tumors exhibit these amplifications may benefit from targeted therapies (e.g., anti-EGFR antibodies or HER2 inhibitors) that specifically block the activity of these oncogenes. PubMed Search: EGFR inhibitors colorectal cancer, PubMed Search: HER2 targeted therapy colorectal cancer
- Patient Stratification: The distinct CNV landscapes observed across individual tumor samples underscore the genomic heterogeneity of colorectal cancer. This suggests that a 'one-size-fits-all' approach to treatment may be suboptimal, and genomic profiling, including CNV analysis, could be crucial for stratifying patients into groups most likely to respond to specific therapies.
- Understanding Drug Resistance: Genomic instability and the presence of diverse CNV profiles contribute to the capacity of tumors to evolve and develop resistance to treatment. Monitoring CNV changes over time or after treatment could provide insights into resistance mechanisms.
5. CNV-Aware UMAP Visualization of Cell Type, Ploidy, Condition, and Sample Distribution in Colon Tissue
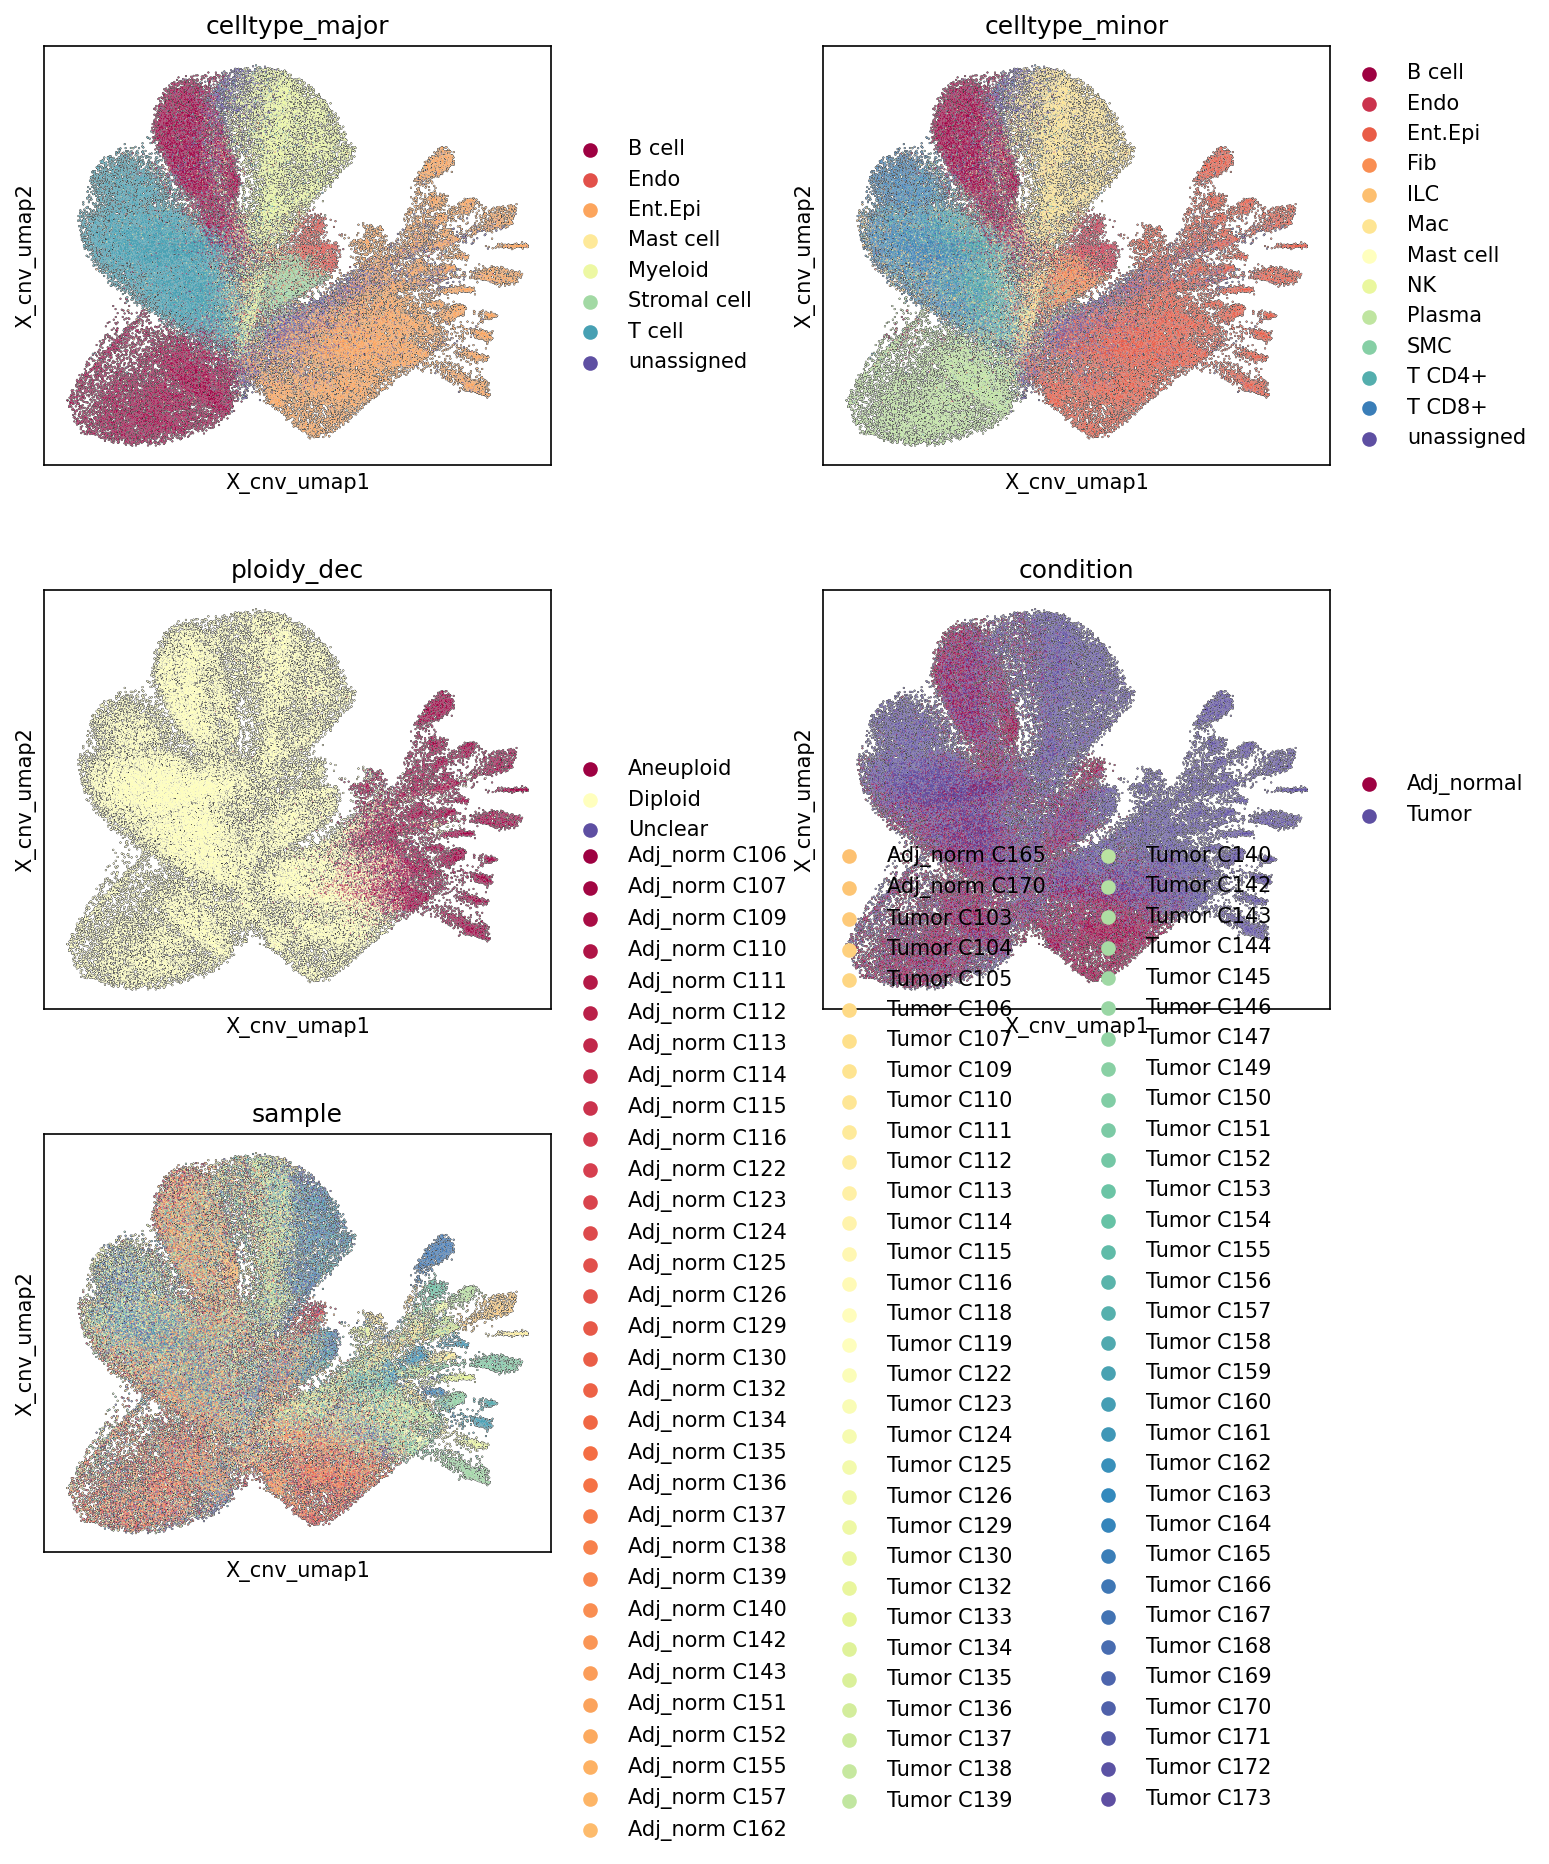
[Analysis Visualization Results]...
Analysis Overview
This analysis presents UMAP visualizations of single cells, where the embedding space ('X_cnv_umap1', 'X_cnv_umap2') is derived using copy number variation (CNV) patterns. These plots illustrate how major cell types, minor cell types, ploidy status, biological condition (Tumor vs. Adj_normal), and individual samples distribute within this CNV-informed manifold. The primary goal is to assess the separation and clustering of cells based on their genomic integrity, and to evaluate the consistency of cell type and ploidy annotations with the observed CNV landscape.
Visual Summary
The UMAPs reveal a clear structural separation of cells into distinct populations based on CNV profiles.
- Overall Embedding Structure: The UMAP displays a large, dense cluster on the left and center, and a more elongated, branching cluster extending to the right. This structural dichotomy is a key feature in all plots.
Cell Type Distribution (celltype_major, celltype_minor):
- The large, central cluster predominantly comprises various immune cells (T cells, B cells, Myeloid cells), stromal cells, and endothelial cells.
- The distinct elongated cluster on the right is highly enriched with Intestinal Epithelial cells. Minor populations like Tuft cells, Goblet cells, Enterocytes, and Crypt cells (subtypes of Intestinal Epithelial cells) also align with this cluster.
Ploidy Status Distribution (ploidy_dec):
- The large central cluster is almost entirely composed of 'Diploid' cells.
- In stark contrast, the distinct right-side elongated cluster is overwhelmingly labeled as 'Aneuploid'. Cells with 'Unclear' ploidy status are sparse and scattered. This plot demonstrates that the CNV-aware UMAP effectively segregates cells based on their ploidy.
Condition Distribution (condition):
- Cells from 'Adj_normal' tissue predominantly reside within the large central cluster, largely overlapping with the diploid cell population.
- 'Tumor' cells show a bimodal distribution: a significant portion populates the aneuploid, epithelial-enriched cluster on the right, while another substantial fraction is found intermingled within the diploid cluster on the left. This mixing is expected, as tumor biopsies contain not only malignant cells but also various non-malignant immune and stromal cells that constitute the tumor microenvironment.
Sample Distribution (sample):
- Within the large diploid cluster, cells from different 'Adj_normal' and 'Tumor' samples appear generally well-integrated, indicating reasonable batch correction or inherent similarity among non-malignant cells across samples.
- Within the aneuploid cluster, while there is overall mixing of 'Tumor' samples, some degree of sample-specific clustering is visible, suggesting inter-patient heterogeneity in the specific CNV patterns of malignant cells.
Biological Interpretation
The CNV-aware UMAP provides strong evidence for a distinct population of malignant cells within the colon tissue samples.
- Identification of Malignant Cells: The most striking finding is the clear separation of 'Aneuploid' cells from 'Diploid' cells based on CNV patterns. This aneuploid population is predominantly identified as 'Intestinal Epithelial cell', which is consistent with the 'Resolved tumor-origin cell type' and the known biology of colorectal adenocarcinoma, where malignant cells typically originate from epithelial lineage and often exhibit aneuploidy.
- Tumor Microenvironment: The presence of a substantial number of 'Diploid' cells within the 'Tumor' condition, intermingled with cells from 'Adj_normal' tissue, confirms the diverse cellular composition of the tumor microenvironment. This includes various immune (T cells, B cells, Myeloid cells) and stromal cells (Fibroblasts, Endothelial cells) that infiltrate or reside within the tumor and are typically diploid.
- Ploidy as a Marker for Malignancy: The strong co-localization of 'Aneuploid' status with 'Tumor' condition and 'Intestinal Epithelial cell' identity within a unique UMAP region reinforces the utility of CNV analysis and ploidy estimation in single-cell data for distinguishing malignant cells from the surrounding non-malignant cells.
- Inter-Patient Heterogeneity: While the UMAP shows a general clustering of aneuploid cells, the subtle sample-specific patterns within this cluster suggest that the precise CNV landscapes of malignant cells can vary between individual patients, reflecting the genomic heterogeneity of colorectal cancer.
Annotation Notes
The UMAP visualizations demonstrate that the celltype_major, celltype_minor, ploidy_dec, and condition annotations are highly congruent with the underlying CNV patterns of the cells. The distinct separation of aneuploid, epithelial cells from the broader diploid, non-epithelial populations strongly supports the accuracy and biological relevance of these annotations within the context of colorectal cancer. The embedding successfully captures the fundamental genomic differences between malignant and non-malignant cells, providing a robust basis for downstream analyses.
6. Minor Cell Type Population Bar Plot Across Conditions
[Analysis Visualization Results]...
Analysis Overview
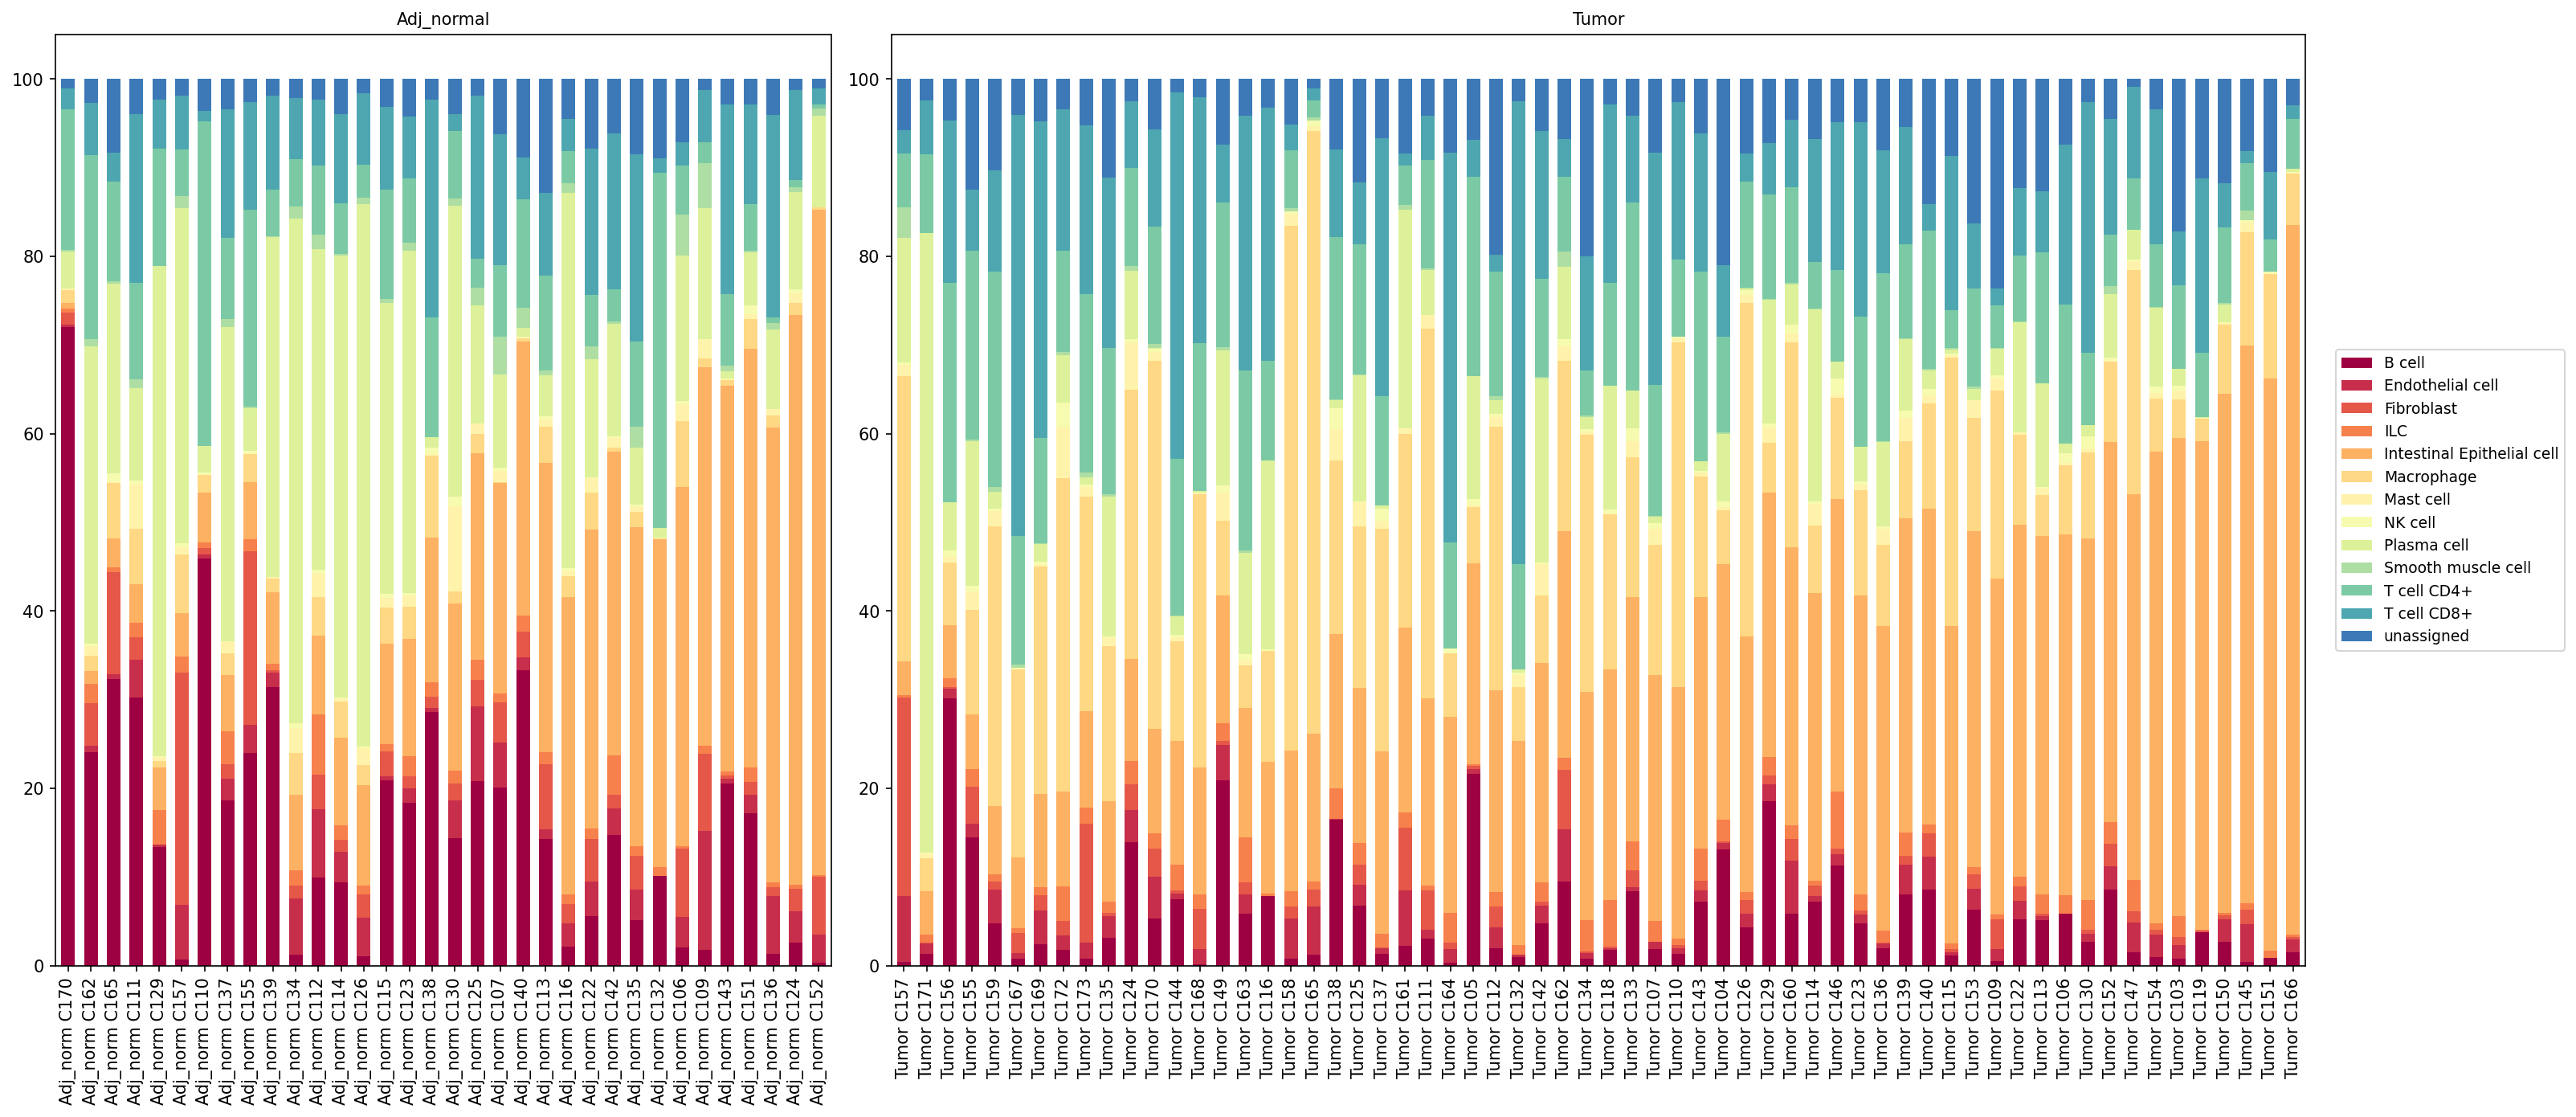
This visualization displays the relative proportions of different minor cell types within individual samples, distinguishing between 'Adj_normal' (adjacent normal) and 'Tumor' conditions derived from human colon tissue. Each bar represents a single sample, and the stacked segments within each bar show the percentage contribution of each identified minor cell type. This analysis helps to understand the cellular composition and heterogeneity across samples and conditions, providing insights into changes associated with the colorectal cancer tumor microenvironment.
Visual Summary
The bar plot provides a comprehensive overview of the minor cell type composition for each sample, grouped by 'Adj_normal' and 'Tumor' conditions.
- Dominant Cell Type in Tumor: 'Intestinal Epithelial cell' (light orange) consistently represents the largest proportion of cells in the 'Tumor' samples, often exceeding 60-70% of the total cells. This dominance is also observed in 'Adj_normal' samples, though with greater variability and often at a relatively lower proportion compared to tumor samples.
- Immune Cell Presence: Various immune cell types are observed in both conditions.
- 'T cell CD4+' (light teal) and 'T cell CD8+' (darker teal) are present across most samples, though their relative proportions vary. In 'Tumor' samples, their relative proportion can appear diluted due to the high epithelial cell content.
- 'Macrophage' (pale yellow) is a consistent component in both 'Adj_normal' and 'Tumor' samples, showing inter-sample variability.
- 'B cell' (dark red/maroon) and 'Plasma cell' (light green-yellow) appear to constitute a notable, albeit variable, proportion in some 'Adj_normal' samples, while their relative presence in 'Tumor' samples seems generally reduced or more sporadic in certain individuals.
- Stromal and Other Cell Types: 'Fibroblast' (orange-red) and 'Endothelial cell' (red) are present in smaller but consistent proportions across both conditions. 'Smooth muscle cell' (light green) and 'ILC' (orange) are generally present in very low percentages.
- Unassigned Cells: A segment labeled 'unassigned' (dark blue) is present in almost every sample, representing approximately 5-15% of cells. This indicates a portion of cells could not be confidently classified into one of the defined minor cell types.
- Inter-sample Heterogeneity: Significant heterogeneity in cell type proportions is observed between individual samples within both the 'Adj_normal' and 'Tumor' groups, reflecting individual patient differences.
Biological Interpretation
The observed shifts in cell type populations between adjacent normal and tumor tissues provide important biological insights into colorectal cancer development and its microenvironment.
- Epithelial Expansion in Tumor: The marked predominance of 'Intestinal Epithelial cells' in tumor samples is consistent with the neoplastic origin of colorectal cancer from epithelial cells. This suggests effective enrichment for tumor cells in these samples, aligning with the "Intestinal Epithelial cell" being the resolved tumor-origin cell type.
Altered Immune Microenvironment:
- The relative proportions of immune cells such as T cells and Macrophages indicate their presence within both normal colon tissue and the tumor microenvironment. Their role in cancer involves complex interactions, from anti-tumor immunity to pro-tumor inflammation.
- The potentially lower relative contribution of B cells and Plasma cells in some tumor samples compared to adjacent normal tissue might hint at alterations in adaptive humoral immune responses within the tumor, which can be critical for immune surveillance and response to therapy. PubMed search: colorectal cancer B cells tumor microenvironment
- Stromal Contribution: While fibroblasts and endothelial cells appear as smaller components, their absolute numbers and activated states are crucial in tumor progression, angiogenesis, and extracellular matrix remodeling, even if their relative proportion is diluted by the highly abundant epithelial cells in the tumor samples. GeneCards: Fibroblasts in cancer
- Unassigned Cell Populations: The consistent presence of 'unassigned' cells suggests that there may be novel or rare cell states that were not captured by the current cell type annotations, or cell states that fall ambiguously between defined types. Further investigation of these 'unassigned' populations could reveal new biological insights relevant to colorectal cancer.
Clinical or Translational Implications
Understanding the cellular composition of colorectal tumors and adjacent normal tissue has several clinical and translational implications:
- Tumor Purity and Treatment Stratification: The high proportion of 'Intestinal Epithelial cells' in tumor samples validates these samples for studies focused on the biology of the cancer cells themselves. This cellular context is crucial for interpreting downstream analyses like differential gene expression or pathway enrichment, ensuring they reflect tumor-specific processes.
- Immunosuppression and Immunotherapy Response: Changes in the relative abundance of immune cell populations, particularly the potential shifts in B cell and Plasma cell proportions, could indicate an altered immune landscape in the tumor. This is highly relevant for predicting response to immunotherapies, as the composition of the tumor microenvironment significantly influences treatment efficacy in colorectal cancer. PubMed search: colorectal cancer immunotherapy tumor microenvironment
- Biomarker Discovery: Discrepancies in cell type populations between tumor and normal tissue, especially for immune or stromal cells, could point to potential prognostic or predictive biomarkers. For instance, specific immune cell infiltrates are known to correlate with patient outcomes in various cancers.
- Heterogeneity as a Challenge: The observed sample-to-sample variability in cell type composition highlights the inherent heterogeneity of colorectal cancer. This patient-specific cellular landscape suggests that personalized approaches to diagnosis and treatment, accounting for individual tumor microenvironments, may yield better outcomes.
7. T Cell and Innate Lymphoid Cell Subpopulation Analysis in Colorectal Cancer
[Analysis Visualization Results]...
Analysis Overview
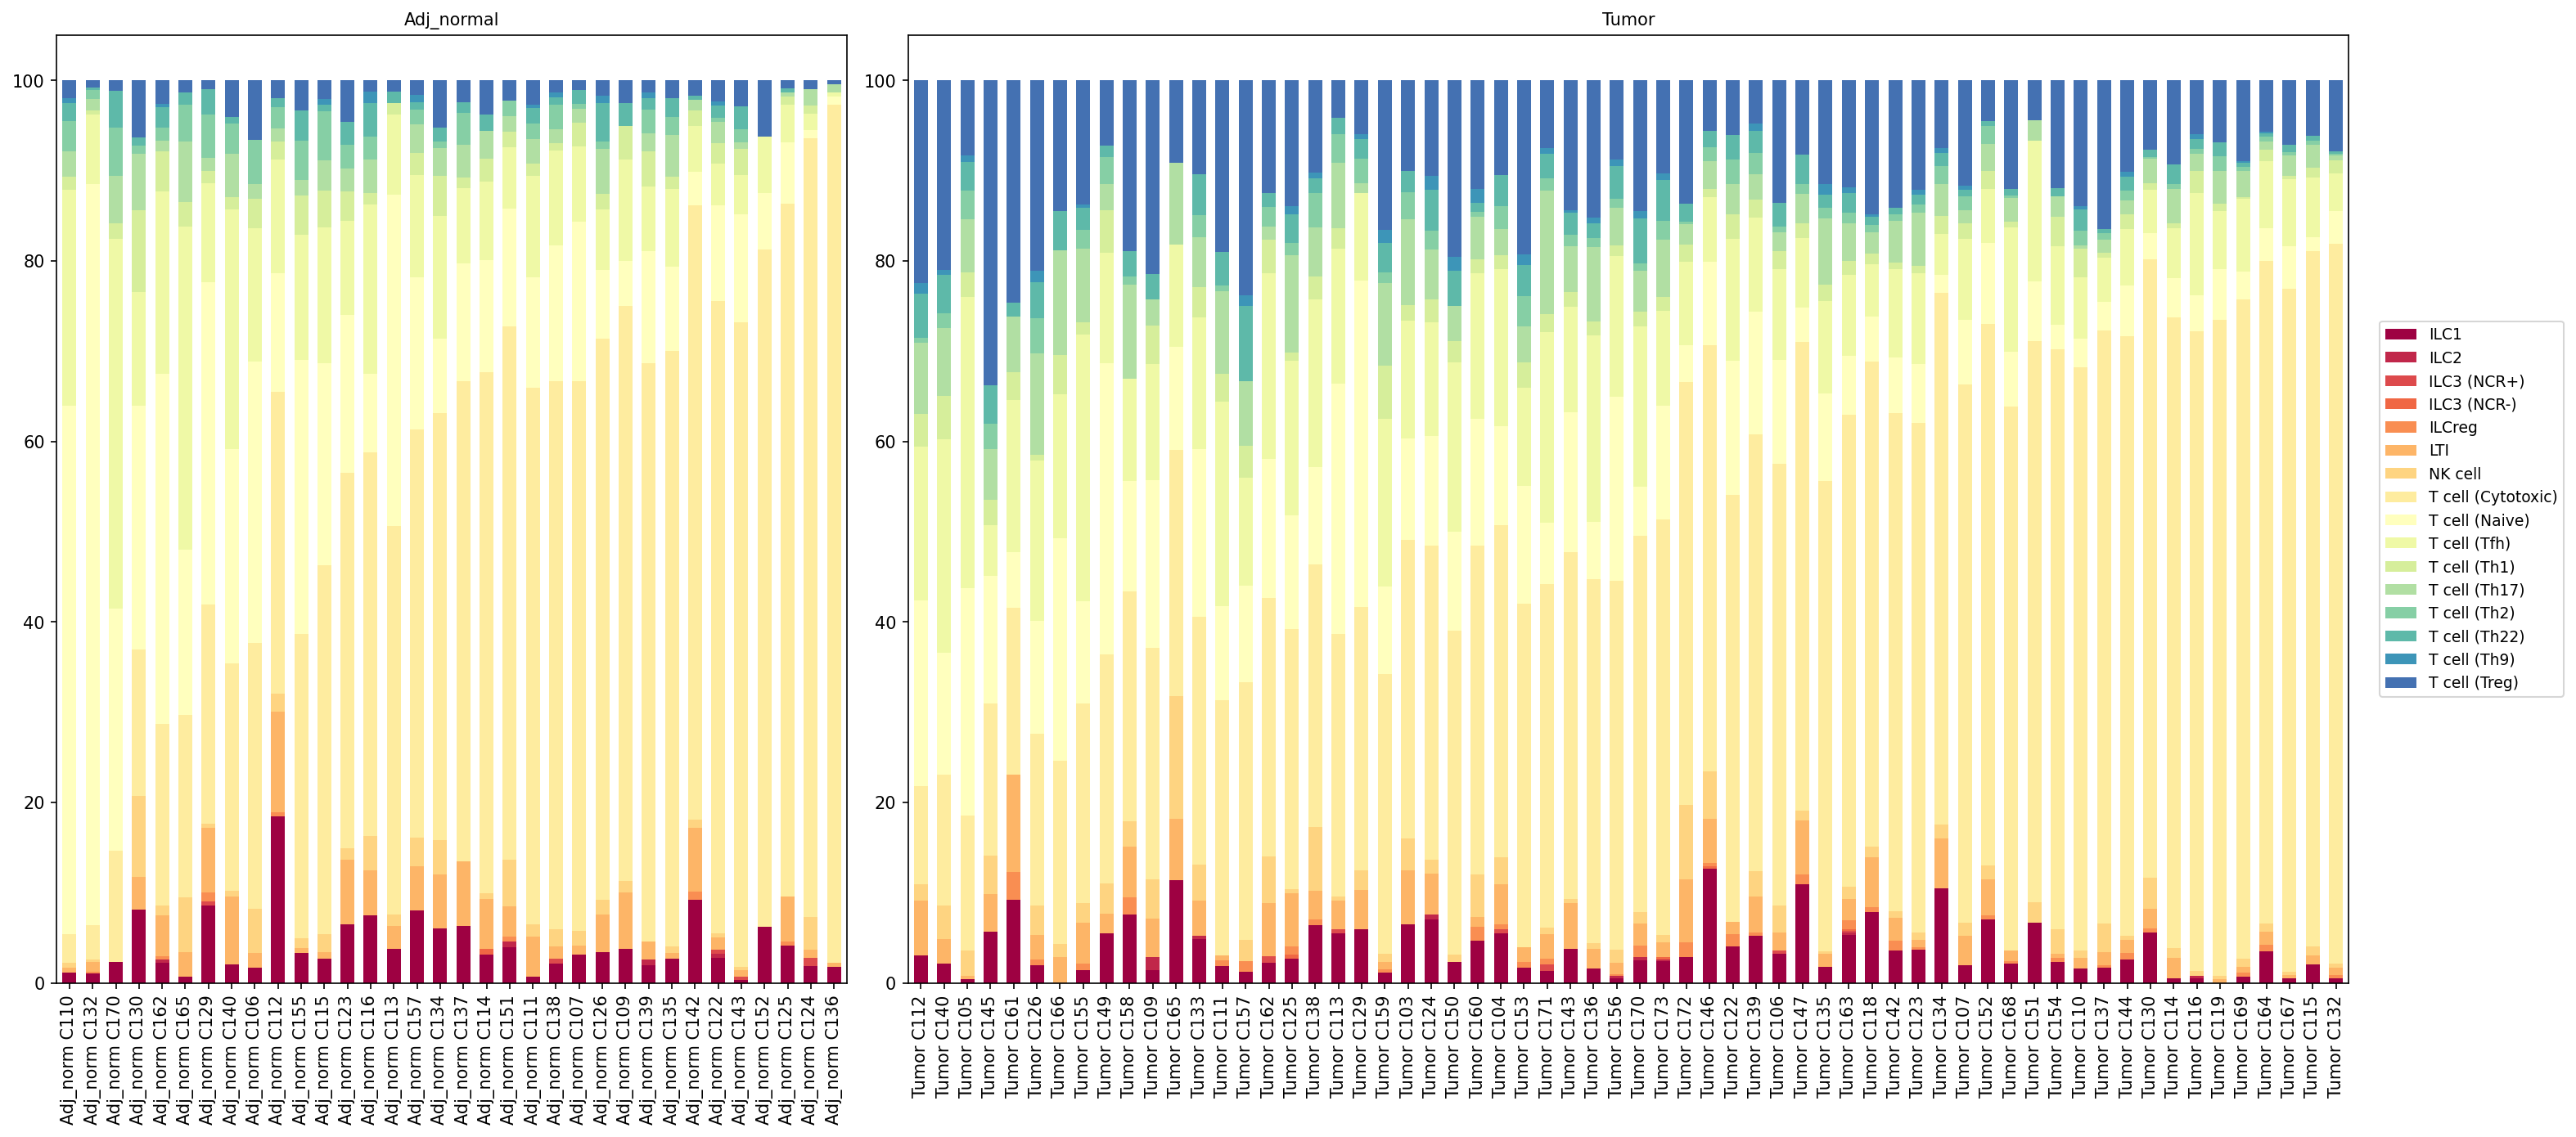
This analysis presents a stacked bar plot visualizing the proportional distribution of various T cell subsets and related innate lymphoid cell (ILC) populations across individual samples, comparing 'Adj_normal' (adjacent normal colon tissue) and 'Tumor' (colorectal tumor tissue) conditions. Each bar represents a single sample, and the segments within the bar show the relative abundance of each cell subset within the broader T cell/ILC compartment. This analysis aims to highlight potential shifts in the immune microenvironment associated with colorectal cancer development.
Visual Summary
The stacked bar plots display the relative proportions of 18 different cell subsets, including various T helper (Th) cell types, cytotoxic T cells, naive T cells, regulatory T cells (Tregs), NK cells, and several ILC subsets. Samples are clearly demarcated by 'Adj_normal' and 'Tumor' conditions.
Key observations:
- Dominance of Cytotoxic and Naive T cells: In both 'Adj_normal' and 'Tumor' samples, T cell (Cytotoxic) (lightest yellow) and T cell (Naive) (very light yellow) subsets constitute a large proportion of the total T cell/ILC population, with T cell (Cytotoxic) generally being the most abundant.
- Increase in Regulatory T cells (Treg) in Tumor: The dark blue segment representing T cell (Treg) appears to be more prominent and consistently present at higher proportions across many 'Tumor' samples compared to 'Adj_normal' samples. While present in adjacent normal tissue, their contribution to the total T cell population seems to increase in the tumor microenvironment.
- Shift in T Helper Cell Proportions: There are subtle but noticeable shifts in the proportions of various T helper cell subsets (Th1, Th2, Th9, Th17, Th22, Tfh). The lighter green shades (Th1, Th17) and blue-green shades (Th2, Th22, Th9) generally show a variable contribution. While no single Th subset shows an overwhelmingly dominant shift, their collective distribution appears altered.
- Innate Lymphoid Cells (ILCs) and NK Cells: NK cell (pale orange) and various ILCs (red/orange shades: ILC1, ILC2, ILC3 (NCR+), ILC3 (NCR-), ILCreg, LTI) are present in smaller proportions overall. ILC1 (darkest red) shows variable presence, occasionally appearing at higher proportions in some individual 'Adj_normal' and 'Tumor' samples, but without a clear, consistent trend between conditions.
- Sample Heterogeneity: Within both conditions, particularly the 'Tumor' group, there is considerable sample-to-sample heterogeneity in the exact proportions of these subsets, indicating individual patient-level variations in immune composition.
Biological Interpretation
The observed shifts in T cell and ILC populations provide insights into the immune response in the colorectal cancer microenvironment.
- Immunosuppressive Microenvironment: The increase in T cell (Treg) populations in tumor samples is a significant finding. Regulatory T cells are known to suppress anti-tumor immune responses by inhibiting the proliferation and function of effector T cells, such as T cell (Cytotoxic). This expansion of Tregs contributes to an immunosuppressive tumor microenvironment, allowing cancer cells to evade immune surveillance and progress PubMed: 28258380.
- Altered Balance of Effector T cells: While T cell (Cytotoxic) cells remain a major component, their *relative* proportion might be effectively diminished by the increasing presence of immunosuppressive cells like Tregs or by other mechanisms, reducing their anti-tumor efficacy.
- Role of Th Cell Subsets: The dynamic changes in various Th cell subsets (Th1, Th2, Th17, Th22, Th9, Tfh) suggest a complex modulation of the inflammatory and adaptive immune responses within the tumor. For instance, Th1 cells are typically associated with anti-tumor immunity (via IFN-γ production), while Th2 cells can promote tumor growth in some contexts. Th17 cells have a dual role, sometimes promoting, sometimes inhibiting, depending on the tumor type and stage. The nuanced shifts observed here warrant further investigation into the functional states of these cells.
- Innate Lymphoid Cells in Cancer: Although less prominent, the presence and slight variations in NK cells and ILCs (ILC1, ILC2, ILC3) suggest their involvement in both normal tissue homeostasis and the tumor response. NK cells are important for immediate anti-tumor cytotoxic responses UniProt: P01584 (NKG2D), while ILCs can bridge innate and adaptive immunity, contributing to inflammation or tissue repair, with specific ILC subsets having reported roles in promoting or suppressing tumor immunity.
Clinical or Translational Implications
The distinct alterations in T cell and ILC populations, particularly the expansion of Tregs in the tumor microenvironment, have several clinical implications for colorectal cancer:
- Prognostic Biomarkers: A higher proportion of Tregs in the tumor could serve as a potential prognostic biomarker for poorer outcomes in CRC, as it indicates a more immunosuppressed state.
- Therapeutic Targets: Modulating the balance of these immune cell populations represents a promising therapeutic strategy.
- Targeting Tregs: Reducing Treg activity or numbers could unleash anti-tumor immunity, potentially by blocking their suppressive functions or depleting them. This is an active area of research in cancer immunotherapy PubMed: 32669645.
- Enhancing Effector T cells: Strategies to enhance the function or persistence of T cell (Cytotoxic) cells and beneficial Th1 subsets (e.g., through checkpoint blockade or adoptive cell transfer) could improve therapeutic responses.
- Patient Stratification: Understanding the immune cell landscape heterogeneity across patients could help stratify individuals for specific immunotherapeutic approaches, moving towards personalized medicine. For instance, patients with a highly Treg-infiltrated tumor might benefit more from Treg-depleting agents.
8. T Cell Subset Population Dynamics in Colorectal Cancer
[Analysis Visualization Results]...
Analysis Overview
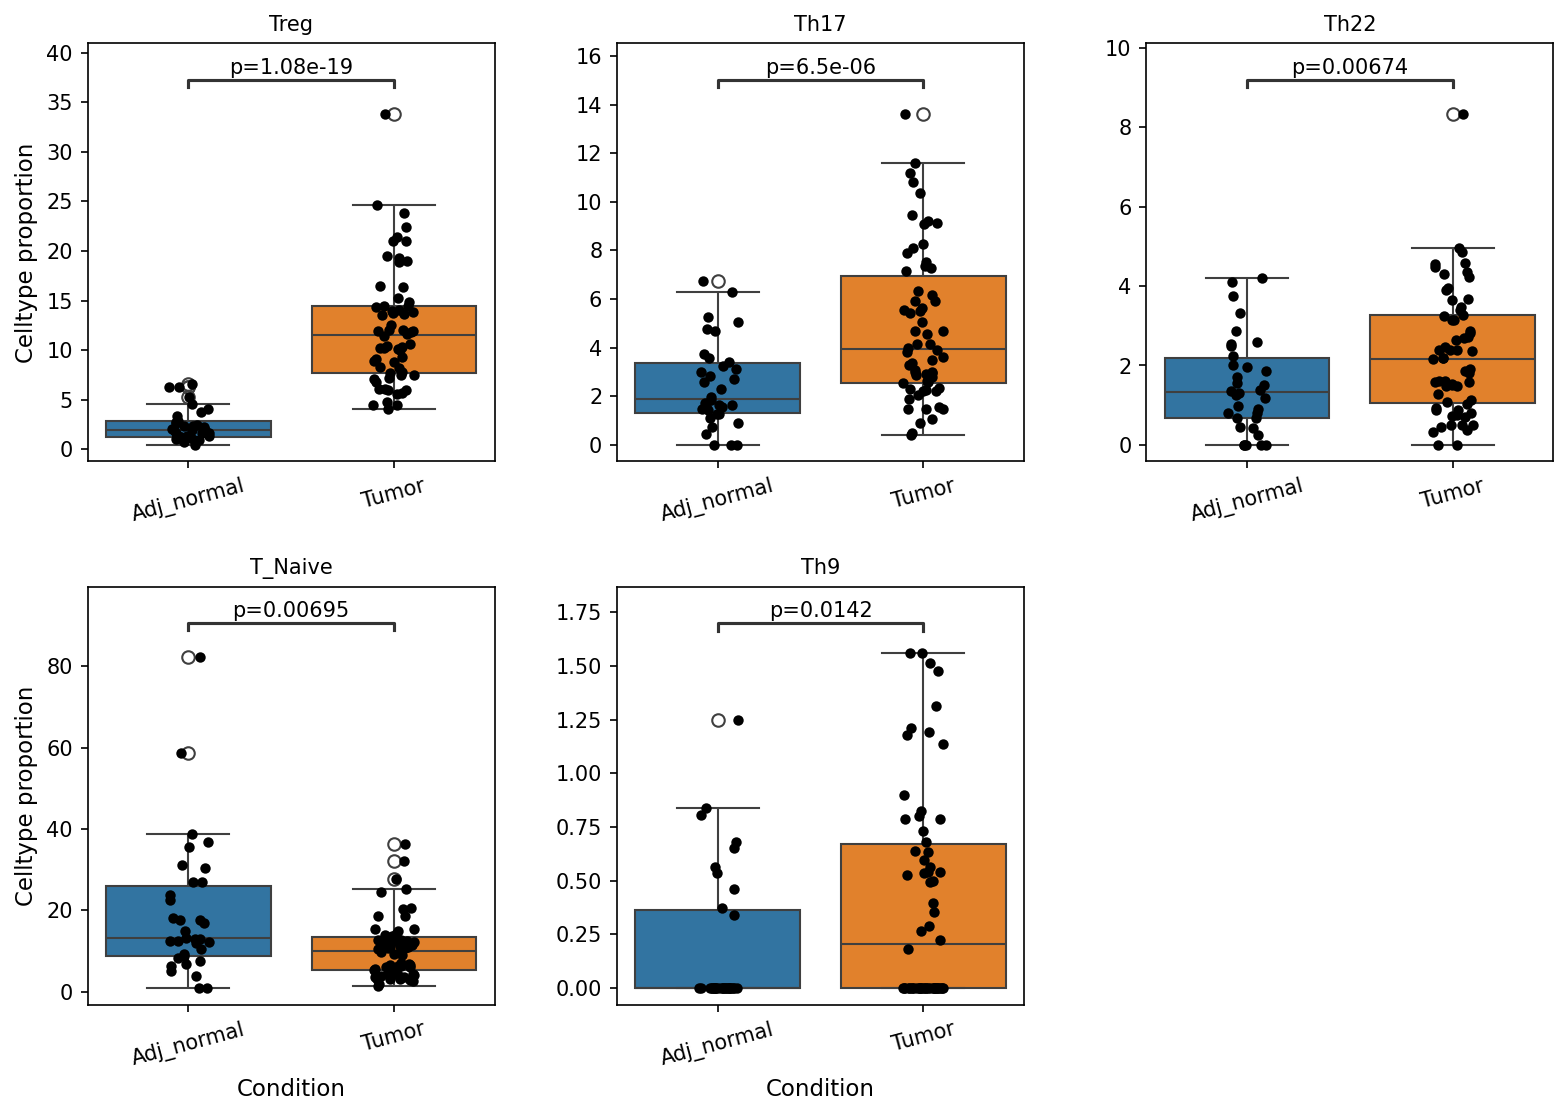
This analysis investigates the proportional differences of various T cell subsets between 'Adj_normal' (adjacent normal tissue) and 'Tumor' conditions within human colon samples, as derived from single-cell RNA sequencing data. Box plots illustrate the distribution of cell type proportions across individual samples for each condition, with statistical significance indicated by p-values. The objective is to identify T cell subsets whose proportions are significantly altered in the colorectal tumor microenvironment, providing insights into immune shifts associated with cancer progression.
Visual Summary
The box plots reveal distinct shifts in the proportions of several T cell subsets when comparing tumor tissue to adjacent normal tissue.
Increased Proportions in Tumor Tissue (relative to Adjacent Normal):
- Treg (Regulatory T cells): Showed a highly significant increase in tumor tissue (median proportion notably higher, p=1.08e-19).
- Th17 (T helper 17 cells): Significantly elevated in tumor samples (p=6.5e-06).
- ILCreg (Regulatory Innate Lymphoid Cells): Demonstrated a significant increase in tumor tissue (p=0.000492).
- Th22 (T helper 22 cells): Exhibited a significant increase in tumor tissue (p=0.00674).
- Th9 (T helper 9 cells): Also showed a significant increase in tumor tissue (p=0.0142).
Decreased Proportions in Tumor Tissue (relative to Adjacent Normal):
- T_Naive (Naive T cells): Significantly reduced in tumor tissue (median proportion notably lower, p=0.00695).
- Th2 (T helper 2 cells): Showed a marginally significant decrease in tumor tissue (p=0.0597), with lower median and overall distribution compared to adjacent normal.
Biological Interpretation
The observed changes in T cell subset proportions reflect significant remodeling of the immune landscape within the colorectal cancer microenvironment.
- Immune Suppression and Tolerance: The most striking finding is the highly significant increase in Treg cells. Regulatory T cells are key mediators of immune suppression, maintaining self-tolerance and preventing excessive immune responses. Their enrichment in the tumor microenvironment is a well-established mechanism by which tumors evade anti-tumor immunity by inhibiting effector T cell functions (PubMed search: Treg cancer immune evasion). Similarly, the increase in ILCreg (regulatory innate lymphoid cells) could suggest an additional layer of innate immune regulation contributing to an immunosuppressive environment.
- Pro-tumorigenic Inflammation: The significant increases in Th17, Th22, and Th9 cells point towards a complex inflammatory milieu within the tumor.
- Th17 cells have a context-dependent role in cancer, but in colorectal cancer, they are often associated with promoting tumor growth, angiogenesis, and metastasis, potentially by inducing pro-inflammatory cytokines and recruiting other immune cells (PubMed search: Th17 colorectal cancer).
- Th22 cells can contribute to tumor progression in various cancers, including CRC, by driving chronic inflammation and influencing epithelial cell proliferation and survival (PubMed search: Th22 colorectal cancer).
- The role of Th9 cells in CRC is less clearly defined but an increase suggests their involvement in shaping the tumor immune landscape, potentially contributing to either pro- or anti-tumor effects depending on the specific context and cytokine production.
- Loss of Naive T cells: The significant decrease in T_Naive cell proportions in tumor tissue suggests a shift from an unprimed to an activated or exhausted T cell state. This could indicate either successful antigen-driven activation and differentiation of T cells within the tumor microenvironment or, conversely, a lack of recruitment of new naive T cells into the tumor, possibly due to chemokine gradients or stromal barriers.
- Altered Th2 Response: The marginal decrease in Th2 cell proportions, while less dramatic, might reflect a de-emphasis of a Th2-mediated immune response, which is typically associated with humoral immunity and allergic reactions, not always effective against solid tumors. Shifts away from Th2 dominance might indicate a different effector profile being favored in the tumor.
Collectively, these findings are consistent with the inferred biological context of Colorectal Cancer, where a complex and often immune-suppressive microenvironment characterized by specific T cell subset expansions (Treg, Th17, Th22, Th9) and reduction of naive cells supports tumor growth and immune evasion.
Clinical or Translational Implications
The observed shifts in T cell subset populations in colorectal cancer have several potential clinical and translational implications:
- Biomarkers for Prognosis and Prediction: The proportions of specific T cell subsets, particularly the elevated Tregs and Th17 cells, could serve as prognostic biomarkers for disease progression or indicators of response to therapy in colorectal cancer patients. Higher Treg infiltration, for example, is often associated with poorer outcomes in various cancers.
- Immunotherapeutic Targets: The enrichment of immunosuppressive cells like Tregs represents a clear target for immunotherapy. Strategies aimed at depleting Tregs or inhibiting their function could enhance anti-tumor immune responses. Similarly, targeting pathways that promote the differentiation or function of pro-tumorigenic Th17 and Th22 cells could be explored to remodel the tumor microenvironment towards an anti-tumor state.
- Monitoring Immune Responses: Quantifying these T cell subsets in patient biopsies or peripheral blood could provide a means to monitor the efficacy of immunotherapies, track disease progression, or identify patients who might benefit from specific immune-modulating treatments.
9. Macrophage Subset Population Dynamics in Colorectal Cancer
[Analysis Visualization Results]...
Analysis Overview
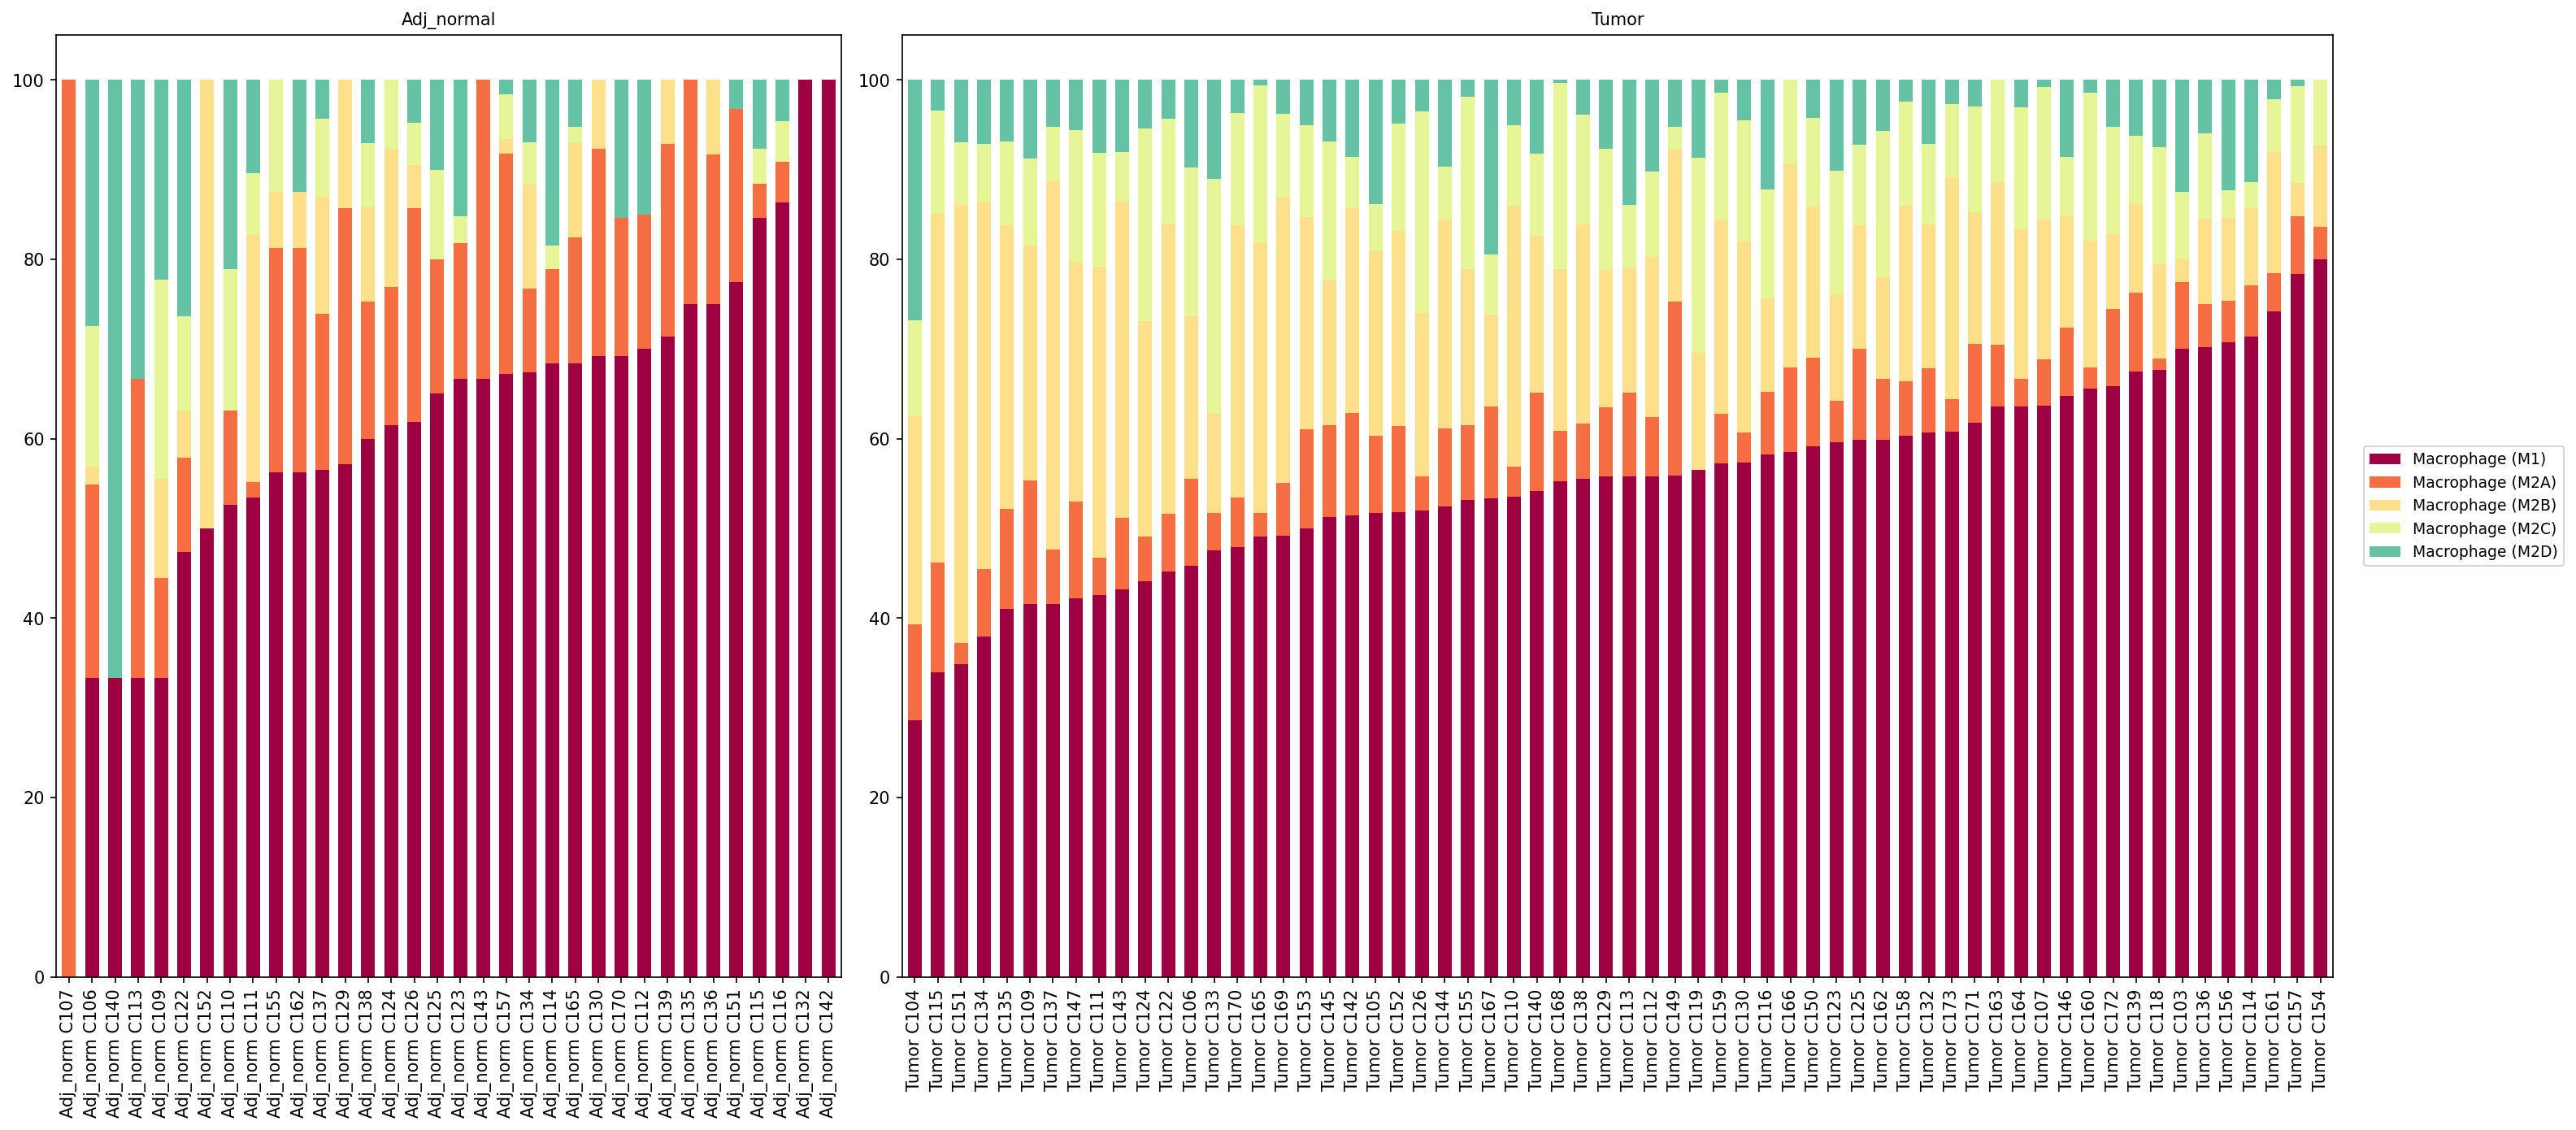
This analysis presents a population bar plot illustrating the relative proportions of different macrophage subsets within the total macrophage population across individual adjacent normal and colorectal tumor tissue samples. The macrophage subsets identified in this dataset include Macrophage (M1), Macrophage (M2A), Macrophage (M2B), Macrophage (M2C), and Macrophage (M2D). Each bar in the plot corresponds to a distinct patient sample, and the colored segments within each bar represent the fractional abundance of each macrophage subset. The samples are categorized and grouped by their tissue condition: 'Adj_normal' (adjacent normal colon tissue) and 'Tumor' (colorectal tumor tissue). For both conditions, samples are visually arranged such that the proportion of Macrophage (M1) generally increases from left to right, facilitating trend observation.
Visual Summary
The visualization clearly highlights distinct compositional differences in macrophage subsets when comparing adjacent normal and tumor samples from the colon.
- Adjacent Normal Samples: The adjacent normal tissue samples exhibit considerable heterogeneity in their macrophage subset composition. While Macrophage (M1) (dark red) is present and often constitutes a significant portion, the M2-like subsets (Macrophage (M2A) - orange, Macrophage (M2B) - light yellow, Macrophage (M2C) - pale yellow, and Macrophage (M2D) - teal) collectively contribute substantially to the total macrophage population in many individuals. The relative proportions of these M2-like subsets vary widely across different normal samples.
- Tumor Samples: In stark contrast, the colorectal tumor samples show a consistent and striking dominance of Macrophage (M1) (dark red) across most individuals. In a large number of tumor samples, Macrophage (M1) accounts for the vast majority of the macrophage population, frequently exceeding 60-70% and in several cases approaching 100%. Consequently, the cumulative proportions of the M2-like macrophages (M2A, M2B, M2C, M2D) are generally diminished in tumor samples compared to their often higher and more variable presence in adjacent normal tissue.
Biological Interpretation
The observed shift towards a predominant Macrophage (M1) phenotype within the colorectal tumor microenvironment is a significant finding that warrants detailed consideration.
- Dominance of Macrophage (M1) in Tumor: Macrophages are highly plastic immune cells, broadly categorized into M1 (pro-inflammatory, anti-tumorigenic) and M2 (anti-inflammatory, pro-tumorigenic) phenotypes, though these represent extremes of a spectrum. The consistent and high prevalence of Macrophage (M1) in colorectal tumor samples challenges the generalized paradigm where tumor microenvironments (TMEs) are typically enriched with M2-like tumor-associated macrophages (TAMs) that promote tumor growth, angiogenesis, and immune evasion. The strong presence of M1 macrophages could signify an active host-mediated anti-tumor immune response within the colon cancer TME [1, 2]. Alternatively, it might reflect a chronic inflammatory state that, while initially anti-tumor, could also paradoxically contribute to tumor progression through sustained inflammatory signaling.
- Heterogeneous Normal Tissue Immune Landscape: The variability in macrophage subset composition in adjacent normal tissue likely reflects the diverse physiological roles of macrophages in maintaining gut homeostasis, responding to local inflammation, or participating in tissue repair. The presence of M2-like macrophages in normal tissue is consistent with their functions in immune regulation and tissue remodeling.
- Colorectal Cancer Specificity: In colorectal cancer (CRC), the role of macrophages is complex and context-dependent. While M2-like TAMs are often associated with poor prognosis, some studies have reported the presence of M1-like macrophages in CRC, which can be linked to improved patient outcomes or specific disease stages [3]. The precise functional implications of these annotated M1/M2 subsets in this dataset would benefit from further investigation into their specific gene expression profiles and interactions with other immune and stromal cells within the TME.
Clinical or Translational Implications
These findings regarding the distinct macrophage subset composition in colorectal cancer offer several potential clinical and translational implications:
- Prognostic Biomarker Potential: A high prevalence of M1 macrophages within the colorectal TME, as observed here, could potentially serve as a favorable prognostic indicator, particularly if these cells retain their anti-tumorigenic functions. Further studies correlating these macrophage profiles with patient outcomes (e.g., recurrence-free survival, overall survival) are essential to validate this potential.
- Immunotherapeutic Strategy Refinement: Understanding the dominant macrophage phenotype is crucial for designing and optimizing immunotherapeutic approaches. If Macrophage (M1) cells are indeed functionally anti-tumorigenic, strategies aimed at enhancing their activation, persistence, or recruitment into the TME could be beneficial. This might involve targeting specific signaling pathways or utilizing immunomodulatory agents.
- TME Immune Status Assessment: The relative proportions of macrophage subsets could serve as valuable biomarkers to assess the overall immune status and inflammatory landscape of the TME in colorectal cancer patients. This could aid in stratifying patients and guiding treatment decisions, potentially identifying individuals more likely to respond to certain types of immunotherapy.
- Personalized Medicine Approaches: The observed inter-sample heterogeneity, particularly in the adjacent normal tissue, underscores the importance of personalized approaches in cancer immunology. Macrophage profiling could help classify patients into subgroups with distinct immune microenvironments, leading to more tailored therapeutic strategies.
---
References:
- Macrophage (M1) Information: GeneCards - M1 Macrophage
- Macrophage (M2) Information: GeneCards - M2 Macrophage
- Macrophages in Colorectal Cancer (M1/M2): PubMed Search: colorectal cancer macrophage M1 M2
10. Differential Macrophage Subpopulation Proportions in Colorectal Cancer
[Analysis Visualization Results]...
Analysis Overview
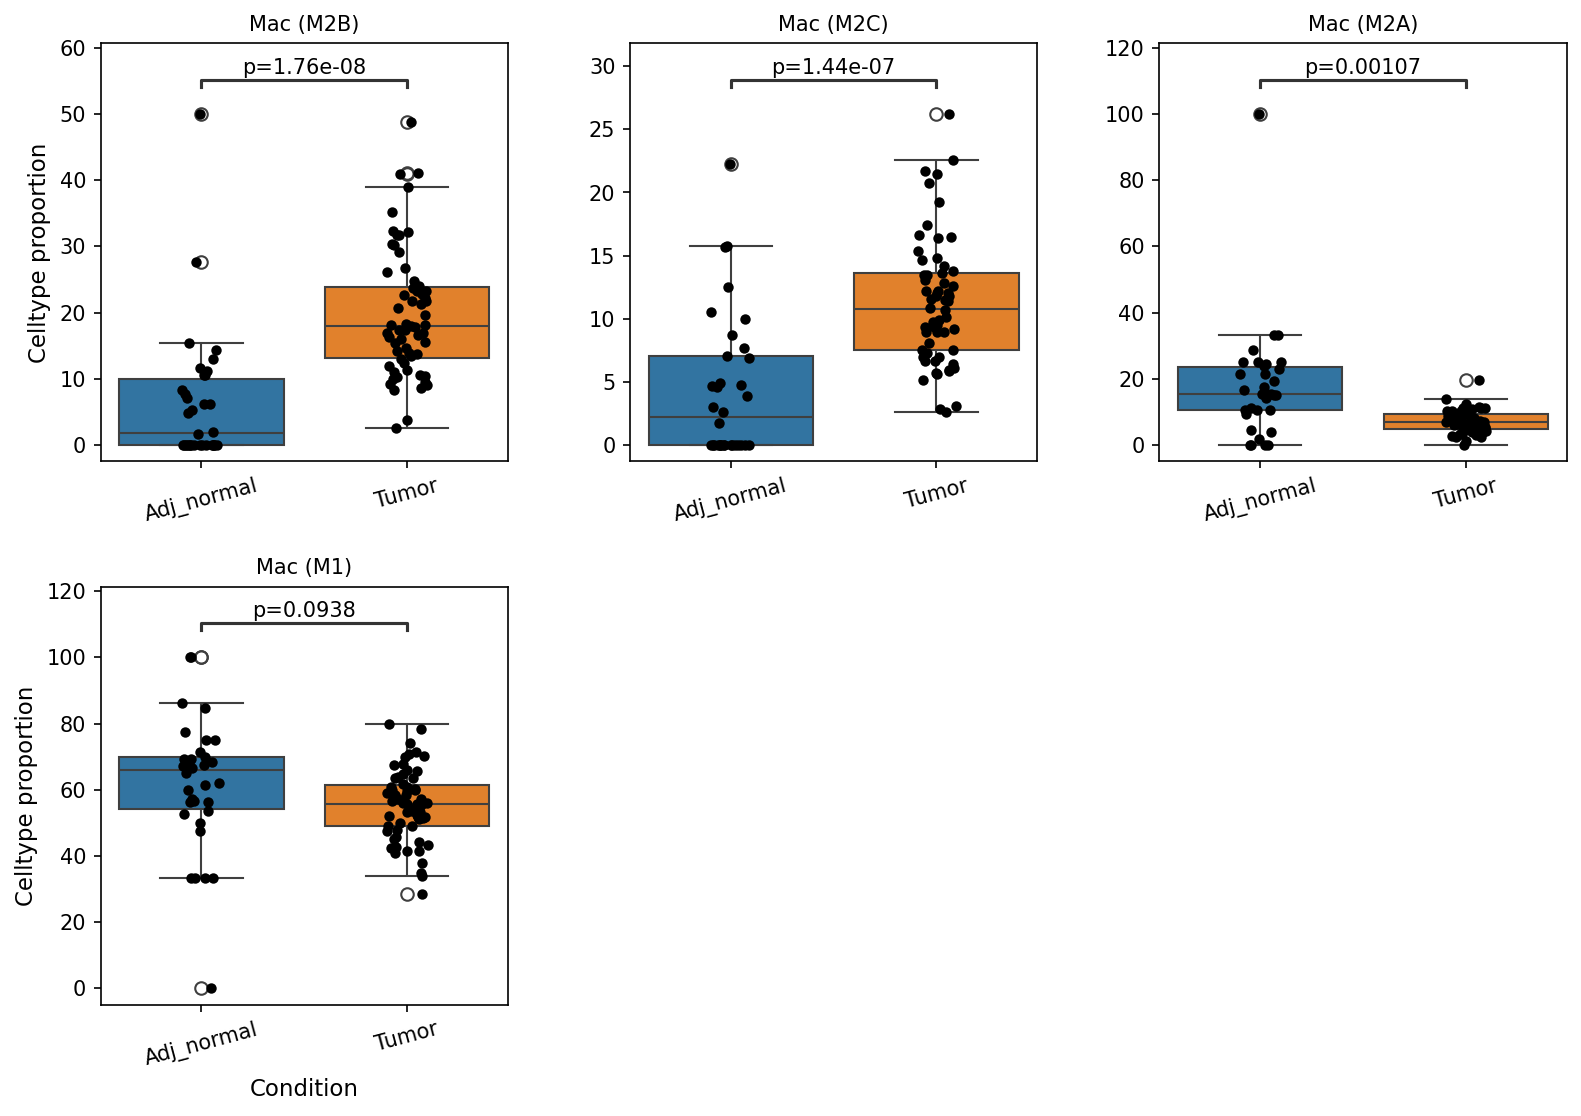
This analysis investigates the proportions of specific macrophage subsets within colon tissue, comparing samples derived from tumor tissue ("Tumor") with those from adjacent normal tissue ("Adj_normal"). The goal is to identify macrophage subpopulations that exhibit statistically significant differences in their relative abundance, providing insights into the immune microenvironment in colorectal cancer. The analysis was performed on single-cell RNA-seq data from human colon tissue, and box plots were generated to visualize cell type proportions, with statistical significance determined using a p-value cutoff of 0.1.
Visual Summary
The box plots illustrate the distribution of celltype proportions for four macrophage subsets across "Adj_normal" and "Tumor" conditions, with individual data points overlaid as a stripplot. All four macrophage subsets displayed statistically significant differences (p < 0.1) in their proportions between the two conditions:
- Mac (M2B): The proportion of Mac (M2B) cells was significantly increased in Tumor tissue compared to Adj_normal tissue (p=1.76e-08). The median proportion in Tumor tissue was approximately 20-25%, substantially higher than the median of around 5-10% in Adj_normal tissue.
- Mac (M2C): Similarly, Mac (M2C) cells showed a significant increase in proportion in Tumor tissue (p=1.44e-07). The median proportion in Tumor tissue was roughly 10-15%, whereas in Adj_normal tissue it was about 5-8%.
- Mac (M2A): In contrast, the proportion of Mac (M2A) cells was significantly decreased in Tumor tissue (p=0.00107). The median proportion in Tumor tissue was approximately 5-10%, a reduction from the median of about 20% observed in Adj_normal tissue.
- Mac (M1): The proportion of Mac (M1) cells also showed a significant decrease in Tumor tissue (p=0.0938). The median proportion in Tumor tissue was around 50-55%, slightly lower than the median of approximately 60-70% in Adj_normal tissue.
Overall, M2-like macrophage subsets (M2B, M2C) are enriched in tumor tissue, while other macrophage subsets (M2A, M1) are relatively diminished or less abundant.
Biological Interpretation
The observed shifts in macrophage proportions strongly suggest a significant remodeling of the immune microenvironment in colorectal cancer. Macrophages are highly plastic cells that can adopt various phenotypes, broadly categorized into M1 (pro-inflammatory, anti-tumor) and M2 (anti-inflammatory, pro-tumor) functional states, with M2 further sub-categorized (e.g., M2A, M2B, M2C, M2D).
The significant increase in Mac (M2B) and Mac (M2C) populations in the Tumor condition is particularly notable. M2-like macrophages, often referred to as Tumor-Associated Macrophages (TAMs), are known to play a crucial role in promoting tumor progression through various mechanisms, including:
- Immunosuppression: M2 macrophages can suppress anti-tumor immune responses by secreting immunosuppressive cytokines (e.g., IL-10, TGF-β) and expressing immune checkpoints.
- Angiogenesis: They contribute to new blood vessel formation, which is essential for tumor growth and metastasis.
- Tumor growth and metastasis: M2 macrophages can secrete growth factors and matrix metalloproteinases that facilitate tumor cell proliferation, invasion, and metastasis.
[Reference: PubMed search for "M2 macrophages cancer progression"]
Conversely, the decrease in Mac (M2A) and Mac (M1) populations in the tumor microenvironment is also biologically significant. M1 macrophages are traditionally associated with anti-tumor activity, characterized by their ability to present antigens, secrete pro-inflammatory cytokines (e.g., TNF-α, IL-12), and directly kill tumor cells. A reduction in their relative proportion suggests a dampened anti-tumor immune response. While M2A macrophages are generally involved in wound healing and allergic responses, their reduction in tumor tissue might indicate a shift away from these specific M2-like phenotypes towards others that are more directly supportive of cancer. The collective shift towards M2B/M2C dominance further highlights a pro-tumorigenic polarization of the macrophage compartment in colorectal cancer.
Clinical or Translational Implications
These findings have important clinical and translational implications for colorectal cancer:
- Biomarker Potential: The altered proportions of macrophage subsets, particularly the enrichment of M2B and M2C, could serve as potential biomarkers for colorectal cancer progression, prognosis, or even response to therapy. Monitoring these populations might offer insights into disease status.
- Therapeutic Targets: Macrophages, particularly TAMs, are increasingly recognized as attractive targets for cancer immunotherapy. Strategies aimed at re-polarizing pro-tumor M2-like macrophages to an anti-tumor M1-like phenotype, or depleting specific pro-tumorigenic macrophage subsets (like M2B/M2C), could enhance anti-tumor immunity and improve treatment outcomes in colorectal cancer.
[Reference: PubMed search for "macrophage reprogramming cancer therapy"]
- Understanding Immune Evasion: The observed macrophage polarization pattern contributes to our understanding of how colorectal tumors evade immune surveillance and promote their growth. Therapeutic approaches that disrupt this pro-tumorigenic macrophage shift could be crucial for overcoming resistance to existing immunotherapies.
Further research focusing on the specific functions and molecular mechanisms driving the observed polarization of these macrophage subsets in colorectal cancer would be valuable for developing targeted immunotherapeutic strategies.
11. Ploidy Status of Intestinal Epithelial Cells in Colorectal Cancer
[Analysis Visualization Results]...
Analysis Overview
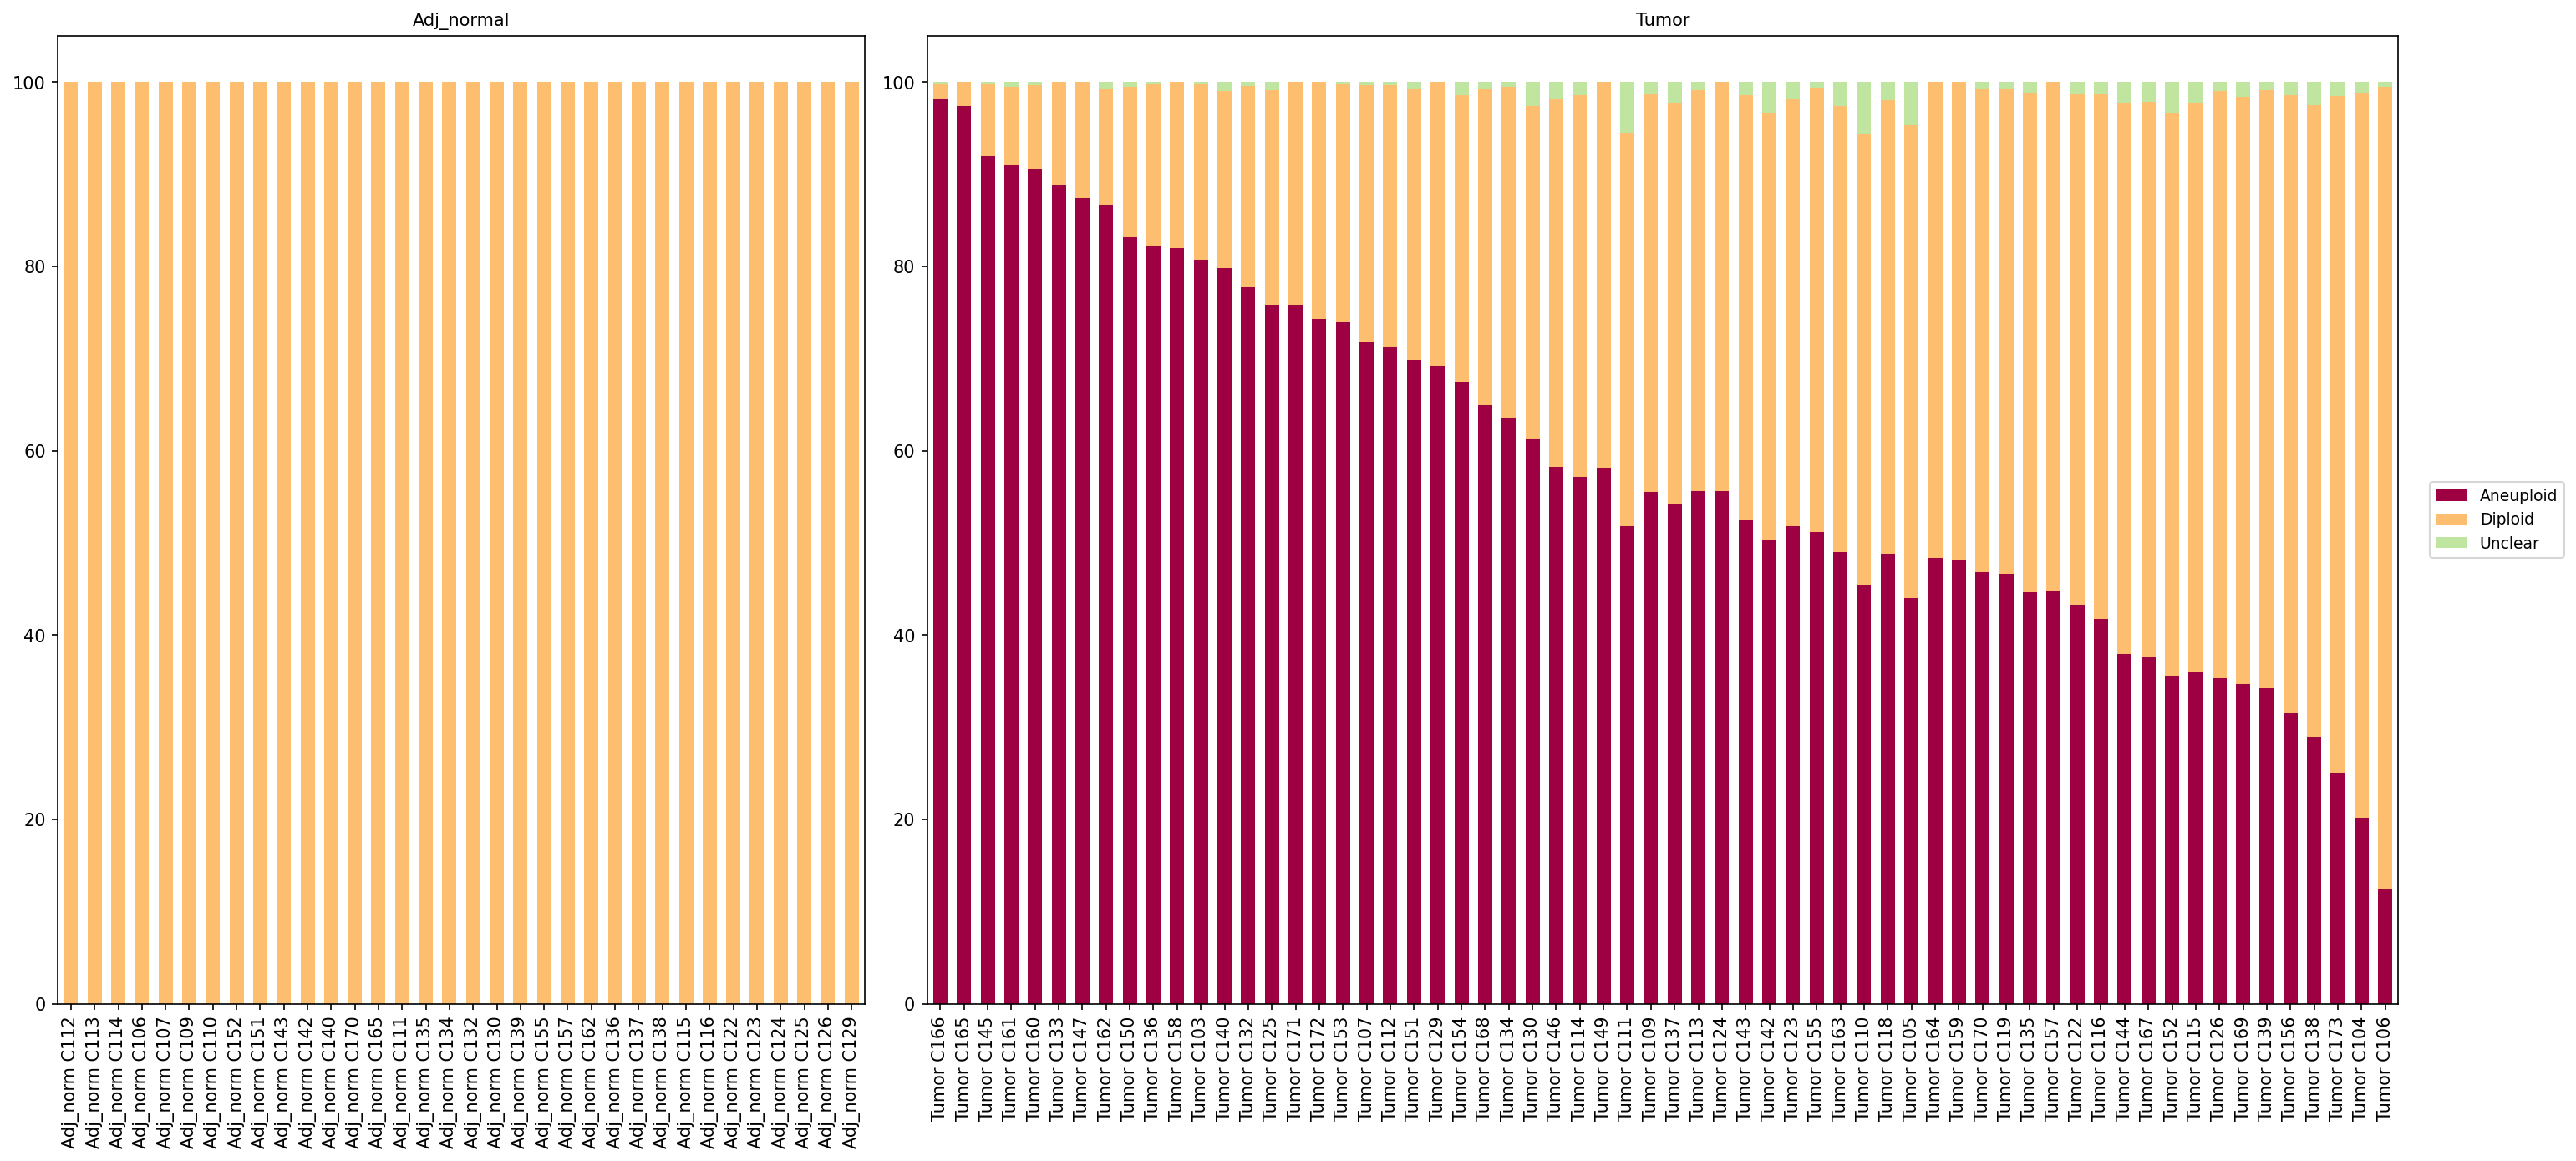
This analysis investigates the ploidy status (Aneuploid, Diploid, or Unclear) of Intestinal Epithelial cells, which have been identified as the tumor-origin cell type within the provided single-cell RNA-sequencing dataset. The ploidy status is evaluated across individual samples derived from both 'Adj_normal' (adjacent normal colon tissue) and 'Tumor' (colorectal tumor tissue) conditions. This comparison aims to highlight genomic stability differences characteristic of malignancy.
Visual Summary
The bar plots display the proportional distribution of ploidy populations within Intestinal Epithelial cells for each sample.
- Adjacent Normal Samples (Adj_normal): The left panel, representing 'Adj_normal' samples, shows a remarkably consistent pattern. Nearly all Intestinal Epithelial cells across all adjacent normal samples are classified as Diploid (orange bars, consistently reaching 100%). This indicates a high degree of genomic stability in healthy colon epithelial cells. There is a negligible presence of Aneuploid or Unclear cells.
- Tumor Samples (Tumor): The right panel, representing 'Tumor' samples, reveals a drastic shift in ploidy. A significant proportion of Intestinal Epithelial cells in these samples are Aneuploid (burgundy bars). The fraction of aneuploid cells varies considerably between different tumor samples, ranging from over 90% (e.g., Tumor C166, Tumor C165) to less than 20% (e.g., Tumor C106). Diploid cells (orange bars) are still present in tumor samples, but their proportion is generally reduced compared to normal tissue. A small fraction of "Unclear" cells (light green) is also noticeable in some tumor samples, though it remains a minor component.
Biological Interpretation
The observed ploidy patterns strongly corroborate the inferred biological context of colorectal cancer.
- Genomic Instability as a Hallmark of Cancer: The stark contrast in aneuploidy between 'Adj_normal' and 'Tumor' samples underscores genomic instability as a fundamental characteristic of colorectal cancer. Normal Intestinal Epithelial cells maintain a diploid state, whereas their malignant counterparts frequently acquire an abnormal number of chromosomes (aneuploidy) during tumor development and progression [PubMed Search].
- Confirmation of Tumor-Origin Cell Type: The high prevalence of aneuploidy specifically in the Intestinal Epithelial cells within tumor samples strongly supports their identification as the tumor-origin cell type. This genomic alteration is a direct consequence of the oncogenic processes driving cell transformation and uncontrolled proliferation.
- Inter-Patient Heterogeneity: The substantial variability in aneuploid proportions among different tumor samples highlights significant inter-patient heterogeneity. This suggests that colorectal cancers can differ widely in their degree of genomic instability, which may reflect different molecular subtypes, stages of progression, or unique evolutionary paths of individual tumors. Some tumors appear almost entirely aneuploid, while others retain a larger diploid fraction, possibly indicating different levels of tumor purity or varying degrees of genomic chaos.
- Coexistence of Ploidy States within Tumors: The presence of both aneuploid and diploid Intestinal Epithelial cells within tumor samples could reflect several biological scenarios. It might include residual normal epithelial cells infiltrated within the tumor mass, less transformed tumor cell subclones, or even adaptive plasticity where some tumor cells might transiently or stably revert to a diploid-like state under certain conditions.
Clinical or Translational Implications
These findings have several potential clinical and translational implications for colorectal cancer.
- Diagnostic and Prognostic Biomarker: The detection and quantification of aneuploid Intestinal Epithelial cells can serve as a robust biomarker for confirming malignancy and potentially for assessing tumor aggressiveness. A higher proportion of aneuploid cells might correlate with a more advanced or aggressive disease phenotype.
- Guidance for Personalized Medicine: The observed inter-patient heterogeneity in aneuploidy levels suggests that genomic stability profiles could be integrated into personalized medicine approaches. Patients with highly aneuploid tumors might respond differently to certain therapies (e.g., those targeting cell cycle checkpoints or DNA repair pathways) compared to those with tumors exhibiting lower aneuploidy.
- Monitoring and Therapeutic Targeting: Understanding the mechanisms driving aneuploidy in tumor epithelial cells could reveal vulnerabilities for therapeutic intervention. Therapies aimed at restoring genomic stability or exploiting the vulnerabilities associated with aneuploidy are an active area of research in cancer treatment [GeneCards]. Furthermore, monitoring ploidy changes in circulating tumor cells or during treatment could provide insights into disease response and recurrence.
12. Analysis of Cell-Cell Interaction Patterns in Colorectal Cancer
[Analysis Visualization Results]...
Analysis Overview
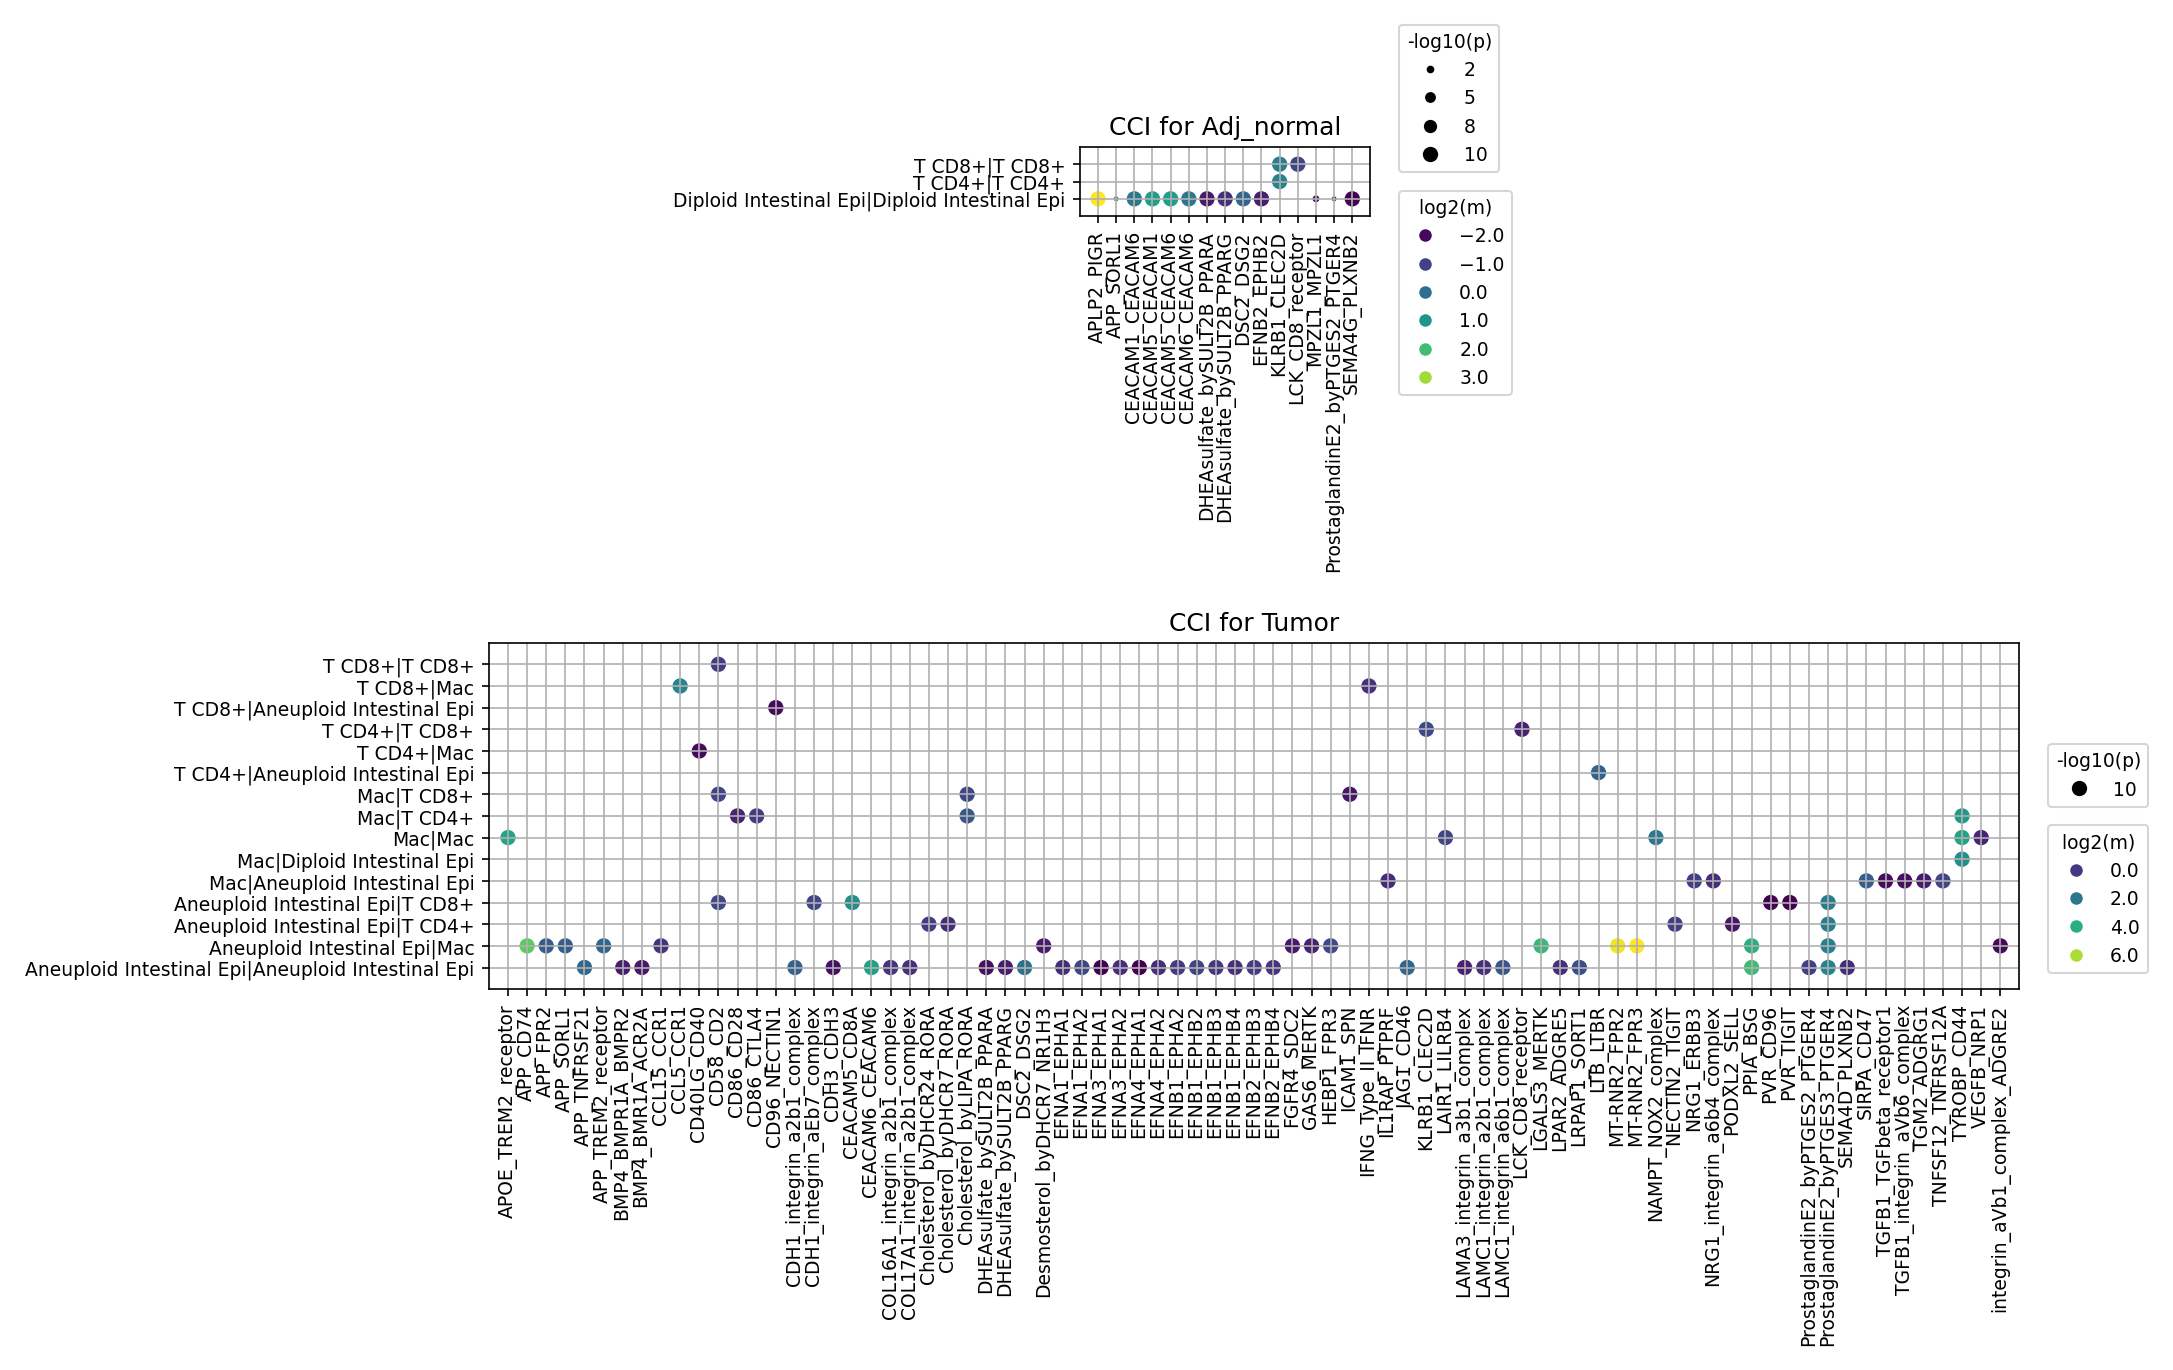
This analysis investigates cell-cell interaction (CCI) patterns using single-cell RNA-seq data from human colon tissue, comparing 'Adj_normal' (adjacent normal) and 'Tumor' conditions. The plot_cci_dots tool was used to visualize significant ligand-receptor interactions between key cell types involved in colorectal cancer (CRC) pathophysiology, including Intestinal Epithelial cells (tumor-origin cells), Fibroblasts, Macrophages, and T cells (CD4+ and CD8+). The analysis specifically expanded Intestinal Epithelial cells based on ploidy, distinguishing 'Diploid Intestinal Epi' in normal tissue and 'Aneuploid Intestinal Epi' in tumor tissue. The goal is to identify active communication pathways that are altered in the tumor microenvironment.
Visual Summary
The provided dot plots illustrate cell-cell interaction strengths and significances for 'Adj_normal' and 'Tumor' conditions, respectively. The size of each dot represents the -log10(p-value) (significance), and the color intensity reflects the log2(mean) expression of the ligand-receptor pair (interaction strength).
Key Observations:
- Complexity of Tumor Microenvironment: The 'Tumor' condition exhibits a dramatically higher number and diversity of significant cell-cell interactions compared to the 'Adj_normal' condition. The plot for 'Adj_normal' shows a sparse interaction landscape, primarily involving homotypic interactions, while the 'Tumor' plot is densely populated with both homotypic and heterotypic interactions.
- Dominant Cell Types in Tumor Interactions: In the tumor microenvironment, 'Aneuploid Intestinal Epi' cells (tumor cells) are central to a multitude of interactions, engaging with Macrophages, T CD4+ cells, and T CD8+ cells, in addition to extensive homotypic interactions. Macrophages also show a wide range of interactions with tumor cells and T cells.
Specific Interaction Patterns in Adj_normal:
- Homotypic interactions among 'Diploid Intestinal Epi' cells are prominent, involving cell adhesion molecules like CEACAM1, CEACAM5, CEACAM6, DSG2, and MPZL1. CEACAM6-CEACAM6 shows particularly strong expression and significance.
- Homotypic T cell interactions (T CD8+|T CD8+ and T CD4+|T CD4+) are also observed, with LCK_CD8_Tceptor and EFNB2_EPHB2 interactions.
- Fewer overall interactions, suggesting a more homeostatic and less dynamic communication network.
Specific Interaction Patterns in Tumor:
- Increased Homotypic Tumor Cell Interactions: 'Aneuploid Intestinal Epi' cells show highly significant and strong homotypic interactions, including CEACAM1-CEACAM1, CEACAM5-CEACAM5, CEACAM6-CEACAM6, various Integrin complexes (e.g., CDH1_integrin_a3B1_complex, Integrin_avB1_complex_ADGRE2, LAMA3_integrin_a2B1_complex), and DSC2-DSG2. This suggests altered adhesion and enhanced intrinsic signaling within the tumor cell population.
- Tumor-Immune Cell Crosstalk: Extensive interactions are observed between 'Aneuploid Intestinal Epi' cells and immune cells:
- With T CD4+ and T CD8+ cells: The PVR-TIGIT and PVR-CD226 axes are notable, indicating immune checkpoint involvement. TGFB1-TGFBR and CD40-CD40LG interactions are also present.
- With Macrophages: Strong SPP1-CD44, VEGF-VEGFR, and TGFB1-TGFBR interactions are evident, pointing to pro-tumorigenic macrophage functions.
- Macrophage-Immune Cell Interactions: Macrophages actively interact with T CD4+ and T CD8+ cells via pathways like PVR-TIGIT, SPP1-CD44, TGFB1-TGFBR, CD40-CD40LG, and IFN-gamma. These interactions are critical for shaping the immune response within the tumor.
- Abundant Integrin and CEACAM Signaling: Integrin-mediated interactions are pervasive across multiple cell-cell pairs in the tumor, suggesting extensive extracellular matrix remodeling and altered cell adhesion. CEACAMs also show sustained strong homotypic interactions in tumor cells.
- Absence of Fibroblast Interactions: Despite being a target_cell, fibroblasts do not appear as interacting partners in the top 80 interactions displayed for either condition, suggesting they may have fewer prominent direct ligand-receptor interactions with the selected cell types that meet the significance and strength cutoffs, or their key interactions fall outside the top selected pairs.
Biological Interpretation
The stark contrast in CCI patterns between adjacent normal and tumor tissue underscores the profound transformation of the cellular ecosystem in colorectal cancer.
- Remodeled Tumor Microenvironment (TME): The explosion of diverse and strong cell-cell interactions in the tumor is characteristic of a highly active and dysregulated TME. This complex network facilitates tumor growth, invasion, metastasis, and immune evasion.
- Tumor Cell-Intrinsic Signaling and Adhesion: The prominent homotypic interactions among 'Aneuploid Intestinal Epi' cells, particularly involving CEACAMs (CEACAM1, 5, 6) and various Integrins, highlight altered cell adhesion and potentially autonomous signaling that promotes tumor cell survival and proliferation. CEACAMs are known to be overexpressed in CRC and are implicated in cell adhesion, migration, and immune modulation [1, 2].
- Immune Evasion Mechanisms:
- PVR-TIGIT Axis: The detection of PVR (CD155) on tumor cells interacting with TIGIT on T cells (CD4+ and CD8+) is a significant finding. TIGIT is an inhibitory receptor on T cells that, upon binding to PVR, suppresses T cell activation and effector functions, contributing to immune evasion [3, 4]. PVR-CD226 interactions also occur, with CD226 typically promoting T cell activation, suggesting a complex interplay between activating and inhibitory signals.
- TGF-beta Signaling: The frequent observation of TGFB1-TGFBR interactions, particularly between tumor cells and immune cells (macrophages, T cells), points to a potent immunosuppressive microenvironment. TGF-beta is a pleiotropic cytokine that inhibits anti-tumor immunity, promotes fibrosis, and can induce epithelial-mesenchymal transition (EMT) [5].
- Pro-Tumorigenic Macrophage Functions: The strong interactions involving macrophages, especially with tumor cells (SPP1-CD44, VEGF-VEGFR) and T cells (SPP1-CD44, TGFB1-TGFBR), indicate their critical role in fostering tumor progression. SPP1 (Osteopontin) is known to promote tumor growth, angiogenesis, and macrophage polarization towards an M2 (pro-tumorigenic) phenotype [6]. VEGF-VEGFR signaling is crucial for angiogenesis, which supports tumor nutrient supply and waste removal, and can also directly suppress anti-tumor immunity.
- Extracellular Matrix (ECM) Remodeling and Invasion: The widespread involvement of various Integrin complexes across many cell-cell pairs in the tumor highlights extensive interactions with the ECM. Integrins mediate cell-ECM and cell-cell adhesion, and their altered expression and signaling are fundamental to tumor cell invasion, migration, and metastasis [7].
Clinical or Translational Implications
The identified cell-cell interaction patterns provide valuable insights for potential therapeutic strategies and biomarker discovery in colorectal cancer.
- Therapeutic Targeting of Immune Checkpoints: The prominence of the PVR-TIGIT axis involving tumor cells and T cells makes TIGIT a compelling immune checkpoint target. Blocking TIGIT could restore T cell anti-tumor activity, potentially in combination with other immunotherapies (e.g., anti-PD-1/PD-L1).
- Modulating Macrophage Activity: Given the extensive interactions involving macrophages, especially via SPP1-CD44 and VEGF-VEGFR, targeting these pathways could reprogram macrophages from a pro-tumorigenic M2-like state to an anti-tumorigenic M1-like state, or inhibit angiogenesis. Therapies targeting VEGF are already established in CRC, and targeting SPP1 is an emerging area.
- Inhibiting Pro-Tumorigenic Signaling: The ubiquitous presence of TGFB1-TGFBR signaling suggests that inhibiting the TGF-beta pathway could ameliorate immunosuppression, reduce fibrosis, and potentially slow tumor progression.
- Targeting Cell Adhesion and Invasion: The dysregulation of CEACAMs and Integrins highlights their potential as therapeutic targets to impede tumor cell adhesion, migration, and metastatic spread. For instance, CEACAM5 is a known target for antibody-drug conjugates (ADCs) in CRC [8].
- Biomarker Identification: Upregulated components of these key interaction pathways (e.g., expression levels of PVR, TIGIT, specific CEACAMs, SPP1, or TGFBRs) could serve as prognostic biomarkers or predictive markers for response to targeted therapies.
- Experimental Validation: The specific ligand-receptor pairs identified provide clear candidates for further functional studies in cell lines, organoids, or animal models to validate their mechanistic roles in CRC progression and to test the efficacy of therapeutic interventions.
---
References:
[1] GeneCards: CEACAM1. https://www.genecards.org/cgi-bin/carddisp.pl?gene=CEACAM1
[2] GeneCards: CEACAM5. https://www.genecards.org/cgi-bin/carddisp.pl?gene=CEACAM5
[3] PubMed Search: PVR TIGIT immune checkpoint cancer. https://pubmed.ncbi.nlm.nih.gov/?term=PVR+TIGIT+immune+checkpoint+cancer
[4] UniProt: TIGIT. https://www.uniprot.org/uniprot/W5XG18
[5] PubMed Search: TGF-beta immune suppression cancer. https://pubmed.ncbi.nlm.nih.gov/?term=TGF-beta+immune+suppression+cancer
[6] GeneCards: SPP1. https://www.genecards.org/cgi-bin/carddisp.pl?gene=SPP1
[7] PubMed Search: integrins cancer progression metastasis. https://pubmed.ncbi.nlm.nih.gov/?term=integrins+cancer+progression+metastasis
[8] PubMed Search: CEACAM5 antibody-drug conjugate colorectal cancer. https://pubmed.ncbi.nlm.nih.gov/?term=CEACAM5+antibody-drug+conjugate+colorectal+cancer
13. Cell-Cell Interaction Analysis of Immune Checkpoint and Cell Cycle Pathways in Colorectal Cancer
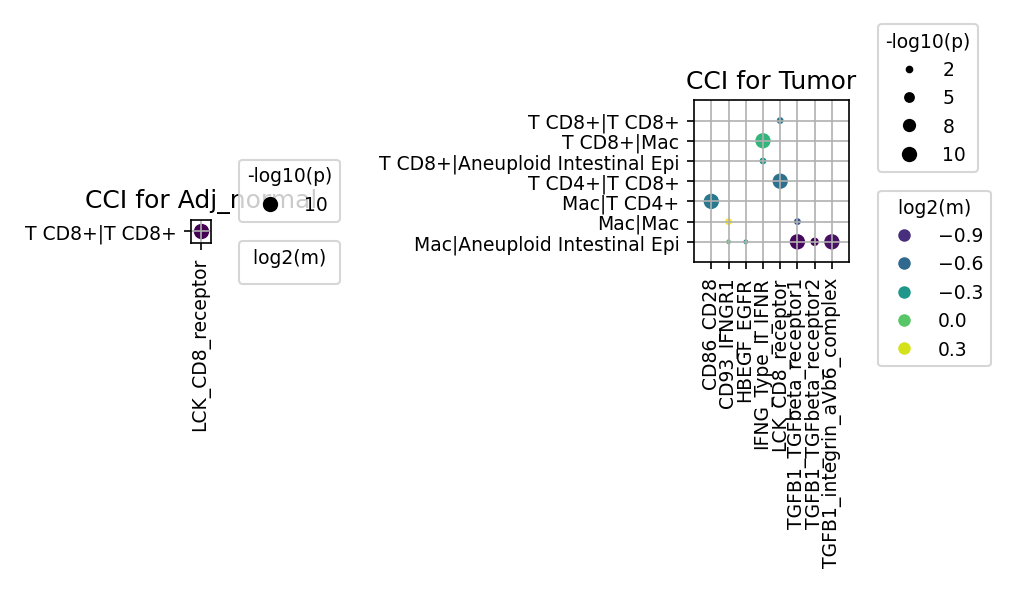
[Analysis Visualization Results]...
Analysis Overview
This analysis investigates cell-cell interactions (CCIs) involving a curated list of genes associated with immune checkpoint and cell cycle pathways in both tumor and adjacent normal colon tissues. Using CellPhoneDB, interactions between different cell types (celltype_minor level) were computed for these specific genes. The results are visualized as dot plots, where dot size represents the significance of the interaction (-log10(p-value)) and dot color indicates the interaction strength (log2(mean expression) of the interacting ligand-receptor pair). The primary goal is to identify active communication pathways related to tumor progression and immune modulation within the tumor microenvironment compared to normal tissue.
Visual Summary
The analysis generated two dot plots comparing CCIs in "Adj_normal" and "Tumor" conditions:
- Adjacent Normal Tissue (Adj_normal): The plot for adjacent normal tissue shows very few significant interactions involving the selected gene sets. Only one interaction, LCK_CD8_receptor within T CD8+|T CD8+ cells, is weakly visible, indicating minimal communication through these pathways in the normal colon microenvironment.
- Tumor Tissue (Tumor): In stark contrast, the tumor tissue plot reveals a rich and diverse landscape of cell-cell interactions.
- Increased Complexity: There is a significant increase in the number and strength of interactions across multiple cell-cell pairs compared to the adjacent normal tissue.
- Key Interacting Cell Types: Macrophages (Mac) and Aneuploid Intestinal Epithelial cells (Aneuploid Intestinal Epi), which are identified as the tumor-origin cells, emerge as central players.
Prominent Interactions involving Aneuploid Intestinal Epithelial cells:
- Macrophages show robust interactions with Aneuploid Intestinal Epithelial cells, particularly through TGFB1_TGFbeta_receptor, TGFB1_TGFbeta_receptor2, and TGFB1_integrin_avb6_complex. These interactions are among the strongest (largest dot size, intense purple color for negative log2(mean) indicating potentially lower expression in reference, or high expression in current condition relative to overall mean depending on specific mean calculation for CellPhoneDB).
- Macrophage-centric Interactions: Macrophages engage in self-interactions (Mac|Mac) primarily via TGFB1_TGFbeta_receptor and TGFB1_TGFbeta_receptor2, and also interact with T CD4+ cells through HBEGF_EGFR and TGFB1_TGFbeta_receptor.
T Cell Interactions:
- T CD8+|T CD8+ cells show self-interactions involving IFNG_IFNGR1 and LCK_CD8_receptor.
- T CD8+ cells also interact with Macrophages, notably through CD93_IFNGR1 and IFNG_IFNGR1.
- Co-stimulatory and Cytokine Signaling: CD86_CD28 (a co-stimulatory molecule pair) is observed between T CD8+ cells and Macrophages, and IFNG_IFNGR1 (Interferon-gamma signaling) is seen in T CD8+|T CD8+ and T CD8+|Mac interactions.
- Absence of specific inhibitory immune checkpoints: While the target gene list included classic inhibitory immune checkpoint genes (e.g., PDCD1/PD-1, CD274/PD-L1), direct interactions involving these specific pairs are not prominently displayed in this visualization under the applied cutoffs, suggesting they may not be among the most statistically significant or highly expressed interactions within this gene subset and cell type combinations.
Biological Interpretation
The striking difference in CCI profiles between adjacent normal and tumor tissues highlights the profound reprogramming of intercellular communication within the colorectal cancer microenvironment.
- Tumor Microenvironment Remodeling: The substantial increase in detected CCIs in the tumor indicates an active and complex communication network involving both cancer cells (Aneuploid Intestinal Epithelial cells) and immune cells (Macrophages, T cells). This is a hallmark of cancer progression, where cellular interactions drive immune evasion, proliferation, and metastasis.
- TGF-beta Signaling as a Central Hub: The most prominent interactions observed involve TGFB1 signaling, particularly between Macrophages and Aneuploid Intestinal Epithelial cells, as well as among Macrophages themselves. TGF-beta is a pleiotropic cytokine with context-dependent roles in cancer. In colorectal cancer, it often acts as a tumor suppressor in early stages but can promote tumor progression, immune suppression, and epithelial-mesenchymal transition (EMT) in advanced disease [1]. The strong TGFB1_integrin_avb6_complex interaction is particularly relevant, as Integrin αVβ6 is often upregulated in various cancers, including colorectal cancer, where it activates TGF-beta and contributes to tumor growth, invasion, and metastasis [2]. This suggests that tumor-associated macrophages (TAMs) might be actively promoting tumor progression and immune evasion through TGF-beta signaling in colorectal cancer.
Immune Cell Cross-talk:
- The IFNG_IFNGR1 interactions between T CD8+ cells and Macrophages suggest active immune responses, as IFN-gamma is a key cytokine produced by activated T cells and NK cells that can activate macrophages and orchestrate anti-tumor immunity. However, the overall context of TGF-beta dominance could imply a complex interplay, where pro-inflammatory signals are simultaneously dampened or redirected by immunosuppressive mechanisms.
- The CD86_CD28 interaction, a critical co-stimulatory signal for T cell activation, indicates active T-cell recognition and potential activation, but its effectiveness could be modulated by other inhibitory signals in the complex tumor microenvironment.
- EGFR Signaling: HBEGF_EGFR interactions between Macrophages and T CD4+ cells are notable. Epidermal Growth Factor Receptor (EGFR) signaling is a well-known driver of cell proliferation and survival in many cancers, including colorectal cancer. HBEGF (Heparin-binding EGF-like growth factor) is produced by various cells, including macrophages, and can promote cancer cell growth and angiogenesis through EGFR activation [3].
Clinical or Translational Implications
The findings from this CCI analysis have several potential clinical and translational implications for colorectal cancer:
- Therapeutic Target Prioritization: The prominence of TGF-beta signaling, especially the TGFB1_integrin_avb6_complex interaction between macrophages and tumor epithelial cells, suggests that targeting this pathway could be a promising therapeutic strategy. Agents that inhibit TGF-beta signaling or Integrin αVβ6 could potentially disrupt tumor-promoting communication and counteract immune suppression.
- Understanding Immune Evasion: The strong immunosuppressive potential of TGF-beta signaling in the tumor microenvironment may explain mechanisms of immune evasion in colorectal cancer. Combining TGF-beta pathway inhibitors with existing immunotherapies (e.g., PD-1/PD-L1 blockade, if these pathways are found to be active elsewhere or at different thresholds) could offer synergistic anti-tumor effects.
- Biomarker Development: The specific ligand-receptor pairs identified as highly active in the tumor, particularly those involving macrophages and aneuploid epithelial cells, could serve as potential biomarkers for disease progression, response to therapy, or patient stratification. For instance, the expression levels or activity of TGFB1, its receptors, or Integrin αVβ6 could be assessed in tumor biopsies.
- Further Investigation of Immune Checkpoints: While classic inhibitory immune checkpoint interactions were not prominent in this specific visualization, their presence in the comprehensive gene list suggests they are still relevant. Further investigations with broader cutoffs or different visualization strategies may be warranted to fully characterize the interplay between co-stimulatory, cytokine, and inhibitory immune checkpoint pathways in this context.
---
References:
[1] Moses, H. L., & Barcellos-Hoff, M. H. (2009). TGF-β in tumour suppression and cancer progression. *Nature Reviews Cancer*, 9(9), 665-675. PubMed Search: TGF-beta colorectal cancer
[2] Lobb, R. R., & Horizon Therapeutics. (2018). Integrin αvβ6 in cancer. *Cancers*, 10(11), 411. PubMed Search: Integrin alphaVbeta6 colorectal cancer
[3] Garrett, R. S., et al. (1989). Human heparin-binding EGF-like growth factor: cloning and biological properties. *Molecular and Cellular Biology*, 9(12), 5296-5301. GeneCards: HBEGF
14. Condition-Specific Cell-Cell Interaction Patterns in Colorectal Cancer
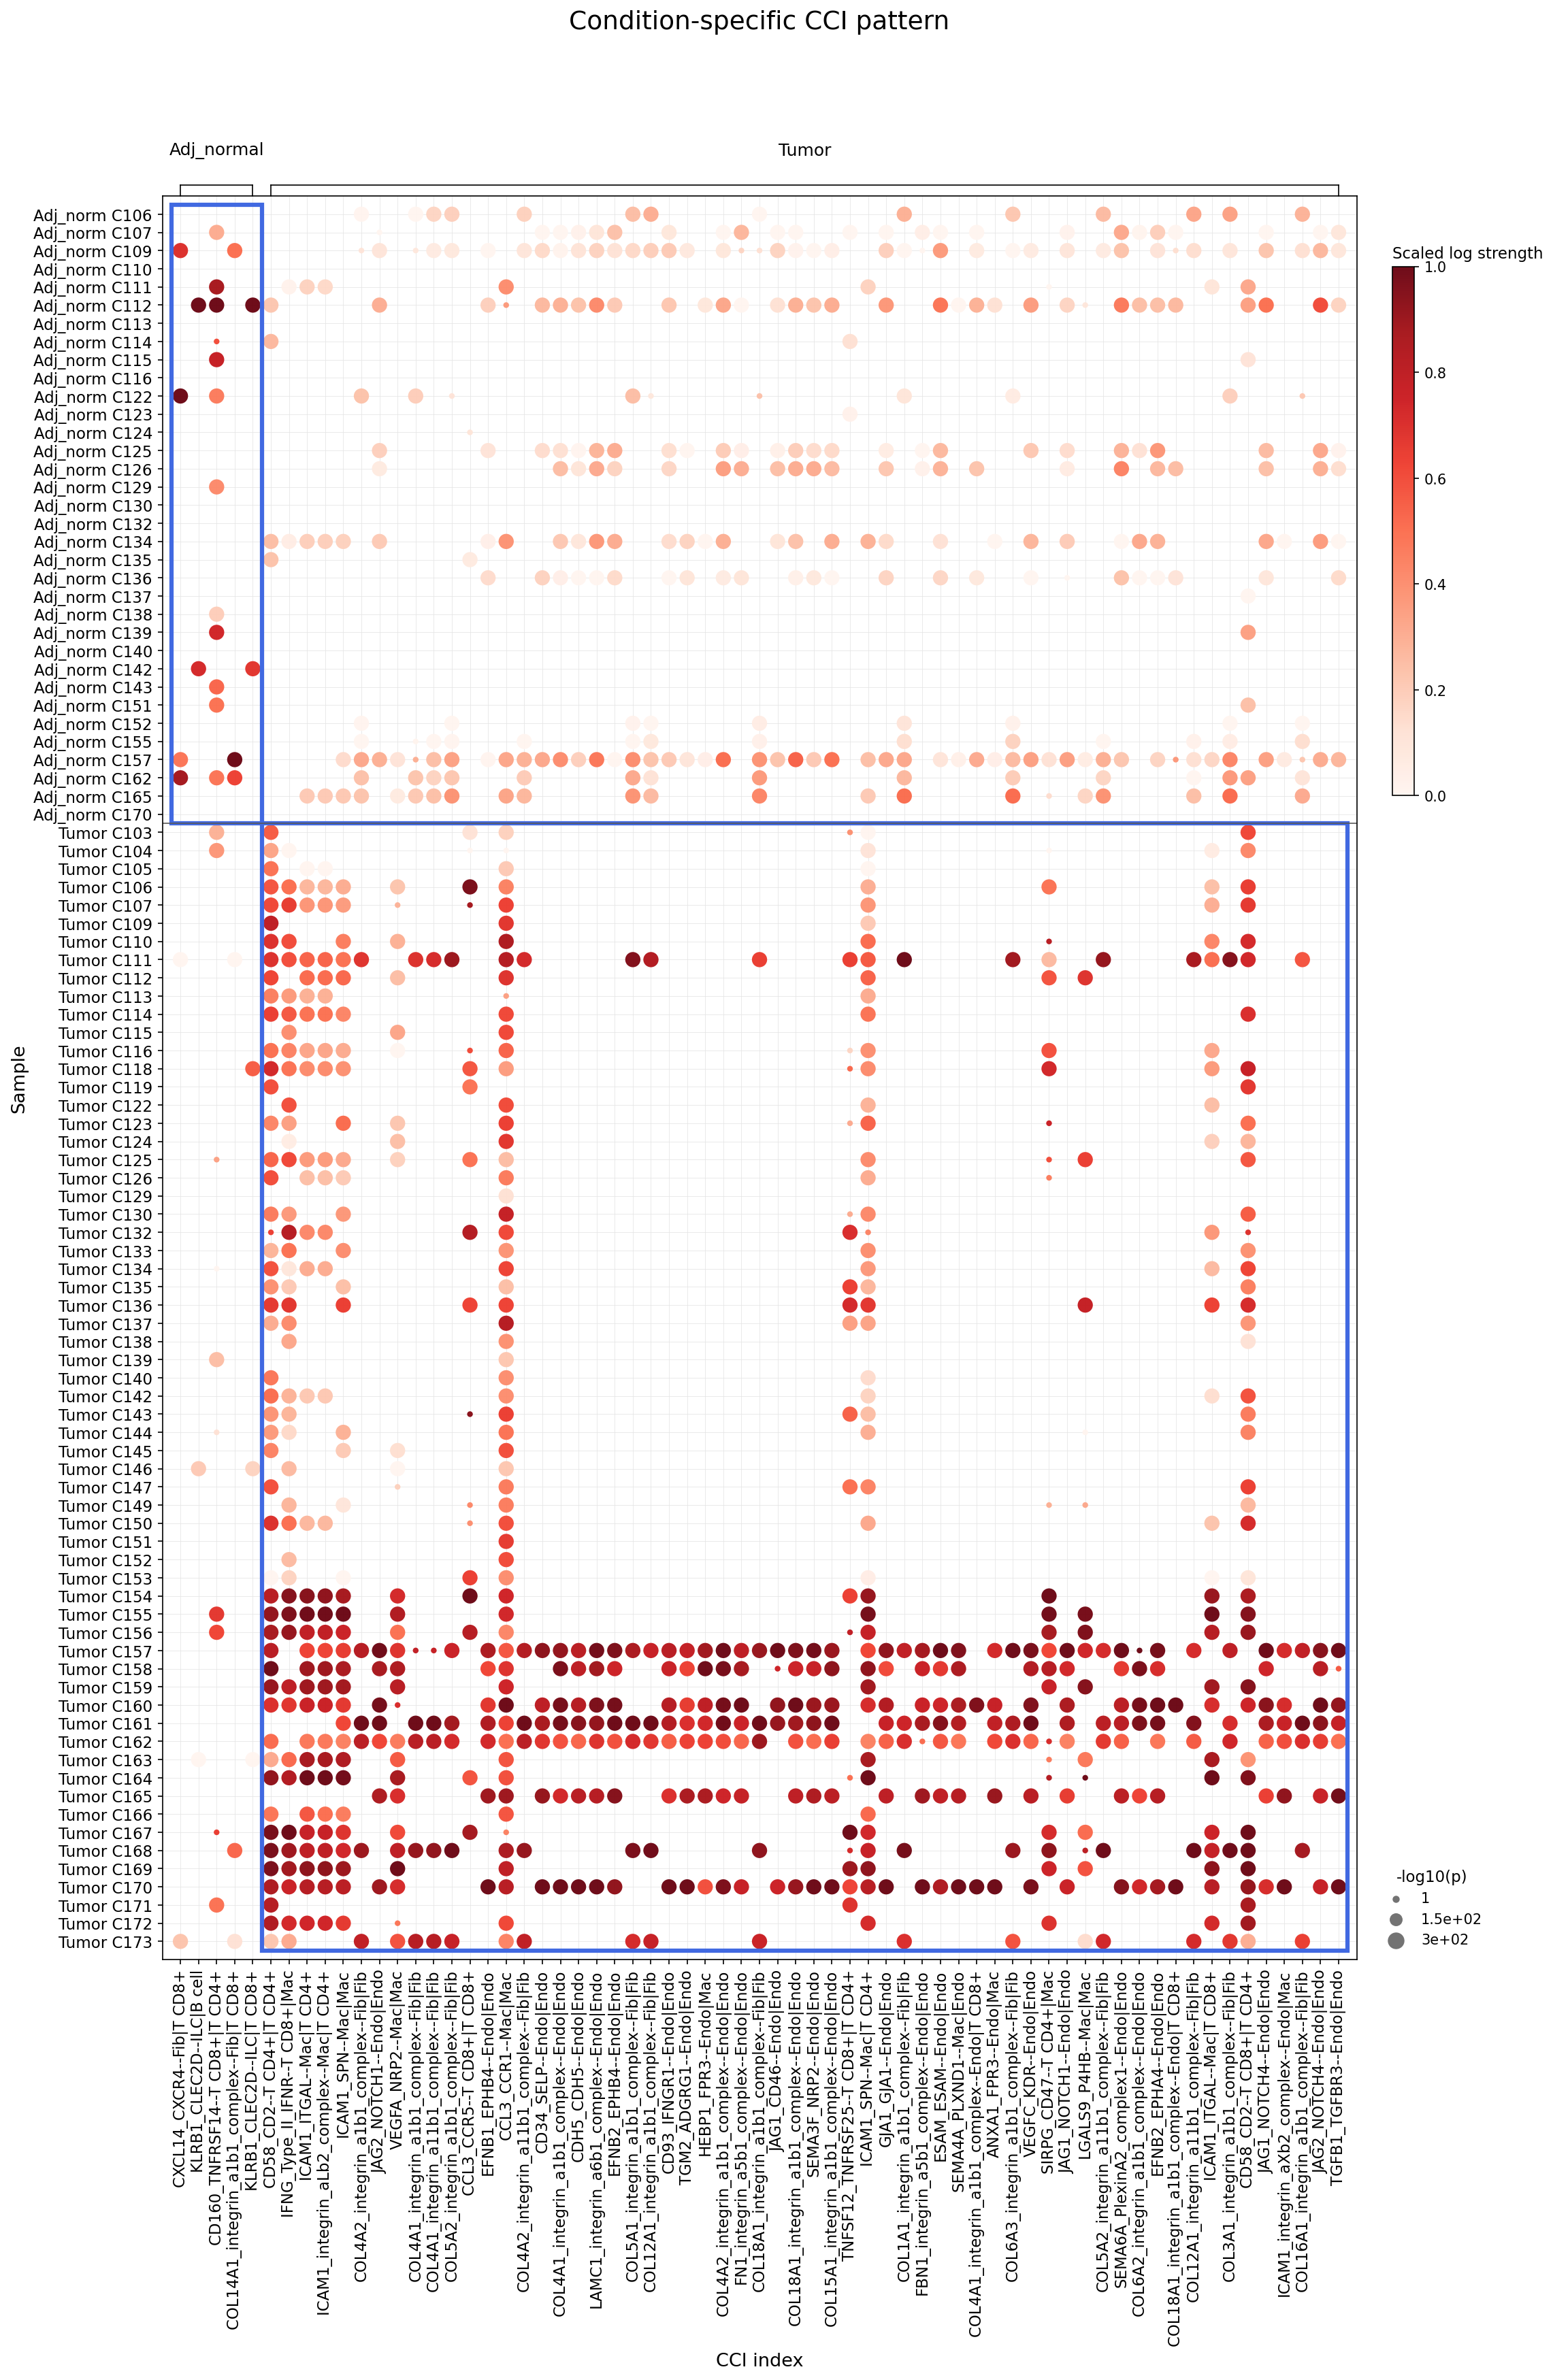
[Analysis Visualization Results]...
Analysis Overview
This analysis identifies cell-cell interactions (CCIs) involving major immune and stromal cell types that show significant differences between colorectal tumor (Tumor) and adjacent normal (Adj_normal) colon tissues. The dot plot visualizes the strength and significance of these interactions across individual samples, providing insights into how the cellular communication landscape changes in the tumor microenvironment. The analysis specifically focused on interactions involving Myeloid cells, T cells, Mast cells, B cells, Endothelial cells, and Stromal cells (Fibroblasts).
Visual Summary
The dot plot, titled "Condition-specific CCI pattern," clearly illustrates distinct cell-cell interaction profiles between Adj_normal and Tumor samples.
- Condition-Specific Patterns: There is a striking increase in both the strength (color intensity, darker red) and statistical significance (dot size, larger dots) of numerous cell-cell interactions within the 'Tumor' samples compared to the 'Adj_normal' samples. Interactions that are largely absent or show minimal activity in adjacent normal tissue become highly prominent and widespread in tumor samples.
- Dominant Tumor-Associated Interactions: A significant portion of the highly active interactions in tumor samples involve:
- Extracellular Matrix (ECM) components and Integrins: Interactions between various collagen (COL) and fibronectin (FN1) proteins with different integrin complexes (e.g., α1β1, α11β1, α5β1), predominantly observed between Fibroblasts (Fib) and Endothelial cells (Endo), as well as among Fibroblasts themselves.
- Angiogenesis and Lymphangiogenesis Regulators: Interactions such as VEGFC-KDR, EFNB2-EPHB4, JAG1-NOTCH1, JAG1-NOTCH4, and SEMA3F-NRP2, primarily occurring between Endothelial cells.
- Immune Cell Adhesion and Modulation: Interactions like ICAM1-integrin_aLb2_complex--Mac|T CD4+ and CD58-CD2--T CD4+|T CD8+, indicating enhanced adhesion and potential dysregulation of immune cell function.
- TGF-beta Signaling: TGFB1-TGFBR3 interactions, particularly between Endothelial cells, highlighting the activation of this critical pathway in the tumor microenvironment.
- Interactions in Adjacent Normal Tissue: While some baseline activity is observed for certain interactions in 'Adj_normal' samples (e.g., CXCL14-CXCR4--Fib|T CD8+), their overall number, strength, and significance are markedly lower compared to the 'Tumor' condition. The 'Adj_normal' section of the plot appears sparse with lighter-colored, smaller dots.
In summary, the visualization strongly suggests a profound reorganization and activation of numerous cell-cell communication pathways in the colorectal tumor microenvironment, particularly those related to ECM remodeling, angiogenesis, and immune cell modulation.
Biological Interpretation
The observed shifts in cell-cell interactions highlight key biological processes disrupted in colorectal cancer, involving critical communication axes between stromal and immune cells. Below, we detail representative interactions highly prominent in the Tumor condition and one from the Adjacent Normal condition, discussing their associated signaling pathways and mechanisms.
Interactions Upregulated in Tumor Condition
1. ECM-Integrin Interactions (e.g., COL1A1_integrin_a11b1_complex--Fib|Fib, FN1_integrin_a5b1_complex--Endo|Endo)
- Ligand-Receptor & Interacting Cells: A large cluster of interactions involves various collagen (e.g., COL1A1, COL4A1, COL12A1) and fibronectin (FN1) ligands binding to different integrin complexes (e.g., integrin_a11b1_complex, integrin_a1b1_complex, integrin_a5b1_complex). These predominantly occur between Fibroblasts and Endothelial cells, or among Fibroblasts themselves.
- Signaling Pathways & Mechanisms: These interactions are central to extracellular matrix (ECM) remodeling, cell adhesion, migration, and proliferation. In the tumor microenvironment (TME), cancer-associated fibroblasts (CAFs) actively deposit and remodel the ECM, increasing its stiffness and altering its composition, notably through increased collagen and fibronectin. Integrins, as transmembrane receptors, transduce mechanical and biochemical signals from the ECM into the cell, activating downstream pathways such as Focal Adhesion Kinase (FAK), Src, PI3K/Akt, and MAPK. This signaling promotes tumor cell survival, invasiveness, and resistance to therapy, while also supporting angiogenesis and modulating immune cell function. GeneCards: Integrin alpha 11, GeneCards: FN1
2. Angiogenesis/Lymphangiogenesis-related Interactions (e.g., VEGFC_KDR--Endo|Endo, EFNB2_EPHB4--Endo|Endo, JAG1_NOTCH1--Endo|Endo)
Ligand-Receptor & Interacting Cells:
- VEGFC-KDR (VEGFR2)--Endo|Endo: Vascular Endothelial Growth Factor C (VEGFC) interacting with Kinase Insert Domain Receptor (KDR, also known as VEGFR2) on Endothelial cells.
- EFNB2-EPHB4--Endo|Endo: Ephrin-B2 (EFNB2) interacting with its receptor EphB4 on Endothelial cells.
- JAG1-NOTCH1--Endo|Endo: Jagged1 (JAG1) interacting with Notch1 (NOTCH1) receptor on Endothelial cells.
- Signaling Pathways & Mechanisms: These interactions are critical drivers of angiogenesis (formation of new blood vessels) and lymphangiogenesis (formation of new lymphatic vessels), essential processes for tumor growth and metastasis.
- VEGFC-KDR: While VEGFC is primarily known for promoting lymphangiogenesis, KDR/VEGFR2 is a key receptor for both angiogenesis and lymphangiogenesis, mediating endothelial cell proliferation, migration, and survival.
- EFNB2-EPHB4: This signaling axis is crucial for regulating vascular development, arterial-venous identity, and lymphatic vessel maturation. In tumors, it promotes abnormal angiogenesis, enhancing blood supply to the tumor and facilitating metastasis.
- JAG1-NOTCH1: Notch signaling, activated by ligands like Jagged1, regulates endothelial cell fate, tip cell selection, and stalk cell proliferation during angiogenesis. Aberrant Notch activation in the TME contributes to uncontrolled vessel growth and can also support cancer stem cell properties.
These pathways collectively contribute to the formation of a dysfunctional tumor vasculature and lymphatic network, supporting tumor expansion and metastatic dissemination. PubMed search: tumor angiogenesis signaling pathways
3. Immune Cell Adhesion and Modulation (e.g., ICAM1_integrin_aLb2_complex--Mac|T CD4+)
- Ligand-Receptor & Interacting Cells: ICAM1 (Intercellular Adhesion Molecule 1) interacting with Integrin αLβ2 (LFA-1) on Macrophages and T cell CD4+ cells.
- Signaling Pathways & Mechanisms: This interaction is fundamental for immune cell adhesion, migration, and stable synapse formation between antigen-presenting cells (like macrophages) and T lymphocytes. It ensures efficient antigen recognition and T cell activation. In the TME, dysregulation of these adhesion molecules can influence immune cell infiltration, recruitment, and effector functions. Upregulated ICAM1 expression on tumor cells or stromal cells can facilitate immune cell extravasation but also, paradoxically, contribute to immune evasion by promoting tolerogenic interactions or facilitating tumor cell spread. GeneCards: ICAM1, UniProt: LFA-1 (ITGAL)
4. TGF-beta Signaling (e.g., TGFB1_TGFBR3--Endo|Endo)
- Ligand-Receptor & Interacting Cells: Transforming Growth Factor Beta 1 (TGFB1) interacting with TGF Beta Receptor 3 (TGFBR3) on Endothelial cells.
- Signaling Pathways & Mechanisms: TGF-beta is a pleiotropic cytokine with complex roles in cancer. While it acts as a tumor suppressor in early stages, it often switches to a tumor promoter in advanced disease, driving epithelial-mesenchymal transition (EMT), immune suppression, fibrosis, and angiogenesis. TGFBR3 acts as a co-receptor, modulating signaling initiated by TGFB1 binding to TGFBR1 and TGFBR2. Its activation on endothelial cells can contribute to the pro-angiogenic and pro-fibrotic environment within the tumor, fostering an immunosuppressive TME that allows cancer progression. GeneCards: TGFB1
Interactions in Adjacent Normal Condition
1. Chemokine Signaling (e.g., CXCL14_CXCR4--Fib|T CD8+)
- Ligand-Receptor & Interacting Cells: CXCL14 (Chemokine (C-X-C motif) Ligand 14) interacting with CXCR4 (C-X-C Motif Chemokine Receptor 4) on Fibroblasts and T cell CD8+ cells.
- Signaling Pathways & Mechanisms: This interaction, while present in some normal samples, typically plays a role in homeostatic immune cell trafficking and basal tissue surveillance. CXCR4 is a prominent chemokine receptor that mediates cell migration, and its interaction with CXCL14 can influence the recruitment of immune cells to specific tissue compartments. In normal tissue, this could be part of the mechanism for maintaining immune homeostasis. In cancer, CXCR4 is frequently overexpressed and is a key mediator of tumor cell migration and metastasis, though CXCL14's role in the tumor context can be complex, sometimes acting as a tumor suppressor by attracting anti-tumor immune cells. GeneCards: CXCR4
Clinical or Translational Implications
The significant upregulation of specific cell-cell interactions in colorectal tumor tissue compared to adjacent normal tissue highlights potential therapeutic vulnerabilities within the tumor microenvironment.
- Targeting ECM-Integrin Interactions:
- Potential as a Therapeutic Target: Disrupting the widespread collagen/fibronectin-integrin interactions can inhibit tumor cell adhesion, migration, invasion, and metastasis. It can also reduce ECM stiffness and density, potentially improving drug delivery and sensitizing tumor cells to chemotherapy or immunotherapy. Targeting cancer-associated fibroblasts (CAFs) that drive ECM remodeling is also a strategy.
- Relevant Therapeutic Agents: Integrin inhibitors, such as specific antibodies or small molecules that block collagen/fibronectin binding to integrins, are in development. For example, some integrin αvβ3/αvβ5 inhibitors (like Cilengitide) have been explored in various cancers. Strategies aimed at depleting or reprogramming CAFs are also actively being investigated.
- Targeting Angiogenesis and Lymphangiogenesis Pathways:
- Potential as a Therapeutic Target: Inhibiting the VEGFC-KDR, EFNB2-EPHB4, and JAG1-NOTCH1 axes is a well-established strategy to suppress tumor growth and metastasis by starving the tumor of oxygen and nutrients and limiting lymphatic spread.
- Relevant Therapeutic Agents: Anti-VEGF antibodies (e.g., Bevacizumab), multi-targeted receptor tyrosine kinase inhibitors (TKIs) that target VEGFR (e.g., Regorafenib, Sunitinib) are approved for various cancers, including colorectal cancer. Notch pathway inhibitors (e.g., Gamma-secretase inhibitors like Navicixizumab) and Ephrin/Eph receptor antagonists are also under active investigation. PubMed search: anti-angiogenic therapy colorectal cancer
- Modulating Immune Cell Adhesion:
- Potential as a Therapeutic Target: The altered ICAM1-integrin αLβ2 interaction indicates potential dysregulation of immune cell recruitment and function in the TME. Modulating such adhesion molecules could enhance anti-tumor immune responses by facilitating T cell infiltration and activation or by preventing immune evasion mechanisms.
- Relevant Therapeutic Agents: While direct targeting of ICAM1/LFA-1 is more common in inflammatory diseases (e.g., Efalizumab, although withdrawn), strategies to optimize immune cell trafficking and interaction within tumors are crucial for the success of immunotherapies. This could involve combining adhesion molecule modulators with checkpoint inhibitors or adoptive cell therapies.
- Targeting TGF-beta Signaling:
- Potential as a Therapeutic Target: Inhibiting the TGFB1-TGFBR3 pathway, which is highly active in the tumor, can counteract its pro-tumorigenic effects, including immune suppression, fibrosis, and EMT, thereby making the tumor more susceptible to other therapies.
- Relevant Therapeutic Agents: TGF-beta receptor kinase inhibitors (e.g., Galunisertib) and anti-TGF-beta antibodies (e.g., Fresolimumab) are in various stages of clinical development for different cancers. PubMed search: TGF beta inhibitor cancer therapy
In summary, the observed condition-specific CCI patterns in colorectal cancer point to a highly active and complex network of interactions within the TME that promotes tumor progression. Targeting these specific intercellular communication pathways offers promising avenues for novel therapeutic interventions.
15. Surfaceome Marker Expression in Intestinal Epithelial Cells of Colorectal Cancer
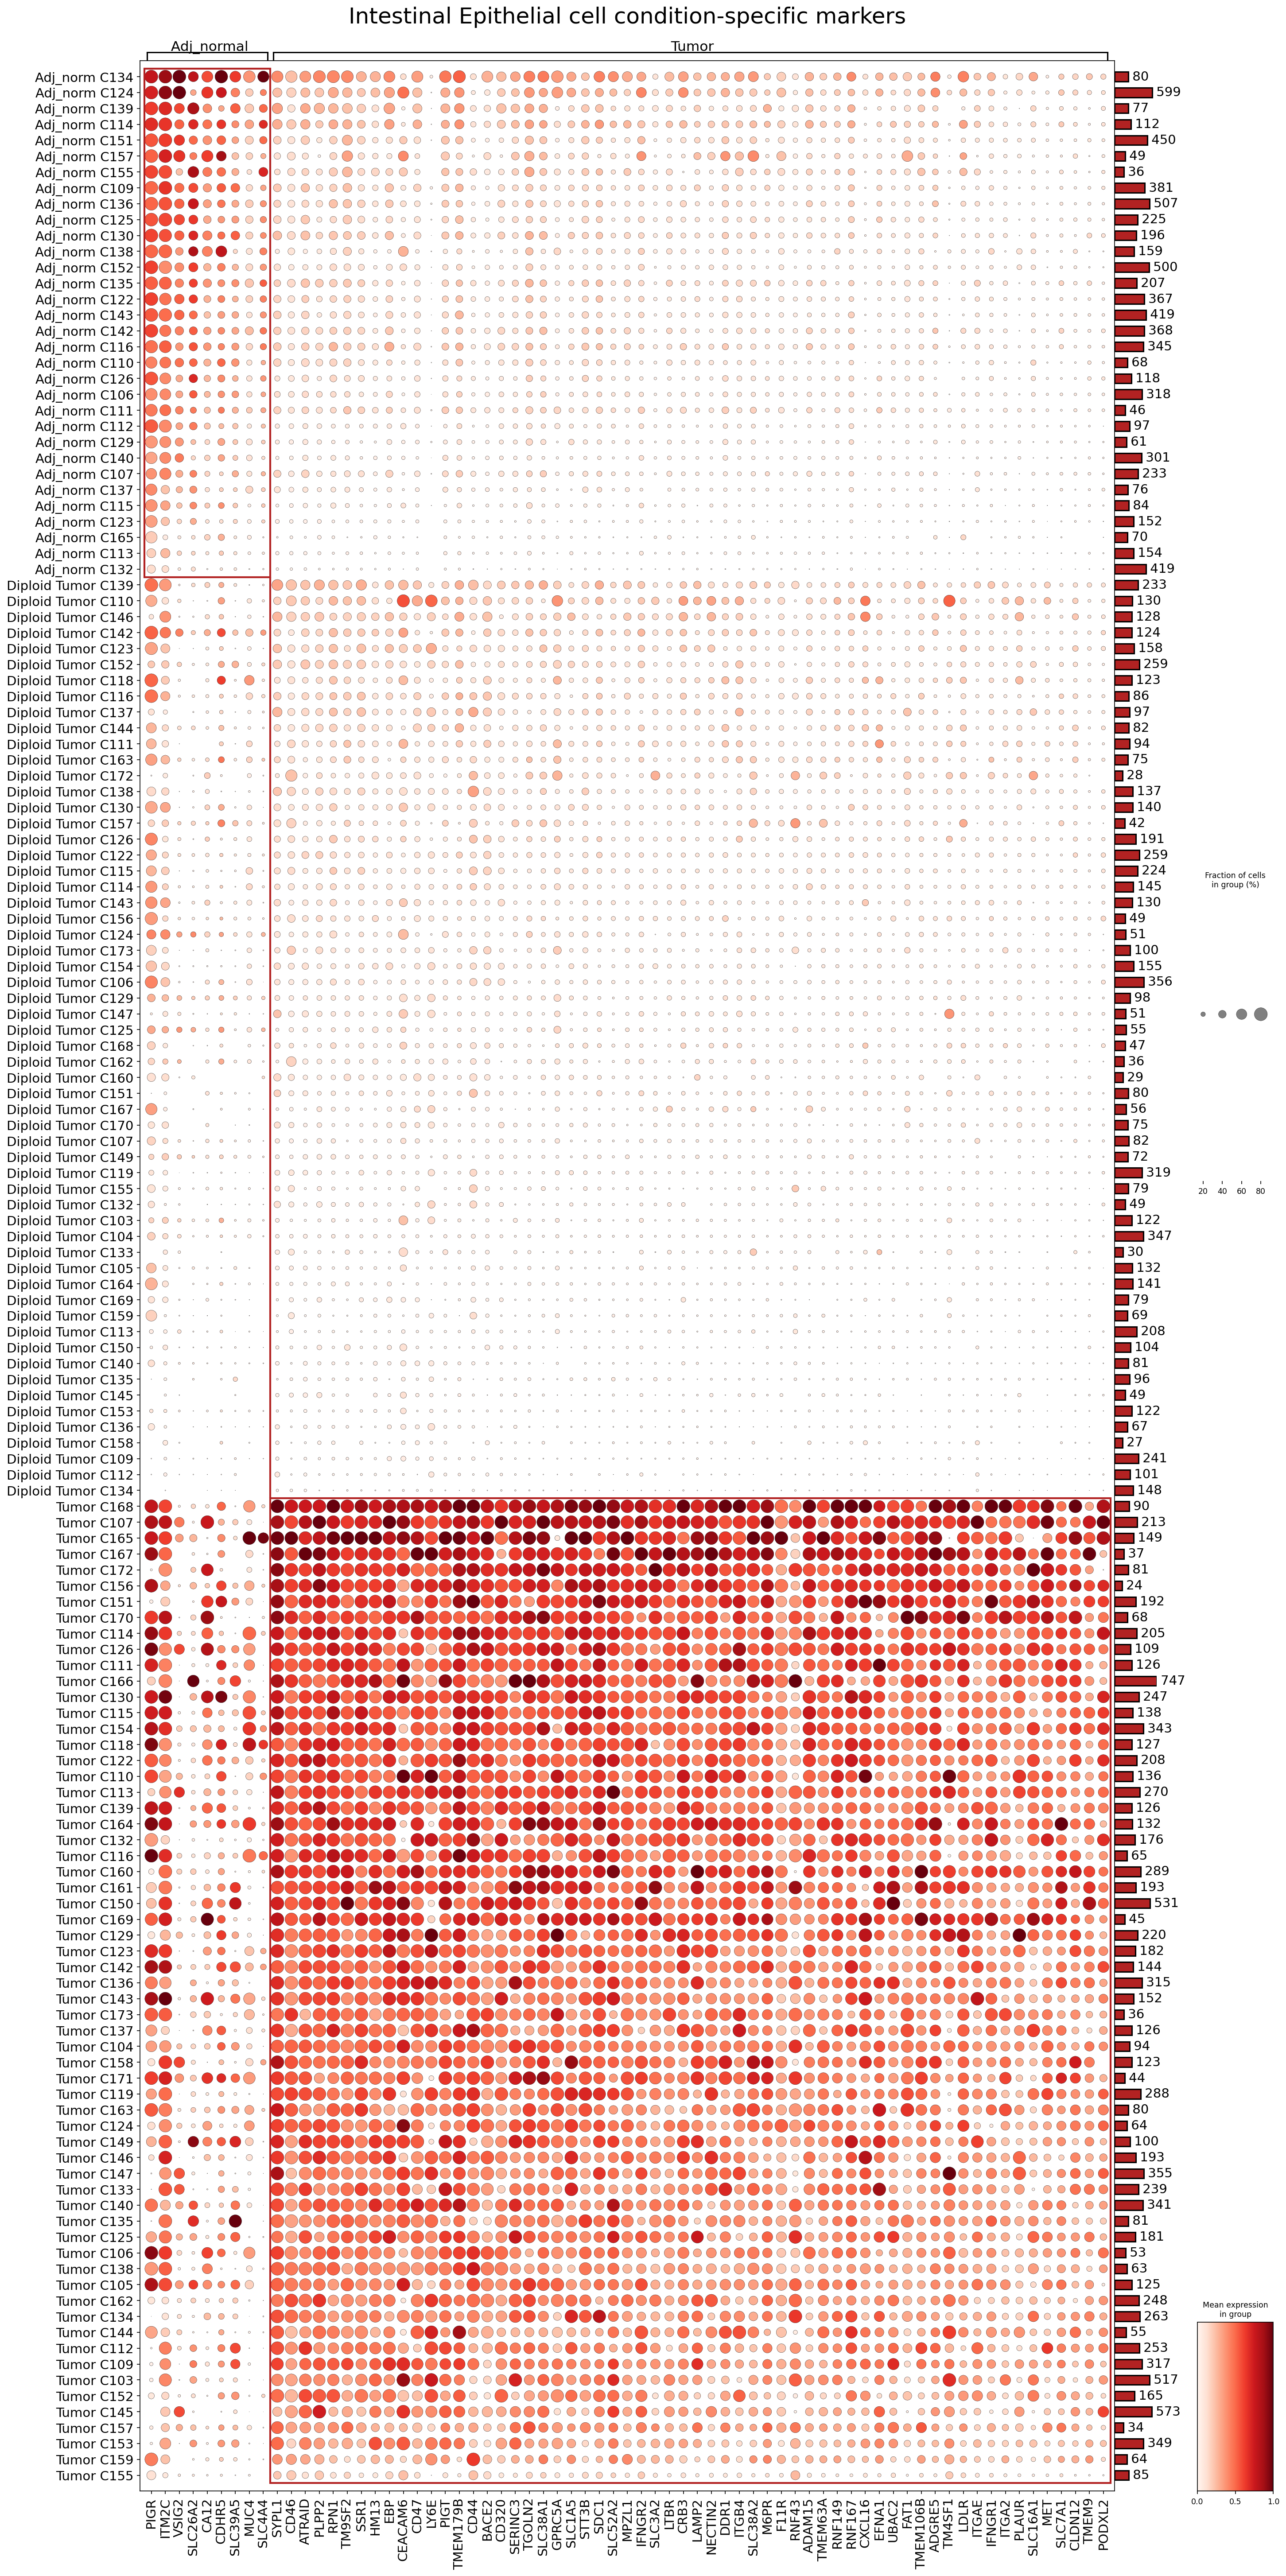
[Analysis Visualization Results]...
Analysis Overview
This analysis investigates the differential expression of surfaceome markers in Intestinal Epithelial cells across different conditions: 'Adj_normal' (adjacent normal tissue), 'Diploid Tumor' (tumor cells with diploid ploidy), and 'Tumor' (tumor cells with aneuploid or general tumor characteristics). The goal is to identify condition-specific surface markers, particularly those upregulated in tumor cells, which may represent established or potential therapeutic targets for colorectal cancer (CRC). The dot plot visualizes the mean expression level (color intensity) and the fraction of cells expressing each marker (dot size) for each sample.
Visual Summary
The dot plot clearly differentiates surfaceome marker profiles among the three conditions for Intestinal Epithelial cells.
- Adj_normal-specific Markers: A distinct cluster of markers (e.g., PIGR, ITM2C, VSIG2, SLC26A2, CA12, CDHR5, SLC39A5, MUCA4, SLC4A4, SYPL1, CD46, ATRAID, PLPP2) is highly expressed and detected in a large fraction of cells within the 'Adj_normal' group. These markers are notably absent or expressed at very low levels in both 'Diploid Tumor' and 'Tumor' cell populations, indicating a loss of normal epithelial cell identity or function during tumorigenesis.
- Tumor-specific Markers: The 'Tumor' group exhibits a striking upregulation of a broad panel of surfaceome markers (e.g., CEACAM5, CD47, CD44, MET, PLAUR, SDC1, SLC1A5, PODXL2, LY6E, ITGB4, GPRC5A). These markers show high mean expression and are present in a substantial fraction of tumor cells across most samples. Their expression is largely absent or minimal in 'Adj_normal' samples.
- Diploid Tumor Profile: The 'Diploid Tumor' cell population presents an intermediate and somewhat heterogeneous expression pattern. While largely lacking the 'Adj_normal'-specific markers, they also show generally lower expression and lower cell fraction of many 'Tumor'-specific markers compared to the main 'Tumor' group. This intermediate profile could suggest evolving tumorigenic processes in diploid tumor cells, possibly representing early transformation or a distinct subpopulation with less aggressive features compared to aneuploid tumor cells. Some 'Diploid Tumor' samples do show emerging expression of 'Tumor'-associated markers, albeit less uniformly than in the 'Tumor' group.
Biological Interpretation
The observed differential expression patterns highlight the profound cellular changes that occur in Intestinal Epithelial cells during colorectal cancer progression. The loss of 'Adj_normal'-specific markers like PIGR and MUCA4, which are involved in mucosal immunity and epithelial differentiation respectively, suggests a dedifferentiation process or disruption of normal colon function in tumor cells.
Conversely, the widespread and robust upregulation of numerous surfaceome proteins in the 'Tumor' group points to altered cell adhesion, signaling, metabolism, and immune evasion mechanisms that are characteristic of malignancy. These tumor-enriched markers are often implicated in key cancer hallmarks, including sustained proliferative signaling, resistance to cell death, induction of angiogenesis, activation of invasion and metastasis, and evasion of immune destruction. The heterogeneity and intermediate profile of 'Diploid Tumor' cells may indicate the dynamic nature of tumor evolution, where cells acquire oncogenic features over time, possibly undergoing ploidy changes as part of this progression. The clear distinction between 'Adj_normal' and 'Tumor' populations based on these surface markers provides strong evidence for their potential utility in diagnosis, prognosis, and therapeutic intervention.
Clinical or Translational Implications
The identified tumor-specific surface markers offer compelling candidates for therapeutic targeting and diagnostic/prognostic applications in colorectal cancer. These markers can be broadly categorized into established therapeutic targets with available agents and less well-characterized markers with high potential for future therapeutic development.
Established Therapeutic Targets and Promising Candidates
Several highly expressed surface markers in Intestinal Epithelial tumor cells are either validated therapeutic targets in cancer or are actively being investigated:
- CEACAM5 (Carcinoembryonic Antigen-related Cell Adhesion Molecule 5)
- Signaling/Mechanism: A glycosylphosphatidylinositol-anchored cell surface glycoprotein involved in cell adhesion, signal transduction, and modulation of immune responses. Highly expressed in adenocarcinomas, it promotes cell proliferation, survival, and metastasis. GeneCards: CEACAM5
- Therapeutic Agents: Monoclonal antibodies (e.g., zolbetuximab, tusamitamab ravtansine) targeting CEACAM5 are in clinical trials for various cancers, including CRC, showing promise as antibody-drug conjugates or immune checkpoint modulators. PubMed search: CEACAM5 colorectal cancer therapy
- Supporting Evidence: CEACAM5 is a well-established diagnostic and prognostic biomarker for CRC and is associated with poor prognosis and advanced disease. Its high expression in the tumor cells makes it a prime candidate for targeted therapies.
CD47 (Cluster of Differentiation 47)
- Signaling/Mechanism: A transmembrane protein that interacts with SIRPα (Signal Regulatory Protein Alpha) on myeloid cells, delivering a "don't eat me" signal that inhibits phagocytosis by macrophages. Its overexpression allows cancer cells to evade immune surveillance. UniProt: CD47
- Therapeutic Agents: Anti-CD47 antibodies (e.g., magrolimab, lemzoparlimab) are being developed to block this immune checkpoint, promoting phagocytosis of cancer cells. These agents are in various stages of clinical trials for solid tumors and hematological malignancies. PubMed search: CD47 cancer immunotherapy
- Supporting Evidence: CD47 overexpression is observed in many cancers, including CRC, and is associated with tumor progression and metastasis. Targeting CD47 has shown efficacy in preclinical models and early clinical trials.
CD44 (Cluster of Differentiation 44)
- Signaling/Mechanism: A transmembrane glycoprotein that acts as a receptor for hyaluronic acid and other ligands. It is involved in cell-cell adhesion, cell migration, proliferation, and differentiation. Specific splice variants (e.g., CD44v6) are linked to cancer stem cell properties, metastasis, and drug resistance. GeneCards: CD44
- Therapeutic Agents: Monoclonal antibodies targeting CD44 or its specific isoforms (e.g., bivatuzumab mertansine targeting CD44v6) have been explored, though challenges with toxicity and efficacy remain. Research into CD44-targeted therapies, including antibody-drug conjugates and small molecule inhibitors, is ongoing. PubMed search: CD44 colorectal cancer therapy
- Supporting Evidence: CD44 is widely recognized as a cancer stem cell marker in CRC, correlating with disease recurrence, metastasis, and resistance to conventional therapies.
MET (MET Proto-Oncogene, Receptor Tyrosine Kinase)
- Signaling/Mechanism: The receptor for hepatocyte growth factor (HGF), MET activation leads to downstream signaling pathways (e.g., PI3K/Akt, MAPK/ERK) that promote cell proliferation, survival, invasion, angiogenesis, and metastasis. Constitutive activation or overexpression of MET is a known oncogenic driver. UniProt: MET
- Therapeutic Agents: Small molecule MET kinase inhibitors (e.g., crizotinib, capmatinib, tepotinib) and anti-HGF/MET antibodies are approved or in clinical development for various cancers, including those with MET alterations. PubMed search: MET inhibitor colorectal cancer
- Supporting Evidence: MET amplification and overexpression are observed in a subset of CRC cases, contributing to tumor progression and resistance to anti-EGFR therapies.
SLC1A5 (Solute Carrier Family 1 Member 5 / ASCT2)
- Signaling/Mechanism: A neutral amino acid transporter (alanine, serine, cysteine, threonine) crucial for cellular uptake of glutamine, a vital nutrient for rapidly proliferating cancer cells. Its activity supports increased anabolism and energy production necessary for tumor growth. GeneCards: SLC1A5
- Therapeutic Agents: Inhibitors targeting glutamine metabolism, including ASCT2 inhibitors, are under investigation as potential anti-cancer agents to starve tumor cells. PubMed search: ASCT2 inhibitor cancer
- Supporting Evidence: Upregulation of SLC1A5 is a common feature in many cancers, including CRC, linking directly to altered cancer cell metabolism and proliferation.
Less Well-Characterized Markers with Potential as Therapeutic Targets
PODXL2 (Podocalyxin Like 2)
- Signaling/Mechanism: A sialomucin that can influence cell adhesion, migration, and invasion, similar to its paralog PODXL (podocalyxin). It is suggested to play a role in maintaining cancer stem cell properties and promoting metastatic potential by modulating cytoskeletal organization and cell-matrix interactions. GeneCards: PODXL2
- Therapeutic Agents: Currently, there are no specific therapeutic agents targeting PODXL2. However, given its structural and functional similarity to PODXL, which is recognized as an oncofetal antigen and a prognostic marker in several cancers, PODXL2 represents a potential novel target.
- Supporting Evidence: Overexpression of PODXL2 has been reported in various cancers, often correlating with aggressive phenotypes and poor prognosis. Its consistent upregulation in CRC intestinal epithelial tumor cells warrants further investigation into its precise role and druggability.
PIGR (Polymeric Immunoglobulin Receptor)
- Signaling/Mechanism: Responsible for transcytosis of polymeric immunoglobulins (IgA and IgM) across epithelial cells into the lumen, playing a critical role in mucosal immunity. Loss of PIGR expression disrupts mucosal barrier function and immune surveillance. UniProt: PIGR
- Therapeutic Agents: PIGR itself is not typically a therapeutic target in cancer; rather, its loss can be a marker of altered epithelial function. However, restoring its function or exploiting its absence might be considered in strategies that aim to enhance local immune responses or normalize epithelial differentiation.
- Supporting Evidence: The observed downregulation or loss of PIGR in Intestinal Epithelial tumor cells is consistent with findings in CRC literature, where its loss is associated with tumor progression, poorer differentiation, and altered immune microenvironment. This makes PIGR a potential diagnostic or prognostic indicator of epithelial transformation.
Experimental Validation Implications
The strong and distinct expression patterns observed for these markers suggest several avenues for experimental validation:
- Immunohistochemistry (IHC) / Immunofluorescence (IF): Confirm protein expression and localization of selected markers in primary CRC tissue sections versus adjacent normal tissue. This can validate the single-cell RNA-seq findings at the protein level and assess spatial heterogeneity.
- Flow Cytometry: Validate surface expression of key markers (e.g., CD47, CD44, CEACAM5) on dissociated tumor cells or organoids derived from CRC patients to identify and isolate specific cell populations.
- Functional Studies: For tumor-upregulated markers, perform *in vitro* (cell lines, organoids) and *in vivo* (xenograft models) studies to investigate the functional consequences of marker overexpression or knockdown/knockout on cell proliferation, migration, invasion, and drug sensitivity.
- Targeted Therapeutic Efficacy: Evaluate the efficacy of existing or novel therapeutic agents targeting the identified established markers (e.g., anti-CD47 antibodies, MET inhibitors) in CRC models. For potential targets, validate their therapeutic potential through antibody or small molecule development.
- Biomarker Utility: Assess the diagnostic and prognostic value of panels of these markers, particularly the 'Adj_normal'-specific markers whose loss could indicate early transformation, or 'Tumor'-specific markers for staging and recurrence risk.
In conclusion, this analysis provides a rich dataset of surfaceome markers that are highly differentially expressed in colorectal cancer Intestinal Epithelial cells, offering significant opportunities for developing new diagnostic tools and targeted therapies.
16. Macrophage Condition-Specific Surfaceome Markers in Colorectal Cancer
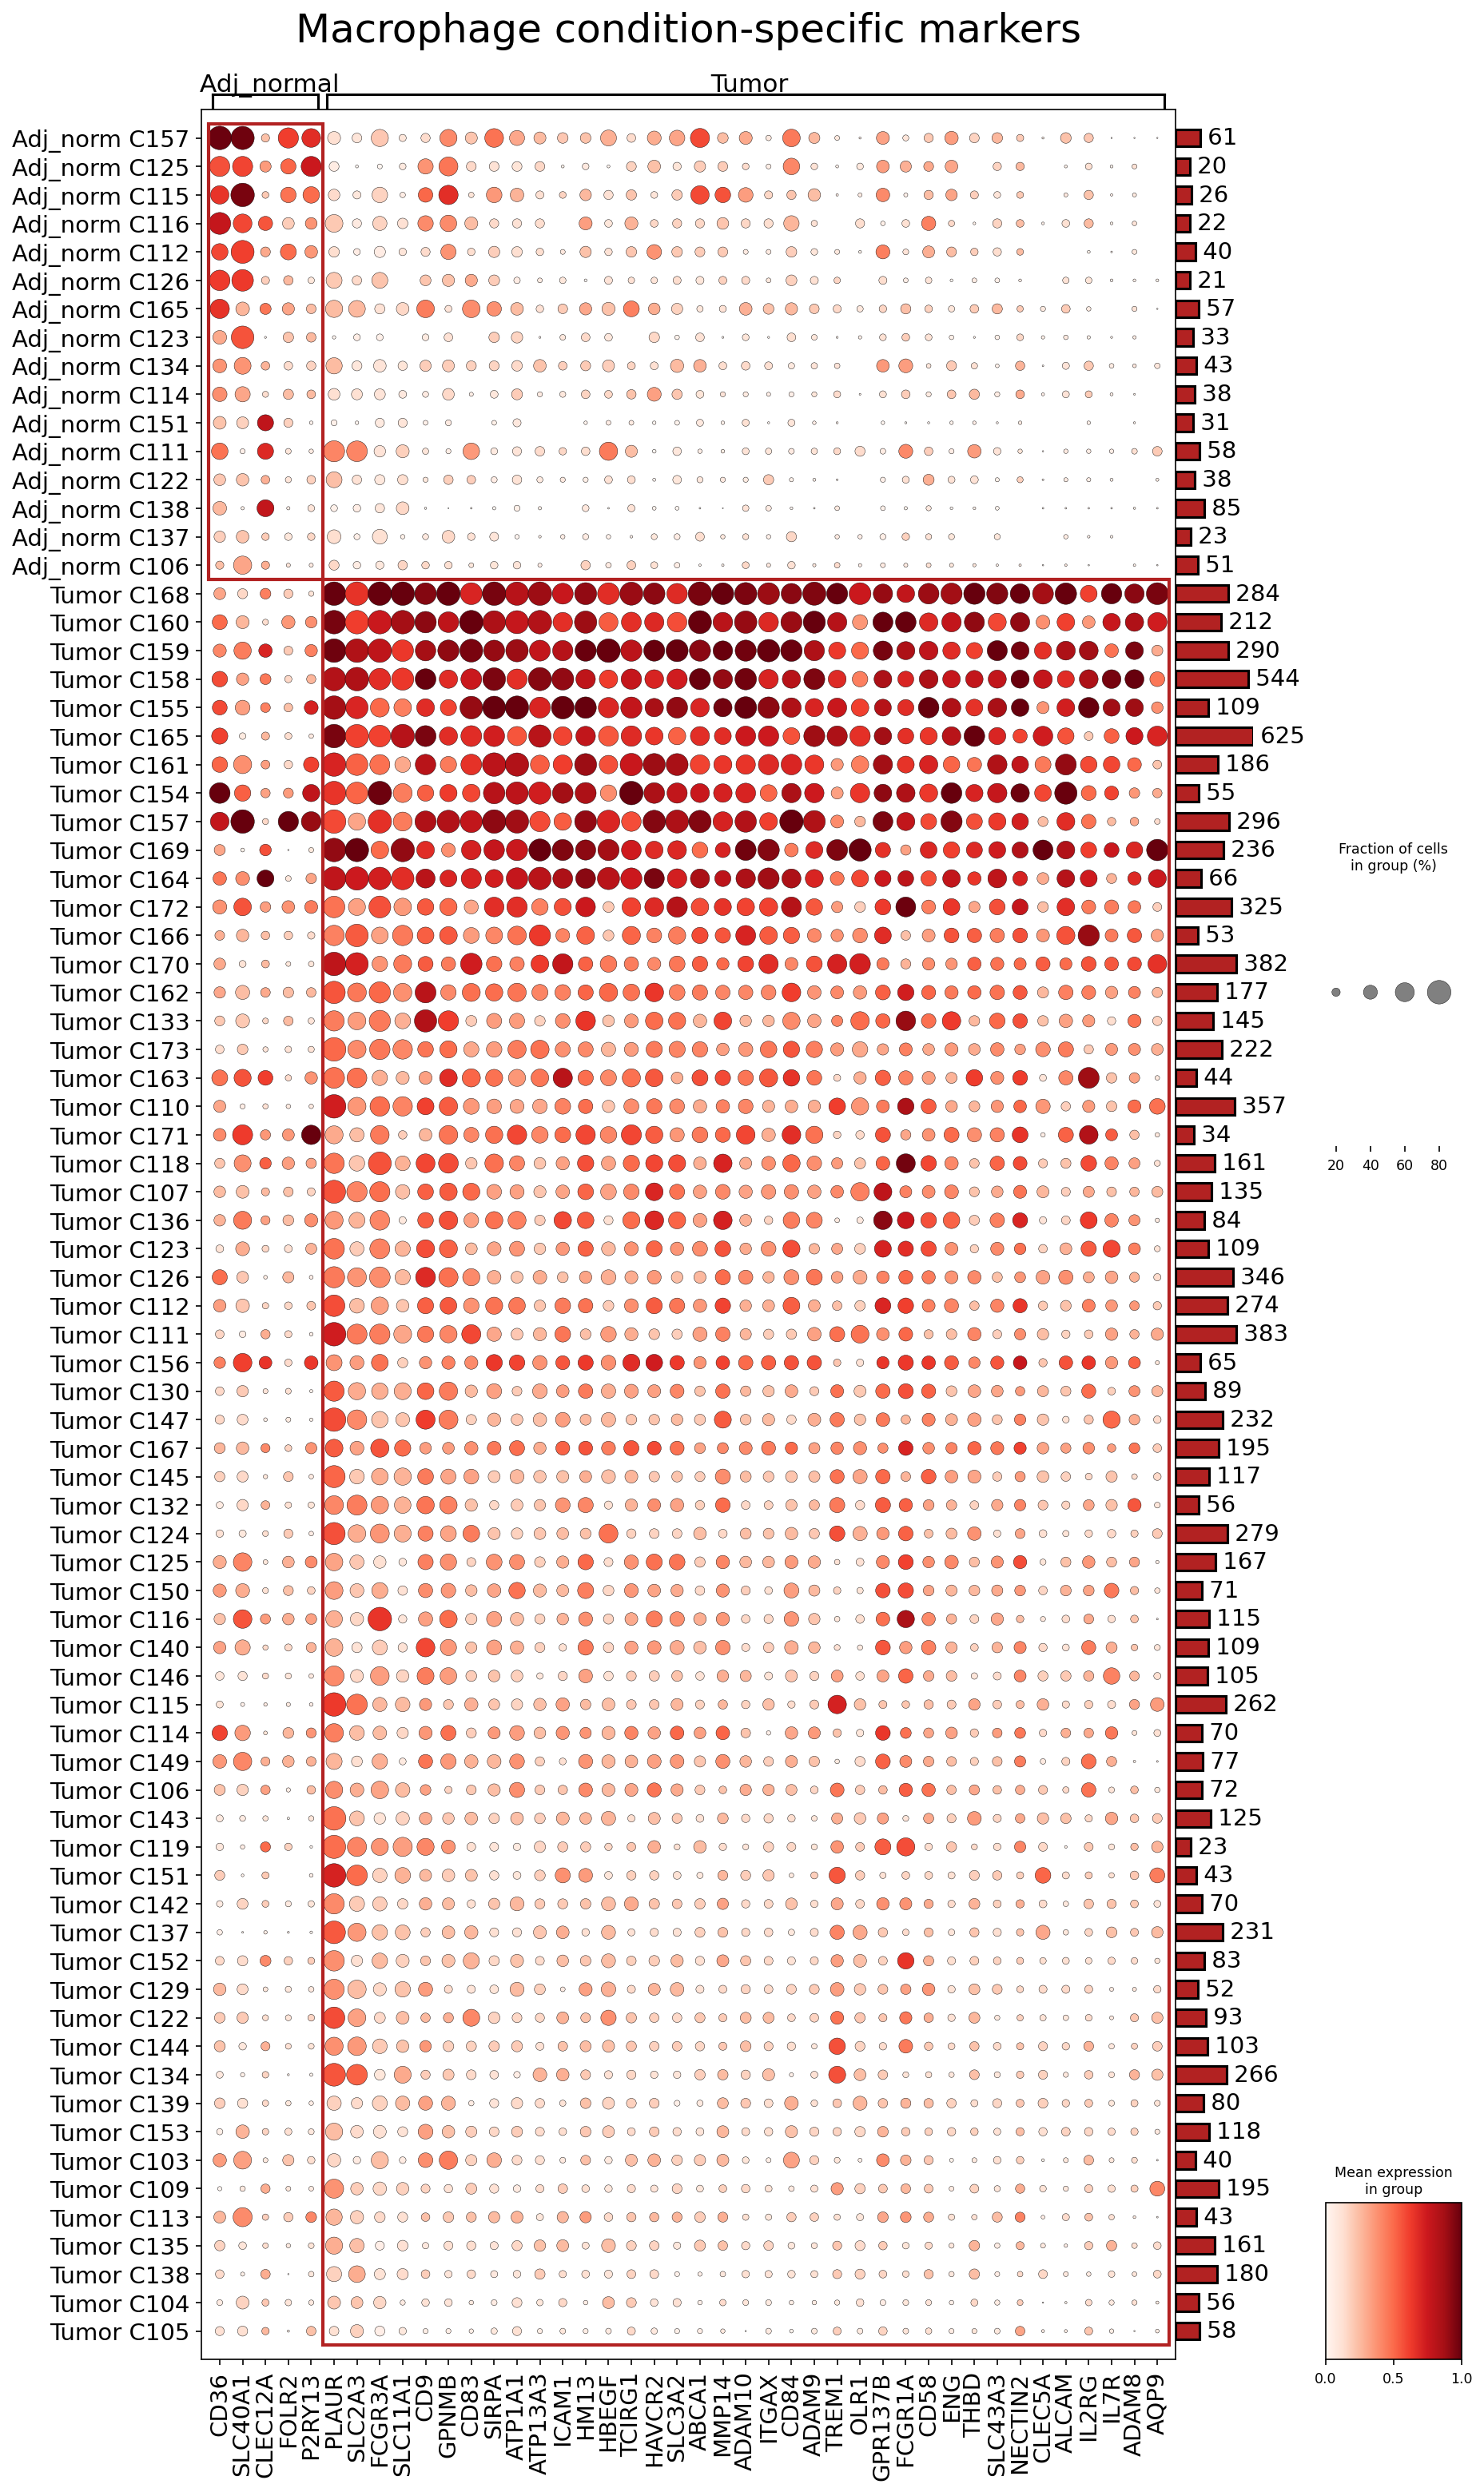
[Analysis Visualization Results]...
Analysis Overview
This analysis identifies surfaceome markers differentially expressed in Macrophages from Colorectal Cancer (CRC) tumor tissue compared to adjacent normal colon tissue. Utilizing single-cell RNA-seq data, a dot plot visualizes the mean expression and percentage of cells expressing specific surface markers across various patient samples within both 'Adj_normal' and 'Tumor' conditions. The objective is to highlight markers that distinguish tumor-associated macrophages (TAMs) from their counterparts in healthy tissue, offering insights into their functional states and potential as therapeutic targets in the tumor microenvironment (TME).
Visual Summary
The dot plot effectively illustrates distinct expression profiles of surfaceome markers in macrophages from adjacent normal versus tumor samples.
- Adjacent Normal Macrophages: A subset of markers shows prominent expression in macrophages from adjacent normal tissue samples (e.g., CD40, SLC40A1, CD83). These markers generally exhibit moderate to high mean expression and fraction of positive cells within the 'Adj_normal' group. However, the overall number of highly expressed, specific markers appears lower and less universally expressed across all adjacent normal samples compared to tumor.
- Tumor-Associated Macrophages (TAMs): A striking pattern emerges in the tumor samples, where a significantly larger and more diverse set of surface markers displays high mean expression and high cell detection frequency. Markers such as FOLR2, MMP14, MRC1, TREM2, CD36, SIRPA, and NRP1 show widespread and strong upregulation across a large number of tumor samples, indicating a distinct transcriptional and phenotypic shift in macrophages within the CRC TME. This suggests a consistent and potentially disease-promoting activation state for TAMs.
- Differential Expression: There is a clear demarcation between the marker profiles of adjacent normal and tumor macrophages. Markers highly expressed in tumor macrophages are often absent or expressed at very low levels in adjacent normal macrophages, and vice versa. This differential expression underscores the profound impact of the tumor microenvironment on macrophage phenotype.
- Heterogeneity: While there are clear trends, some heterogeneity is observed within both 'Adj_normal' and 'Tumor' groups, reflecting inter-patient variability and potentially distinct macrophage subsets within each condition.
Biological Interpretation
The distinct surfaceome profiles reveal a profound reprogramming of macrophages within the colorectal cancer microenvironment, indicating a shift from a homeostatic or generally immune-active state in normal tissue to a highly specialized, often pro-tumoral, phenotype in the tumor.
Markers Enriched in Tumor-Associated Macrophages (TAMs)
The strong upregulation of these surface markers in tumor macrophages points towards their altered functions, involvement in tumor progression, and potential as therapeutic targets.
FOLR2 (Folate Receptor Beta)
- Signaling Pathways: Folate uptake and metabolism, potentially related to macrophage activation and proliferation. FOLR2 internalizes folate, which is crucial for nucleotide synthesis and cell growth.
- Role in TME: FOLR2 is highly expressed on activated macrophages, particularly a subset of tumor-associated macrophages (TAMs). These TAMs often exhibit an M2-like, immunosuppressive, and pro-angiogenic phenotype in the CRC TME, promoting tumor growth and metastasis. GeneCards: FOLR2
- Therapeutic Potential: High expression on TAMs makes FOLR2 an attractive target for antibody-drug conjugates (ADCs) or radioimmunotherapy to specifically deplete pro-tumoral macrophages or deliver anti-cancer payloads.
- Therapeutic Agents: Folate-conjugated drugs or anti-FOLR2 antibodies are under investigation for targeted delivery.
MMP14 (Matrix Metallopeptidase 14)
- Signaling Pathways: Extracellular matrix (ECM) remodeling, integrin signaling, growth factor activation (e.g., pro-MMP2 activation), and angiogenesis.
- Role in TME: MMP14, a membrane-bound metalloproteinase, is crucial for degrading ECM components, facilitating cancer cell invasion, metastasis, and angiogenesis. In TAMs, its expression contributes to the proteolytic environment that supports tumor expansion and immune evasion. GeneCards: MMP14
- Therapeutic Potential: Inhibiting MMP14 on TAMs could reduce tumor invasion, metastasis, and angiogenesis.
- Therapeutic Agents: MMP inhibitors have been explored, though with limited success due to broad specificity. Targeting MMP14 specifically on TAMs might be more efficacious.
MRC1 (CD206, Mannose Receptor C-Type 1)
- Signaling Pathways: Pattern recognition, endocytosis, antigen processing. Often associated with anti-inflammatory and tissue repair pathways.
- Role in TME: MRC1 is a classic marker of M2-polarized macrophages, which are typically immunosuppressive and pro-tumoral in the CRC TME. These TAMs promote angiogenesis, tissue remodeling, and suppress anti-tumor immune responses. GeneCards: MRC1
- Therapeutic Potential: Targeting M2-like TAMs expressing MRC1 could reprogram the TME to be more anti-tumoral, enhancing the efficacy of immunotherapies.
- Therapeutic Agents: Strategies to deplete M2 TAMs or block MRC1-mediated functions are being investigated.
TREM2 (Triggering Receptor Expressed on Myeloid Cells 2)
- Signaling Pathways: DAP12-mediated signaling, lipid metabolism, phagocytosis, and regulation of inflammation.
- Role in TME: TREM2 is a key receptor found on various tissue-resident macrophages, including TAMs in CRC. In the TME, TREM2+ TAMs are often associated with an immunosuppressive phenotype, promoting tumor growth, lipid metabolism in TAMs, and supporting an unfavorable TME. GeneCards: TREM2
- Therapeutic Potential: Modulating TREM2 activity (e.g., blocking) on TAMs could re-sensitize tumors to immunotherapy and inhibit tumor progression.
- Therapeutic Agents: Anti-TREM2 antibodies are in preclinical development for various diseases, including cancer.
CD36
- Signaling Pathways: Fatty acid uptake and metabolism, lipid sensing, angiogenesis, and cell adhesion.
- Role in TME: CD36, a scavenger receptor, mediates the uptake of fatty acids, which can fuel TAM metabolism and promote an immunosuppressive, pro-tumoral phenotype. High CD36 expression on TAMs can contribute to tumor growth, metastasis, and resistance to therapy in CRC. GeneCards: CD36
- Therapeutic Potential: Inhibiting CD36 could starve TAMs of essential lipids, altering their pro-tumoral functions and metabolic state, thereby suppressing tumor growth.
- Therapeutic Agents: Small molecule inhibitors targeting CD36 or metabolic pathways in cancer cells are being explored.
SIRPA (Signal Regulatory Protein Alpha)
- Signaling Pathways: SIRPA-CD47 axis signaling, mediating "don't eat me" signals that inhibit phagocytosis by macrophages.
- Role in TME: SIRPA is expressed on macrophages and binds to CD47, which is often overexpressed on cancer cells, including CRC. This interaction prevents macrophages from engulfing tumor cells, thus promoting immune evasion. GeneCards: SIRPA
- Therapeutic Potential: Blocking the SIRPA-CD47 interaction can "unmask" cancer cells and allow macrophages to phagocytose them, representing a promising immunotherapeutic strategy.
- Therapeutic Agents: Anti-CD47 antibodies (targeting the cancer cell side) and anti-SIRPA antibodies (targeting the macrophage side) are in clinical trials.
NRP1 (Neuropilin 1)
- Signaling Pathways: Co-receptor for VEGF, semaphorins, and other ligands. Involved in angiogenesis, neuronal guidance, and immune regulation.
- Role in TME: NRP1 is expressed on TAMs and contributes to angiogenesis and immune suppression in the TME. Its interaction with various ligands can promote an immunosuppressive environment and support tumor vascularization in CRC. GeneCards: NRP1
- Therapeutic Potential: Targeting NRP1 on TAMs could inhibit tumor angiogenesis and reverse immune suppression.
- Therapeutic Agents: Anti-NRP1 antibodies and peptide inhibitors are being investigated.
Markers Enriched in Adjacent Normal Macrophages
These markers potentially reflect macrophages involved in immune surveillance, tissue homeostasis, or inflammatory responses distinct from the chronic, pro-tumoral inflammation seen in tumors.
CD40
- Signaling Pathways: TNF receptor superfamily, crucial for co-stimulation of T cells, B cell activation, and macrophage activation.
- Role in TME: CD40 is an important co-stimulatory molecule on antigen-presenting cells (APCs), including macrophages, for activating anti-tumor T cell responses. Its relatively higher expression in adjacent normal tissue macrophages suggests a potentially more immunologically competent or active state compared to the dominant TAM phenotype in tumors. GeneCards: CD40
- Therapeutic Potential: Agonistic anti-CD40 antibodies are used in cancer immunotherapy to activate APCs and induce potent anti-tumor T cell responses.
- Therapeutic Agents: Agonistic anti-CD40 antibodies (e.g., moga-CD40, selicrelumab) are in clinical development.
SLC40A1 (Ferroportin)
- Signaling Pathways: Iron export, crucial for systemic and cellular iron homeostasis. Regulated by hepcidin.
- Role in TME: Ferroportin is the only known iron exporter and plays a critical role in iron metabolism. Its expression in macrophages in adjacent normal tissue is consistent with their role in maintaining iron balance and preventing iron-driven oxidative stress, which can be altered in the tumor setting. GeneCards: SLC40A1
- Therapeutic Potential: While not a direct therapeutic target for cancer, understanding iron dysregulation in macrophages could inform strategies to modulate TME iron levels to impact tumor growth or sensitivity to ferroptosis-inducing therapies.
CD83
- Signaling Pathways: Lymphocyte activation and differentiation, T cell activation, and immune tolerance.
- Role in TME: CD83 is typically expressed on mature dendritic cells and activated B cells, but also found on some activated macrophage populations. Its presence in adjacent normal macrophages might indicate a more mature or activated state, contributing to local immune surveillance or homeostatic immune functions, contrasting with the often anergic or immunosuppressive state of TAMs. GeneCards: CD83
- Therapeutic Potential: Modulating CD83 pathways could influence immune cell activation and the balance between pro- and anti-tumor immunity.
Clinical or Translational Implications
The profound differences in surfaceome marker expression between macrophages in tumor versus adjacent normal tissue in colorectal cancer highlight several critical translational implications:
- Biomarker Discovery: The identified tumor-specific macrophage markers (e.g., FOLR2, MRC1, TREM2, CD36, SIRPA, NRP1) can serve as valuable biomarkers for:
- Diagnosis and Prognosis: Quantifying TAMs expressing these markers in biopsies could offer prognostic insights or aid in diagnosis.
- Patient Stratification: Identifying patients with specific TAM phenotypes could guide treatment decisions, particularly for immunotherapies.
- Therapeutic Targeting: The strong and prevalent expression of markers like FOLR2, MRC1, TREM2, CD36, SIRPA, and NRP1 on TAMs provides compelling rationale for developing targeted therapies.
- Direct Depletion/Inhibition: Strategies like antibody-drug conjugates (ADCs) or direct inhibitors could selectively deplete pro-tumoral TAMs or block their pro-cancer functions. For example, blocking the SIRPA-CD47 axis is an active area of investigation to "release the brakes" on macrophage phagocytosis of tumor cells.
- Immune Reprogramming: Therapies aimed at modulating the activity of these receptors (e.g., TREM2 modulators) could reprogram TAMs from an M2-like, immunosuppressive state to a more M1-like, anti-tumoral state, thus enhancing the efficacy of existing immunotherapies such as checkpoint inhibitors.
- Combination Therapies: Understanding the specific surface markers on TAMs allows for rational design of combination therapies. For instance, combining a targeted TAM therapy (e.g., anti-SIRPA) with a T-cell-centric immunotherapy (e.g., anti-PD-1) could synergistically enhance anti-tumor responses by simultaneously boosting effector T cells and removing immunosuppressive TAMs.
- Monitoring Treatment Response: Changes in the expression of these markers on circulating or tissue-resident macrophages could potentially serve as pharmacodynamic biomarkers to monitor the effectiveness of macrophage-targeting therapies.
Overall, the observed macrophage surfaceome profiles underscore the pivotal role of these immune cells in the colorectal cancer microenvironment and provide a rich reservoir of potential targets for developing next-generation cancer immunotherapies.
17. Fibroblast Condition-Specific Surfaceome Marker Expression in Colorectal Cancer
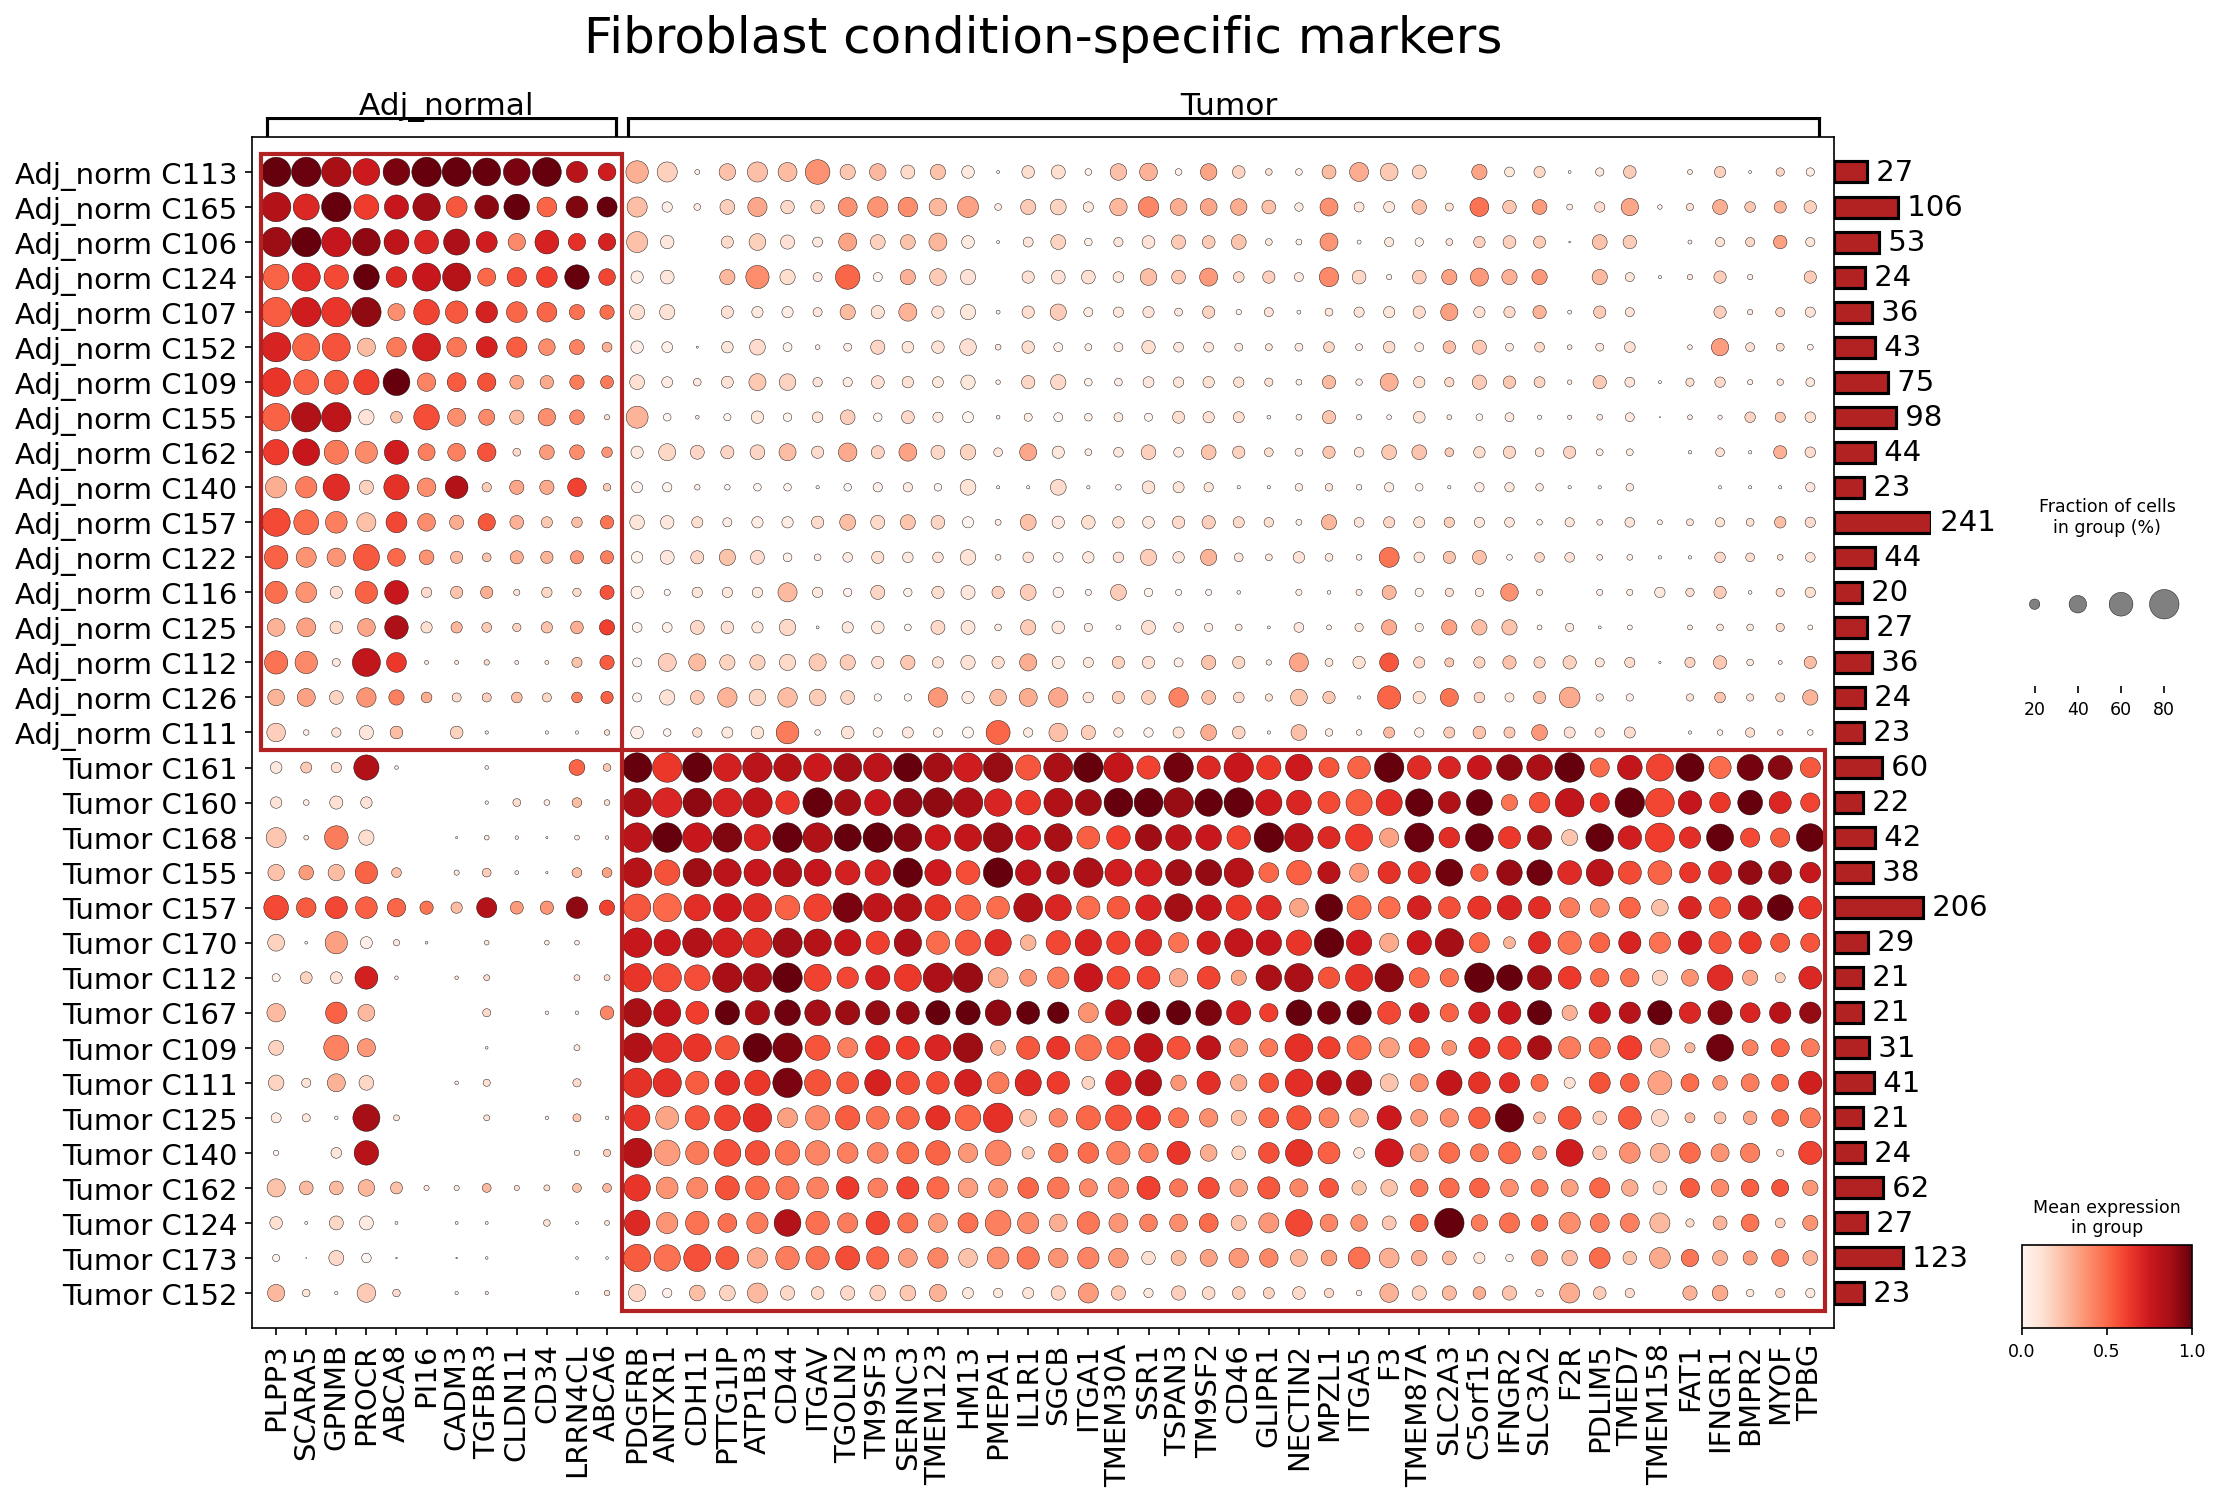
[Analysis Visualization Results]...
Analysis Overview
This analysis identifies surfaceome markers differentially expressed in fibroblasts from 'Adj_normal' (adjacent normal) and 'Tumor' tissues in colorectal cancer (CRC) patients. The dot plot visualizes the expression patterns of these markers across individual samples, showing both the mean expression level (color intensity) and the fraction of cells expressing the gene (dot size). The aim is to distinguish normal tissue-resident fibroblasts from cancer-associated fibroblasts (CAFs) based on their surface protein profiles, offering potential insights into their distinct roles in the tumor microenvironment and identifying candidate therapeutic targets.
Visual Summary
The dot plot clearly differentiates two main groups of fibroblast markers based on their expression patterns across conditions:
- Adjacent Normal Fibroblast Markers: A distinct set of genes, including PLPP3, SCARA5, GPMNB, ABCB8, CADM3, TGFBR3, LRRN4CL, PDGFRB, ANTXR1, PTTG1IP, ITGAL, and CD44, show high mean expression (dark red dots) and a high fraction of expressing cells (large dot size) predominantly in 'Adj_normal' samples. These markers are largely absent or expressed at very low levels in 'Tumor' samples, indicating a shift in fibroblast phenotype within the tumor microenvironment.
- Tumor Fibroblast Markers: Conversely, another set of genes, such as PMEPA1, IL1R1, SGCB, ITGA1, TMEM30A, SSR1, GLIPR1, NECTIN2, MPZL1, SLC2A3, and IFNGR2, exhibit strong expression specifically in 'Tumor' samples. These markers are either not expressed or expressed at negligible levels in 'Adj_normal' samples. This pattern highlights a unique surfaceome signature associated with cancer-associated fibroblasts (CAFs).
- Shared/Variable Markers: Some markers like ITGA5, F3, TMEM158, FAT1, IFNGR1, and BMPR2 show more variable expression or appear in both conditions, albeit often with different intensities or cell fractions, suggesting context-dependent roles or heterogeneity within fibroblast populations.
- Sample Heterogeneity: Within both 'Adj_normal' and 'Tumor' conditions, there is some variability in marker expression across individual patient samples (rows), indicating inter-patient heterogeneity in fibroblast populations and their associated molecular signatures. However, the overall condition-specific trends are robust.
Biological Interpretation
The differential surfaceome marker expression observed in fibroblasts from 'Adj_normal' versus 'Tumor' tissues underscores the profound phenotypical changes undergone by fibroblasts in the colorectal cancer microenvironment. Cancer-associated fibroblasts (CAFs) are a critical component of the tumor stroma, playing diverse roles in promoting tumor growth, invasion, metastasis, angiogenesis, and immune evasion. The identified surfaceome markers provide molecular handles to understand these processes.
Markers Enriched in Adjacent Normal Fibroblasts
- PDGFRB (Platelet-Derived Growth Factor Receptor Beta)
- Associated Signaling Pathways: PDGFRB is a receptor tyrosine kinase that binds PDGFs, activating downstream pathways such as PI3K/Akt, MAPK/ERK, and STAT. These pathways regulate cell proliferation, survival, migration, and differentiation.
- Role in TME: In normal tissues, PDGFRB signaling is crucial for fibroblast proliferation, migration, and extracellular matrix (ECM) remodeling, contributing to tissue homeostasis and repair. Its reduced expression in tumor fibroblasts might indicate a shift in their responsiveness to PDGF or that alternative growth signals dominate within the tumor.
- Therapeutic Potential: While PDGFRB is a known CAF marker in some cancers, its downregulation here suggests it might be more characteristic of quiescent or normal tissue-maintaining fibroblasts in this CRC context. Modulating PDGF signaling remains a therapeutic strategy in other contexts (e.g., GIST), but its role here suggests it may not be a *pro-tumorigenic* target on fibroblasts in CRC.
- Relevant Therapeutic Agents: Imatinib (Gleevec), Sunitinib (Sutent) are multi-kinase inhibitors targeting PDGFR, among others.
- Other Information: GeneCards: https://www.genecards.org/cgi-bin/carddisp.pl?gene=PDGFRB
- TGFBR3 (Transforming Growth Factor Beta Receptor 3 / Betaglycan)
- Associated Signaling Pathways: TGFBR3 is a co-receptor for TGF-beta, modulating its signaling by presenting TGF-beta ligands to the signaling receptors (TGFBR1/TGFBR2) or by sequestering them. It can either enhance or inhibit TGF-beta signaling depending on the cellular context and co-expression of other receptors.
- Role in TME: TGF-beta signaling is highly contextual in cancer, acting as a tumor suppressor in early stages and a tumor promoter later. Reduced TGFBR3 on tumor fibroblasts could alter their response to TGF-beta, potentially contributing to unchecked CAF activation and pro-tumorigenic functions.
- Therapeutic Potential: As a modulator of the critical TGF-beta pathway, alterations in TGFBR3 expression could influence therapeutic responses to TGF-beta inhibitors.
- Other Information: UniProt: https://www.uniprot.org/uniprotkb/P28374
- SCARA5 (Scavenger Receptor Class A Member 5)
- Associated Signaling Pathways: Scavenger receptors are involved in diverse functions including host defense, apoptotic cell clearance, and lipid metabolism. Specific signaling pathways for SCARA5 in fibroblasts are not extensively characterized but likely involve endocytosis and intracellular signaling related to ligand binding.
- Role in TME: SCARA5 has been implicated as a tumor suppressor in some cancers, potentially by inhibiting cell proliferation or promoting apoptosis. Its higher expression in normal fibroblasts might reflect a role in maintaining tissue integrity or a less activated state.
- Therapeutic Potential: If SCARA5 indeed has tumor-suppressive functions, strategies to upregulate its expression or mimic its activity could be explored.
- Other Information: PubMed search for "SCARA5 cancer": https://pubmed.ncbi.nlm.nih.gov/?term=SCARA5+cancer
Markers Enriched in Tumor Fibroblasts
- PMEPA1 (Prostate Transmembrane Protein Androgen Induced 1)
- Associated Signaling Pathways: PMEPA1 is a transmembrane protein that acts as an intracellular regulator of TGF-beta signaling. It can degrade TGF-beta receptors, thereby attenuating TGF-beta signaling, or it can be involved in other cellular processes.
- Role in TME: Upregulation of PMEPA1 in CAFs could contribute to altered TGF-beta responsiveness, potentially favoring certain pro-tumorigenic aspects of CAF activation or immune evasion. Dysregulation of TGF-beta signaling is central to CAF function.
- Therapeutic Potential: Modulating PMEPA1 could indirectly influence TGF-beta signaling, offering a novel approach to target CAF activation.
- Other Information: GeneCards: https://www.genecards.org/cgi-bin/carddisp.pl?gene=PMEPA1
- IL1R1 (Interleukin 1 Receptor Type 1)
- Associated Signaling Pathways: IL1R1 is the primary receptor for the pro-inflammatory cytokine IL-1β. Its activation triggers downstream signaling cascades including NF-κB and MAPK pathways, leading to the expression of inflammatory genes, growth factors, and chemokines.
- Role in TME: IL-1β is a key cytokine in the inflammatory tumor microenvironment. CAFs expressing high levels of IL1R1 are likely highly responsive to IL-1β, contributing to chronic inflammation, angiogenesis, and immune suppression, thereby promoting tumor progression.
- Therapeutic Potential: Targeting IL1R1 or its ligand IL-1β with antibodies or small molecule inhibitors could dampen pro-inflammatory signaling in the TME, thereby inhibiting CAF activation and tumor growth.
- Relevant Therapeutic Agents: Anakinra (IL-1R antagonist), Canakinumab (anti-IL-1β antibody).
- Other Information: UniProt: https://www.uniprot.org/uniprotkb/P14778
- ITGA1 (Integrin Subunit Alpha 1)
- Associated Signaling Pathways: ITGA1 combines with ITGB1 to form the VLA-1 integrin, which primarily binds to collagen and laminin in the ECM. Integrin signaling is bidirectional, connecting the ECM to the cytoskeleton and activating various intracellular pathways (e.g., FAK, Src, MAPK, PI3K/Akt) that regulate cell adhesion, migration, proliferation, and survival.
- Role in TME: CAFs extensively remodel the ECM, and integrins like VLA-1 are critical for these interactions. Upregulation of ITGA1 suggests enhanced adhesion to specific ECM components, potentially facilitating CAF migration, invasion, and mechanical coupling within the stiff tumor stroma, contributing to tumor progression.
- Therapeutic Potential: Inhibiting specific integrins involved in CAF-ECM interactions could disrupt CAF functions and reduce desmoplasia. Antibodies targeting ITGA1 or its associated integrin complex could be explored.
- Other Information: GeneCards: https://www.genecards.org/cgi-bin/carddisp.pl?gene=ITGA1
- NECTIN2 (Nectin Cell Adhesion Molecule 2)
- Associated Signaling Pathways: Nectin2 is a cell adhesion molecule involved in homotypic and heterotypic cell-cell adhesion. It can interact with other nectins and form complexes with cadherins. Nectin signaling influences cell proliferation, migration, and immune cell interactions.
- Role in TME: Nectin2 is often upregulated in various cancers and can promote tumor cell growth and metastasis. Its expression on CAFs suggests a role in mediating CAF-tumor cell interactions or CAF-immune cell interactions within the TME, potentially contributing to immune evasion or tumor cell survival.
- Therapeutic Potential: Targeting Nectin2 on CAFs could disrupt cell-cell communication crucial for tumor growth and potentially enhance immune cell infiltration or activity.
- Other Information: PubMed search for "Nectin2 cancer": https://pubmed.ncbi.nlm.nih.gov/?term=NECTIN2+cancer
- SLC2A3 (Solute Carrier Family 2 Member 3 / GLUT3)
- Associated Signaling Pathways: SLC2A3 is a glucose transporter responsible for facilitating glucose uptake into cells. While not a signaling molecule itself, its activity is critical for cellular metabolism and impacts metabolic signaling pathways.
- Role in TME: CAFs are metabolically reprogrammed and can undergo aerobic glycolysis (Warburg effect) or provide metabolic support to tumor cells. Upregulation of GLUT3 indicates increased glucose demand by CAFs, fueling their energetic needs for proliferation, ECM production, and secretome activity, thus supporting tumor growth.
- Therapeutic Potential: Inhibiting glucose uptake through GLUT3 in CAFs could selectively starve them, disrupting their pro-tumorigenic functions and sensitizing tumor cells to therapy.
- Relevant Therapeutic Agents: Small molecule inhibitors targeting glucose transporters are under investigation in cancer therapy.
- Other Information: GeneCards: https://www.genecards.org/cgi-bin/carddisp.pl?gene=SLC2A3
- IFNGR2 (Interferon Gamma Receptor 2)
- Associated Signaling Pathways: IFNGR2 is a component of the heterodimeric receptor for Interferon-gamma (IFN-γ), alongside IFNGR1. Upon IFN-γ binding, the receptor complex activates the JAK-STAT signaling pathway, leading to the transcription of IFN-γ inducible genes involved in immune responses, cell growth inhibition, and apoptosis.
- Role in TME: CAFs can modulate immune responses. While IFN-γ typically has anti-tumor effects, prolonged exposure in the TME can lead to immune evasion mechanisms. Upregulation of IFNGR2 on CAFs suggests they are highly responsive to IFN-γ, which could influence their immunomodulatory functions, potentially leading to increased expression of immune checkpoint ligands or other immune suppressive factors.
- Therapeutic Potential: Targeting IFNGR2, or pathways downstream of IFN-γ signaling in CAFs, could be considered in combination with immunotherapies to counteract potential immune suppressive effects or to re-sensitize CAFs to anti-tumor immunity.
- Other Information: UniProt: https://www.uniprot.org/uniprotkb/P38484
Clinical or Translational Implications
The identification of distinct surfaceome marker profiles for fibroblasts in adjacent normal tissue versus tumor tissue has significant clinical and translational implications for colorectal cancer:
- Diagnostic and Prognostic Biomarkers: The differentially expressed surfaceome markers, particularly those highly specific to tumor fibroblasts (e.g., PMEPA1, IL1R1, ITGA1, NECTIN2, SLC2A3, IFNGR2), could serve as diagnostic or prognostic biomarkers for CRC. Their presence and expression levels could be evaluated in patient biopsies to assess disease presence, progression, or therapeutic responsiveness.
- Therapeutic Targets for CAF Depletion/Reprogramming: As surface proteins, these tumor-specific markers are highly accessible for therapeutic intervention.
- Antibody-Drug Conjugates (ADCs): Antibodies targeting CAF-specific surface markers (e.g., IL1R1, ITGA1, NECTIN2) could deliver cytotoxic payloads directly to CAFs, leading to their selective depletion or functional inhibition without harming normal fibroblasts.
- CAR-T Cell Therapy: Engineering CAR-T cells to target CAF-specific surface markers could allow for direct killing or reprogramming of CAFs, thus remodeling the tumor microenvironment to be less pro-tumorigenic.
- Small Molecule Inhibitors: Inhibitors against key CAF-associated pathways or metabolic transporters (e.g., SLC2A3 for glucose uptake, or modulators of IL1R1/TGF-beta signaling) could attenuate CAF functions.
- Combination Therapies: Targeting CAFs through these surface markers could be particularly effective in combination with standard chemotherapies or immunotherapies. By reducing the immune-suppressive and pro-tumorigenic functions of CAFs, these markers offer a strategy to enhance the efficacy of existing treatments and overcome resistance mechanisms. For example, inhibiting IL1R1 signaling in CAFs could reduce inflammation and improve immune checkpoint blockade response.
- Understanding CAF Heterogeneity: The variability in marker expression across tumor samples suggests heterogeneity within CAFs themselves, which could impact treatment response. Further sub-clustering of CAFs based on these markers might lead to personalized treatment approaches.
18. T cell CD4+ Condition-Specific Surfaceome Marker Expression in Colorectal Cancer
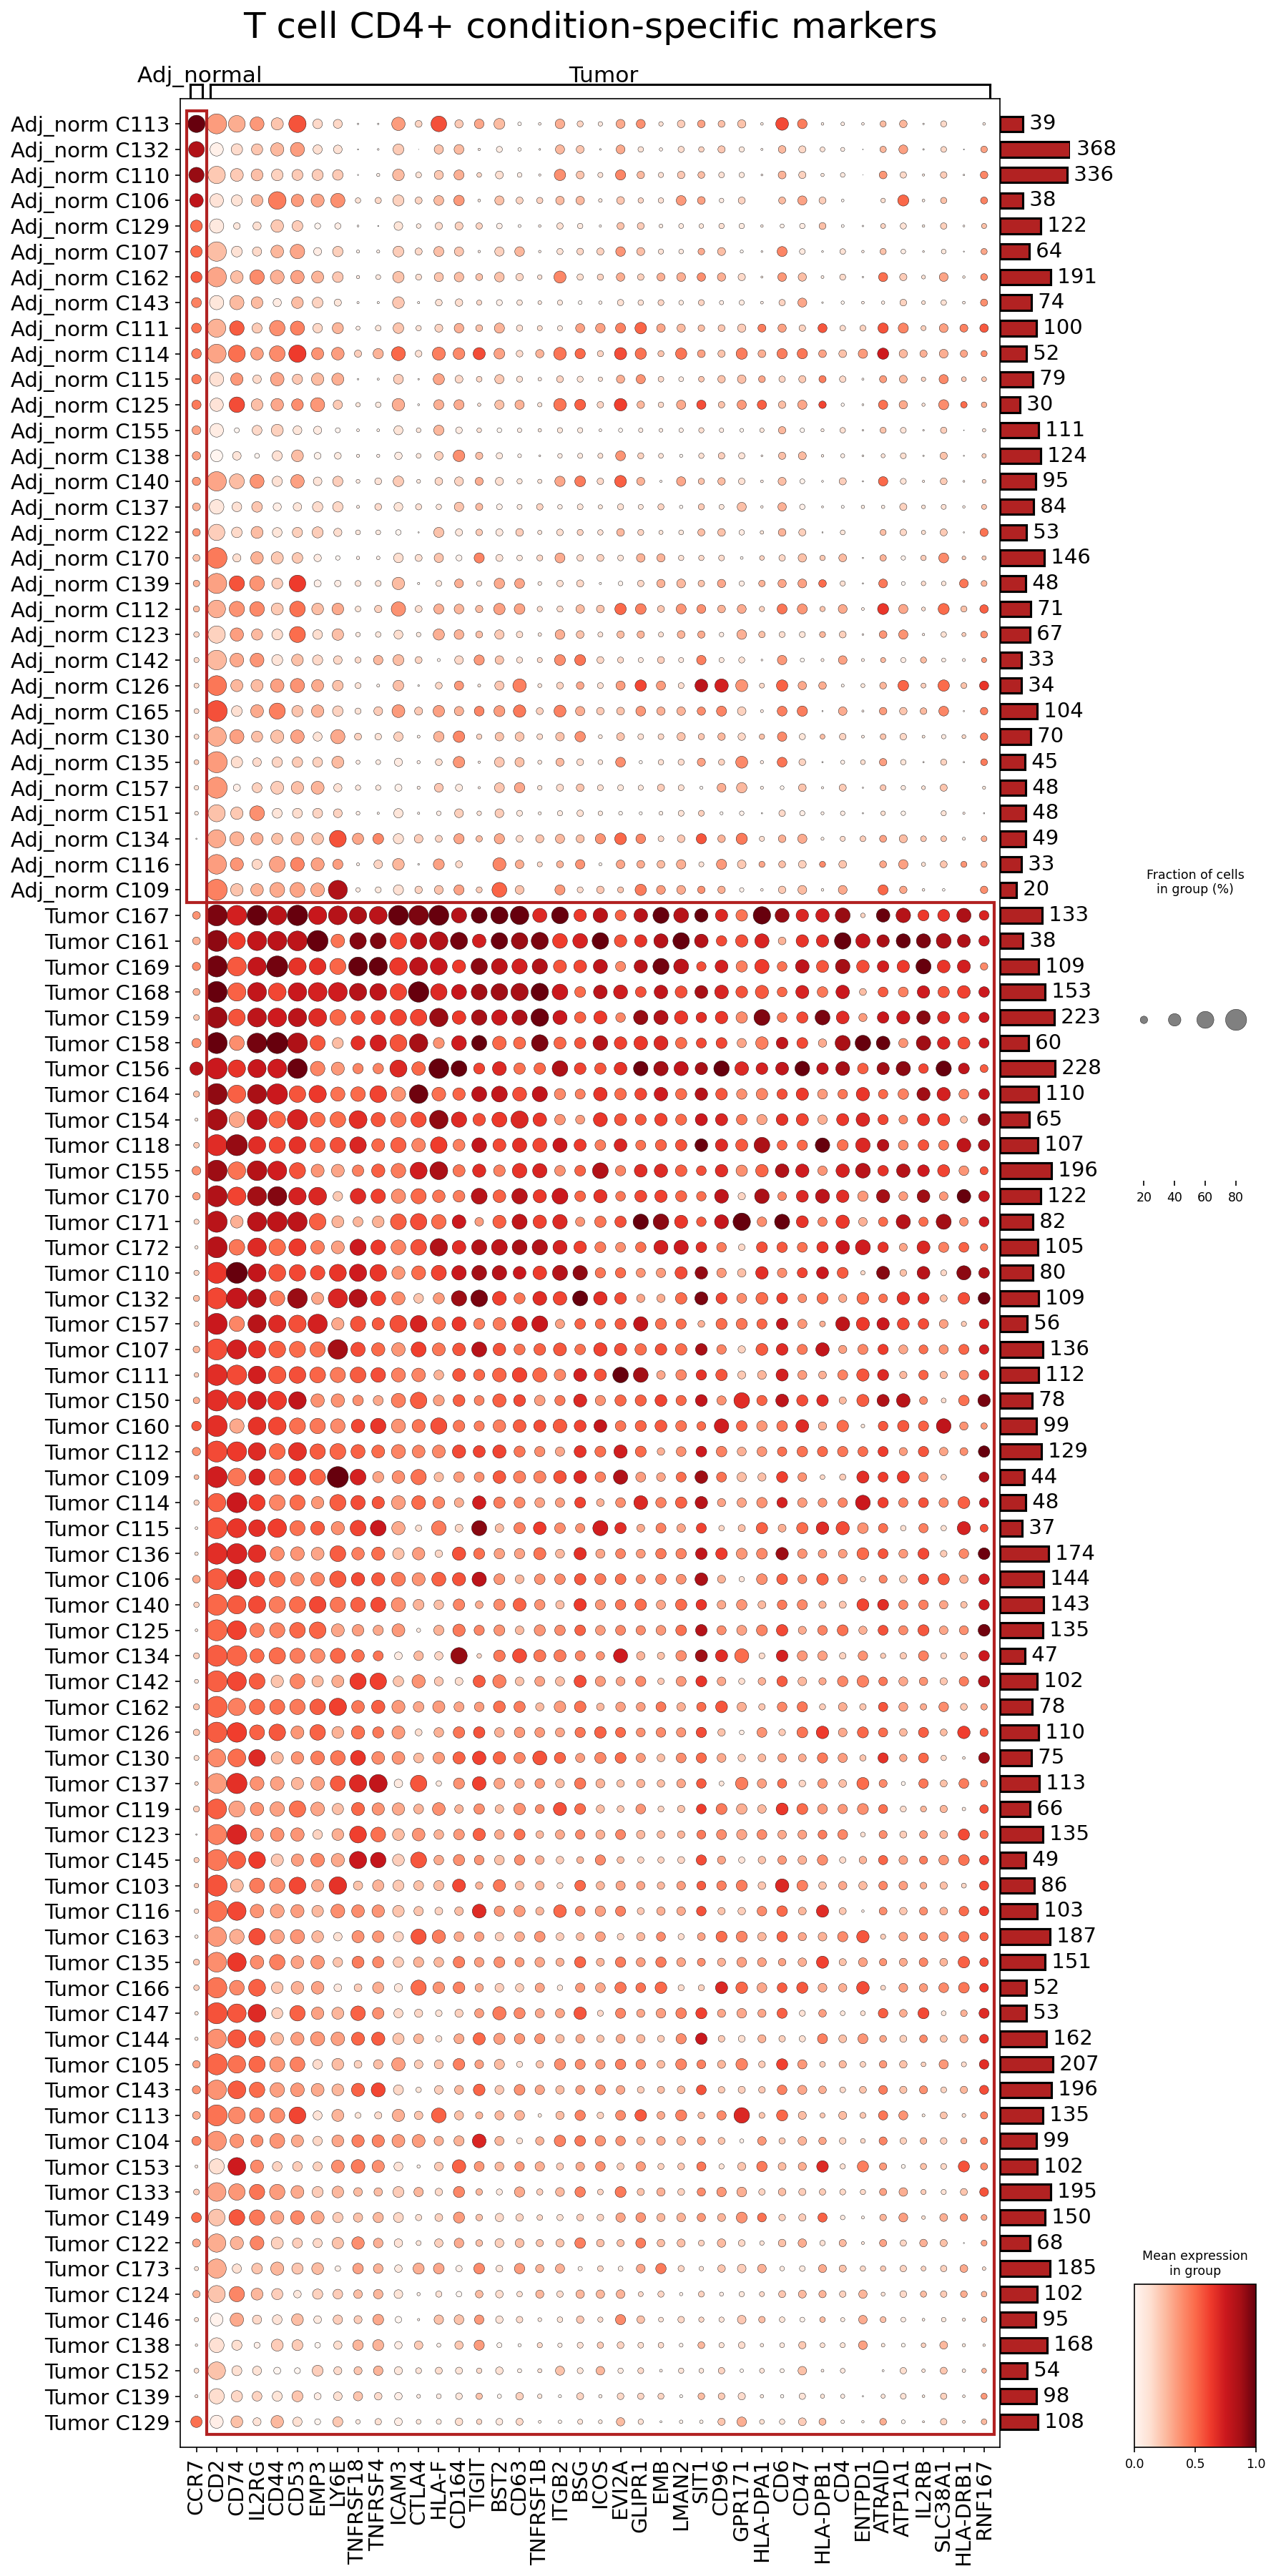
[Analysis Visualization Results]...
Analysis Overview
This analysis investigates the expression patterns of surfaceome markers in CD4+ T cells derived from both colorectal tumor and adjacent normal tissues. The primary objective is to identify markers that are differentially expressed between these two conditions, offering insights into the phenotypic state and potential therapeutic vulnerabilities of CD4+ T cells within the colorectal cancer (CRC) microenvironment. The provided dot plot visualizes the fraction of cells expressing each marker (dot size) and the mean expression level (color intensity) across individual patient samples, highlighting condition-specific trends.
Visual Summary
The dot plot clearly illustrates a distinct shift in the surfaceome profile of CD4+ T cells when comparing adjacent normal and tumor conditions.
- Constitutive T cell markers (CD3D, CD4): As expected, these foundational markers for CD4+ T cells are highly and broadly expressed across almost all samples in both Adj_normal and Tumor conditions, confirming the cellular identity.
Markers predominantly expressed in Adjacent Normal Tissues:
- CCR7 shows consistently higher mean expression and a larger fraction of expressing cells in many Adj_normal samples. This pattern suggests a prevalence of naive or central memory CD4+ T cells in the healthy tissue environment.
- IL2RG and CD53 also maintain robust expression across most Adj_normal samples.
- Markers significantly upregulated in Tumor Tissues: A pronounced group of markers demonstrates notably higher expression levels and/or a greater proportion of positive cells within Tumor samples. These include:
- Immune Checkpoints/Co-stimulatory Receptors: CTLA4, TIGIT, TNFRSF18 (GITR), TNFRSF4 (OX40), ICOS, CD96. The consistent upregulation of these molecules in the tumor microenvironment (TME) indicates a state of T cell activation, potential exhaustion, and ongoing immune modulation.
- MHC Class II molecules: HLA-DPA1, HLA-DPB1, HLA-DRB1 display increased expression in tumor-infiltrating CD4+ T cells, suggesting heightened activation or antigen presentation capabilities within the TME.
- Other Immunomodulatory Markers: ENTPD1 (CD39), BSG (CD147), CD63 are also elevated in the tumor context, pointing to their involvement in metabolic regulation or cell surface interactions critical for immune function.
In summary, the visualization points towards a significant phenotypic adaptation of CD4+ T cells within the CRC TME, characterized by a reduction in naive/central memory markers and a marked increase in both co-stimulatory and co-inhibitory receptors.
Biological Interpretation
The observed differential expression of surfaceome markers in CD4+ T cells provides crucial insights into their functional roles and regulatory mechanisms within the colorectal cancer TME.
Markers Upregulated in Tumor CD4+ T cells
- CTLA4 (Cytotoxic T-Lymphocyte-Associated Protein 4)
- Signaling Pathways: CTLA4 is an inhibitory receptor expressed on T cells that competes with CD28 for binding to CD80/CD86 on antigen-presenting cells (APCs). Its signaling curtails T cell activation and proliferation, acting as a crucial negative regulator of immune responses.
- Role in TME: The increased expression of CTLA4 on tumor-infiltrating CD4+ T cells, particularly regulatory T cells (Tregs) and activated effector T cells, contributes to immune tolerance and suppresses effective anti-tumor immunity in the colorectal cancer TME.
- Therapeutic Target Potential: CTLA4 is a well-established immune checkpoint target. Blocking CTLA4 can enhance anti-tumor immune responses by promoting T cell activation and attenuating Treg-mediated suppression.
- Relevant Therapeutic Agents: Ipilimumab, an anti-CTLA4 monoclonal antibody, is approved for various cancers and is often used in combination with anti-PD-1 therapy to maximize therapeutic benefit PubMed search: Ipilimumab colorectal cancer.
- TIGIT (T cell immunoreceptor with Ig and ITIM domains)
- Signaling Pathways: TIGIT is an inhibitory receptor found on T cells and NK cells. It binds to poliovirus receptor (PVR; CD155) and nectin-2 (CD112) on APCs and tumor cells, competing with the co-stimulatory receptor CD226 (DNAM-1). TIGIT engagement leads to suppressed T cell proliferation and cytokine production.
- Role in TME: Elevated TIGIT expression on tumor-infiltrating CD4+ T cells contributes to T cell exhaustion and immunosuppression within the colorectal cancer TME, hindering robust anti-tumor responses.
- Therapeutic Target Potential: TIGIT is an emerging immune checkpoint target. Blocking TIGIT can potentially reverse T cell exhaustion and enhance the efficacy of other immune checkpoint inhibitors.
- Relevant Therapeutic Agents: Anti-TIGIT monoclonal antibodies, such as Tiragolumab and Vibostolimab, are currently in clinical trials for various solid tumors, including CRC, often in combination with anti-PD-1 agents PubMed search: TIGIT blockade colorectal cancer.
- TNFRSF18 (Tumor Necrosis Factor Receptor Superfamily Member 18, also known as GITR)
- Signaling Pathways: GITR is a co-stimulatory receptor expressed on activated T cells, including effector and regulatory T cells. Its binding to GITRL (GITR Ligand) delivers a co-stimulatory signal that enhances effector T cell function and can attenuate Treg-mediated suppression.
- Role in TME: The upregulation of GITR on tumor-infiltrating CD4+ T cells indicates T cell activation within the TME. Its precise role is context-dependent, as its activation can both bolster anti-tumor immunity by inhibiting Tregs and potentially influence effector T cell responses.
- Therapeutic Target Potential: Agonistic anti-GITR antibodies are being explored as a strategy to boost anti-tumor immunity by stimulating effector T cells and inhibiting Tregs.
- Relevant Therapeutic Agents: Several agonistic anti-GITR antibodies (e.g., TRX518, MEDI1873) are under clinical development for various cancers PubMed search: GITR agonist cancer therapy.
- ICOS (Inducible T cell Co-stimulator)
- Signaling Pathways: ICOS is a co-stimulatory receptor on activated T cells, critical for the development and function of T follicular helper (Tfh) cells and certain regulatory T cells (Tregs). It binds to ICOSL on APCs, promoting T cell proliferation, survival, and cytokine production (e.g., IL-10, IL-21).
- Role in TME: Elevated ICOS on tumor-infiltrating CD4+ T cells can support B cell responses and tertiary lymphoid structures. However, its expression on Tregs can enhance their suppressive function, potentially contributing to immune evasion in colorectal cancer.
- Therapeutic Target Potential: Both agonistic and antagonistic anti-ICOS antibodies are under investigation. Agonists aim to enhance anti-tumor effector T cells, while antagonists might target ICOS+ Tregs to reduce immune suppression.
- Relevant Therapeutic Agents: Anti-ICOS agonists (e.g., Vopalimab) and antagonists are in various phases of clinical trials for different malignancies PubMed search: ICOS antibody cancer therapy.
- HLA-DRB1 (Human Leukocyte Antigen - DRB1)
- Signaling Pathways: HLA-DRB1 is an MHC class II molecule, typically expressed on professional APCs. Its presence on activated CD4+ T cells suggests a highly activated state, and these T cells may acquire the ability to present antigens, influencing other T cells.
- Role in TME: The increased expression of HLA-DRB1 on tumor-infiltrating CD4+ T cells indicates chronic antigen exposure and T cell activation within the colorectal cancer TME, possibly reflecting an exhausted or terminally differentiated state.
- Therapeutic Target Potential: While HLA-DRB1 itself is not a direct therapeutic target for modulating anti-tumor immunity, its expression is a valuable biomarker for T cell activation status and can correlate with responsiveness to immunotherapy.
- Relevant Therapeutic Agents: Not a direct drug target, but its expression is important for assessing immune activity and potential for antigen presentation GeneCards: HLA-DRB1.
- ENTPD1 (Ectonucleoside Triphosphate Diphosphohydrolase 1, also known as CD39)
- Signaling Pathways: CD39 is an ectoenzyme that hydrolyzes ATP and ADP to AMP. AMP is then further converted to adenosine by CD73. Adenosine is a potent immunosuppressive molecule in the TME, acting through adenosine receptors to inhibit effector T cell function.
- Role in TME: High expression of CD39 on tumor-infiltrating CD4+ T cells, particularly Tregs and exhausted T cells, contributes to an immunosuppressive, adenosine-rich environment in the colorectal cancer TME, thus hindering anti-tumor responses.
- Therapeutic Target Potential: Inhibiting CD39, or the broader adenosinergic pathway, is a promising strategy to counteract immune suppression in the TME and enhance anti-tumor immunity.
- Relevant Therapeutic Agents: CD39 inhibitors (e.g., A0740, POM-1) and CD73 inhibitors are currently under investigation to improve the efficacy of various cancer immunotherapies PubMed search: CD39 inhibitor cancer.
Markers Downregulated in Tumor CD4+ T cells (Upregulated in Adjacent Normal)
- CCR7 (C-C Chemokine Receptor Type 7)
- Signaling Pathways: CCR7 is a chemokine receptor that binds CCL19 and CCL21, orchestrating T cell homing to secondary lymphoid organs (SLOs) and promoting their recirculation. It is a key marker for naive and central memory T cells.
- Role in TME: The decreased expression of CCR7 on CD4+ T cells within the colorectal tumor suggests a phenotypic shift away from naive or central memory states towards more differentiated, effector, or exhausted phenotypes typically found in chronic inflammatory or tumor environments. This indicates impaired egress from the tumor or homing to SLOs.
- Therapeutic Target Potential: While not a direct therapeutic target for enhancing anti-tumor immunity in this context, CCR7 expression serves as an important biomarker for T cell differentiation, trafficking, and overall T cell repertoire diversity. Modulating CCR7 expression or function is relevant in adoptive cell therapies for improved cell trafficking.
- Relevant Therapeutic Agents: No direct therapeutic agents targeting CCR7 for cancer treatment; however, it is a crucial marker for understanding T cell migration and homing GeneCards: CCR7.
Clinical or Translational Implications
The distinct surfaceome profiles of CD4+ T cells in colorectal tumor versus adjacent normal tissues present compelling clinical and translational opportunities:
- Biomarker Identification: The differentially expressed markers, especially CTLA4, TIGIT, TNFRSF18 (GITR), ICOS, HLA-DRB1, and ENTPD1 (CD39), are valuable biomarkers for characterizing the immune landscape of colorectal cancer. Their expression patterns could potentially be used to stratify patients for immunotherapy, predict treatment response, or indicate prognosis.
- Targeted Immunotherapy Strategies: The prominent upregulation of immune checkpoints like CTLA4 and TIGIT highlights their critical role in mediating immune evasion in CRC. Targeting these pathways with specific monoclonal antibodies, either alone or in combination with other immunotherapies (e.g., anti-PD-1), offers a promising strategy to reactivate anti-tumor immunity.
- Co-stimulatory Receptor Agonism: The elevated expression of co-stimulatory receptors such as GITR (TNFRSF18) and ICOS suggests that agonistic antibodies against these molecules could be leveraged to enhance anti-tumor T cell responses, either as monotherapy or in combination regimens.
- Metabolic Reprogramming of the TME: The increased expression of ENTPD1 (CD39) underscores the importance of the adenosinergic pathway in creating an immunosuppressive TME. Inhibiting CD39 or other components of this pathway could neutralize adenosine-mediated suppression and amplify the efficacy of existing immunotherapies.
- Personalized Medicine for CRC: These findings are pivotal for developing patient-tailored immunotherapeutic approaches for colorectal cancer, taking into account the heterogeneity of immune responses observed in different CRC subtypes (e.g., microsatellite instability-high vs. microsatellite stable).
- Adoptive Cell Therapy Enhancement: Understanding the surfaceome of tumor-infiltrating CD4+ T cells can guide the engineering of adoptive T cell therapies, enabling the selection or modification of T cells with optimized homing, persistence, and effector functions for improved therapeutic outcomes.
The identified markers provide a rich foundation for further functional validation studies, drug development, and patient stratification efforts in the realm of colorectal cancer immunotherapy.
19. Analysis of Cell Cycle Pathway Gene Expression in Colorectal Cancer Intestinal Epithelial Cells
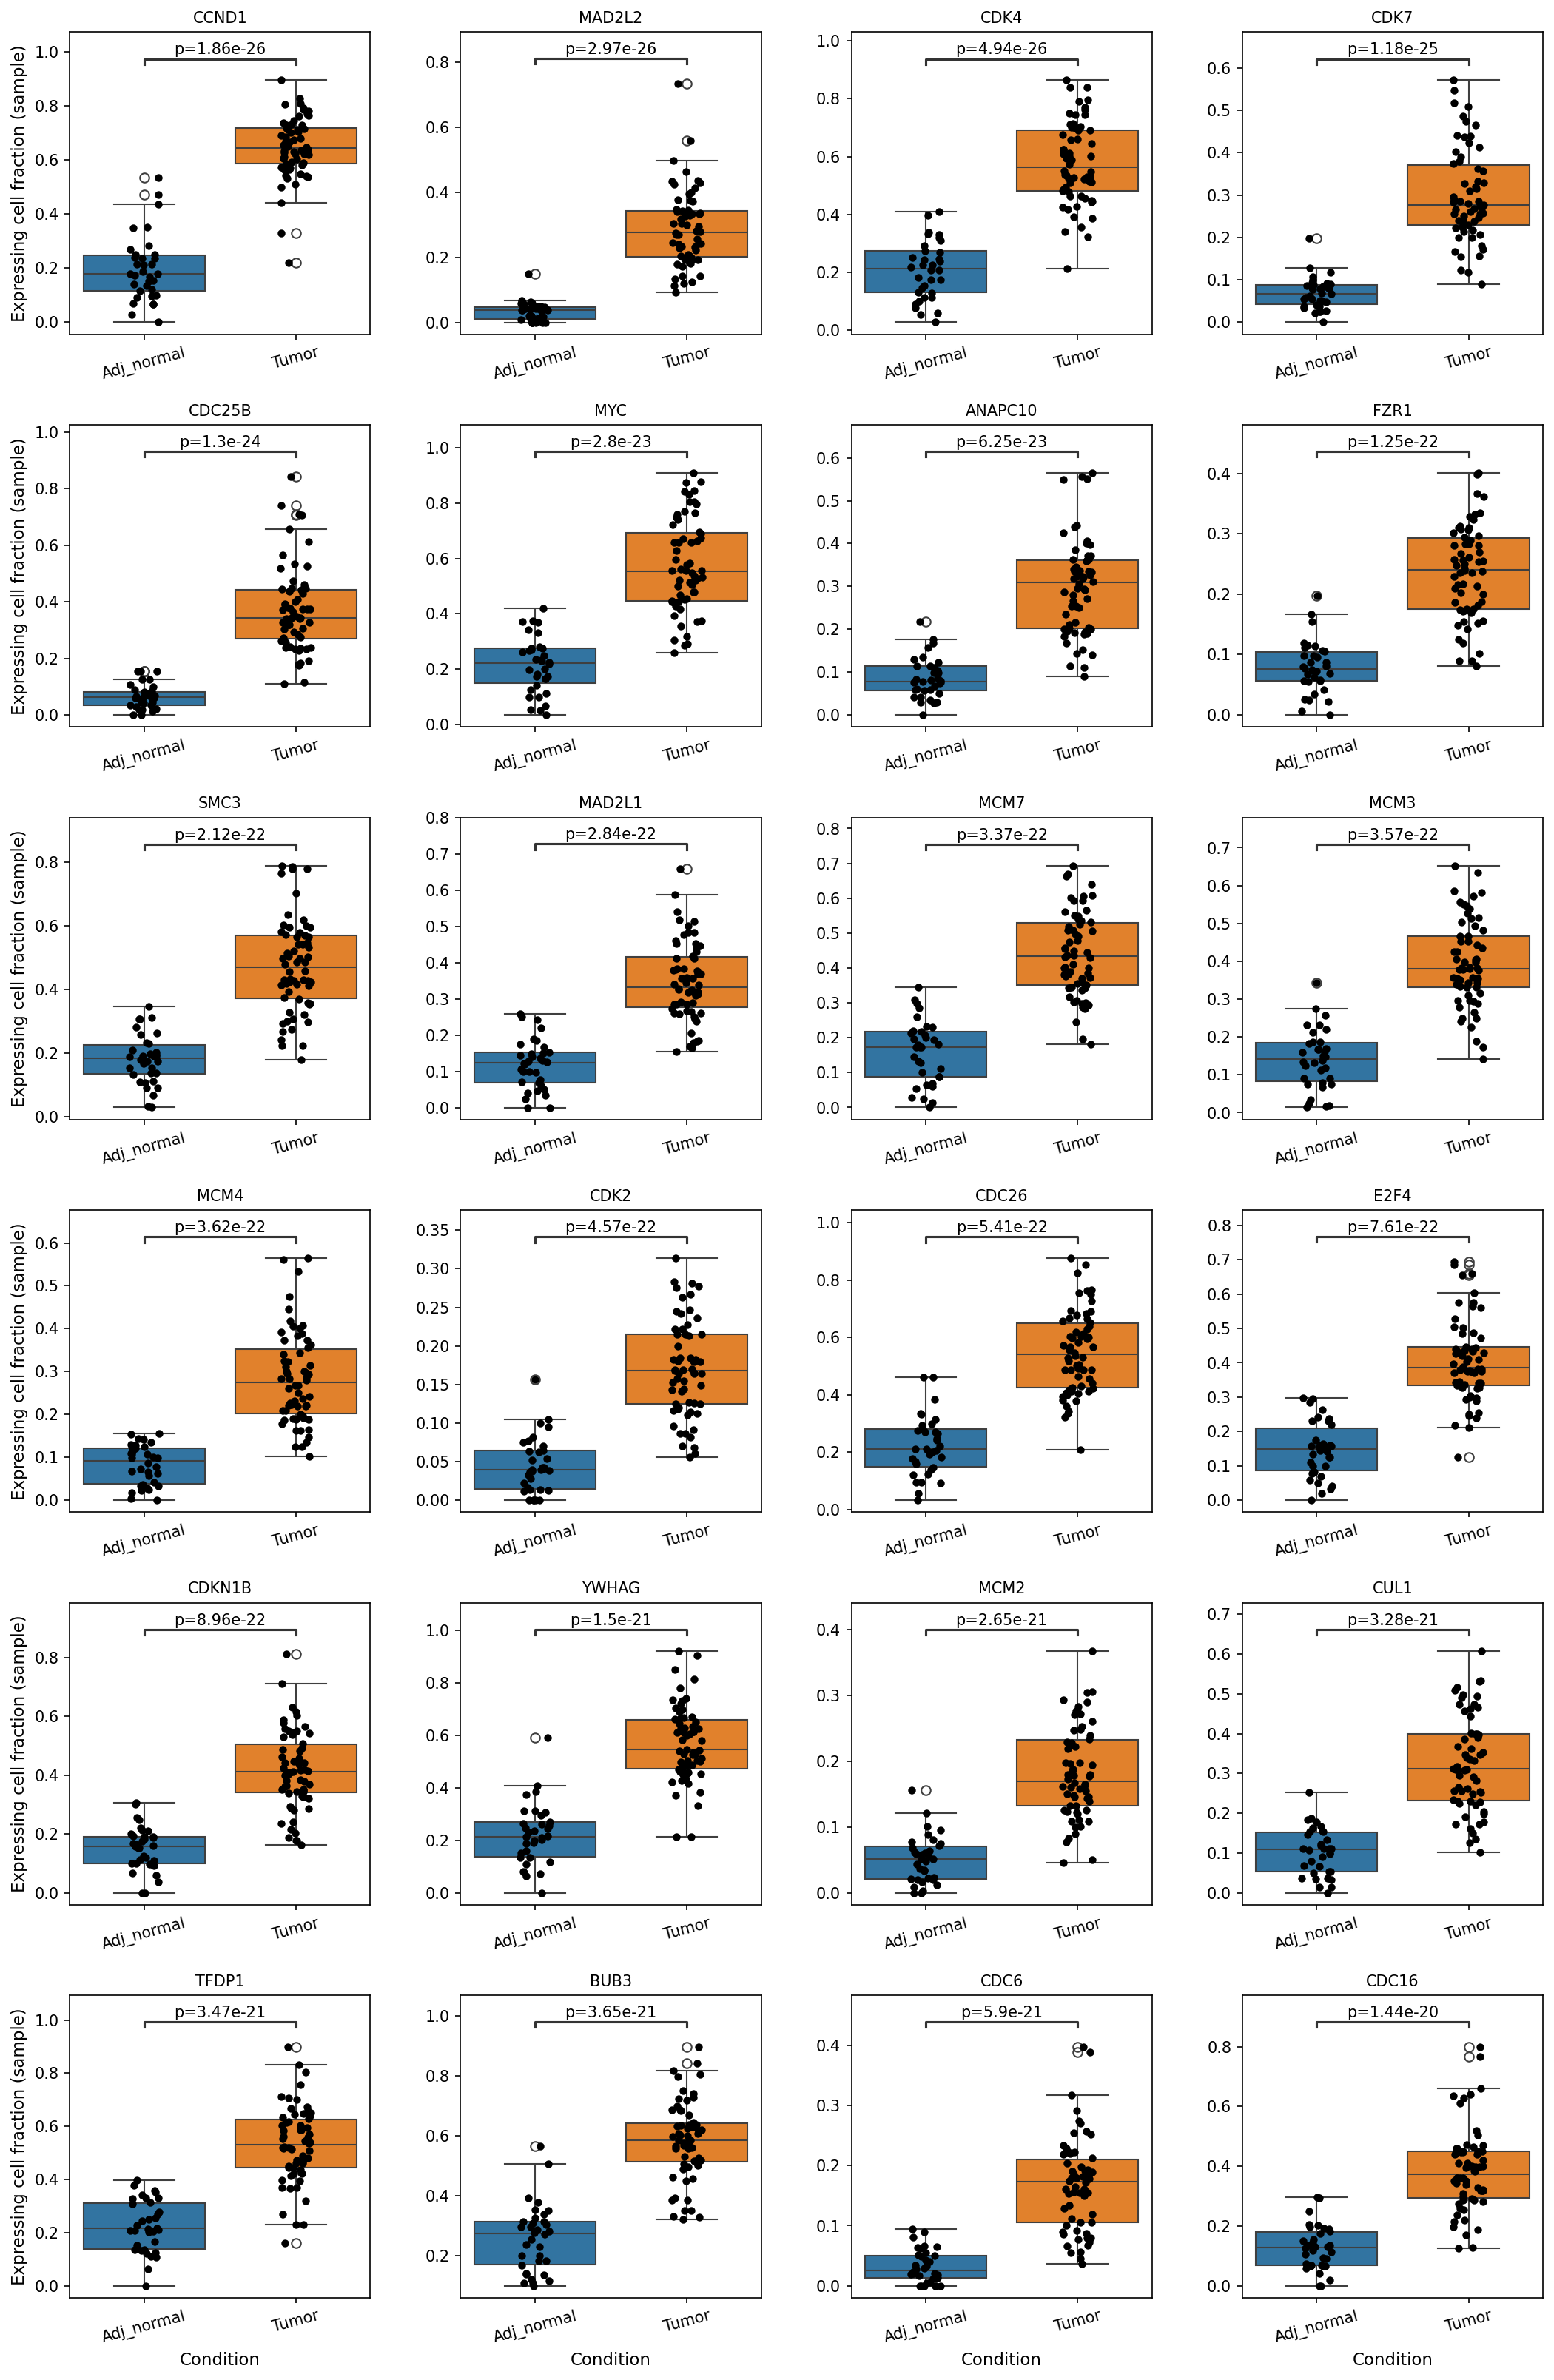
[Analysis Visualization Results]...
Analysis Overview
This analysis investigates the differential expression of a curated set of cell cycle pathway genes within Intestinal Epithelial cells, the identified tumor-origin cell type, comparing cells from colorectal tumor tissue to those from adjacent normal tissue. The aim was to identify genes with statistically significant expression differences between these two conditions, providing insight into the proliferative state of tumor cells. Box plots were generated to visualize the "expressing cell fraction (sample)" for each significant gene, illustrating the proportion of cells within each sample that express a given gene.
Visual Summary
The visualization displays box plots for 24 distinct cell cycle-related genes that exhibit statistically significant differences in their expressing cell fraction between tumor and adjacent normal conditions in Intestinal Epithelial cells.
- Consistent Upregulation in Tumor: A striking and consistent pattern is observed across all plotted genes: the median "expressing cell fraction (sample)" is substantially higher in the "Tumor" condition compared to the "Adj_normal" condition. This indicates that a significantly larger proportion of Intestinal Epithelial cells in tumor samples are actively expressing these cell cycle genes.
- High Statistical Significance: All genes display extremely low p-values (e.g., CCND1 with p=1.86e-26, MAD2L2 with p=2.97e-26, MYC with p=2.8e-23), underscoring the high statistical significance of these observed differences.
- Broad Spectrum of Cell Cycle Regulators: The upregulated genes span various critical components of the cell cycle machinery, including:
- Cyclins and Cyclin-Dependent Kinases (CDKs): CCND1, CDK4, CDK7, CDK2. These are key drivers of cell cycle progression.
- Minichromosome Maintenance (MCM) Complex Genes: MCM2, MCM3, MCM4, MCM7. These are essential for DNA replication initiation.
- Anaphase-Promoting Complex (APC/C) Components: ANAPC10, CDC16, FZR1, CDC26. These regulate mitotic exit.
- Cell Cycle Checkpoint Genes: MAD2L1, MAD2L2, BUB3. These are involved in ensuring proper chromosome segregation during mitosis.
- Transcription Factors and Oncogenes: MYC, E2F4, TFDP1. These regulate the expression of many genes involved in cell growth and proliferation.
- Other Regulators: CDC25B (a phosphatase activating CDKs), SMC3 (a component of the cohesin complex), CDKN1B (p27, a CDK inhibitor). While CDKN1B is an inhibitor, its increased expressing fraction might reflect a dysregulated or overridden feedback loop in tumor cells.
- Magnitude of Change: For many genes, the median expressing cell fraction in tumor samples is 2-4 times higher than in adjacent normal samples, highlighting a profound shift in the proliferative landscape of these cells.
Biological Interpretation
The observed widespread and highly significant upregulation of cell cycle pathway genes in Intestinal Epithelial cells within colorectal tumor samples provides strong biological evidence of increased cellular proliferation, a hallmark of cancer.
- Uncontrolled Proliferation: The Intestinal Epithelial cells are identified as the tumor-origin cells. Their elevated expression of cyclins (CCND1), CDKs (CDK4, CDK2, CDK7), and essential DNA replication initiation factors (MCM2, MCM3, MCM4, MCM7) directly indicates a heightened rate of cell division and DNA synthesis. This uncontrolled proliferation is a fundamental characteristic that distinguishes cancer cells from normal cells.
- Dysregulated Cell Cycle Checkpoints: Genes involved in mitotic checkpoints, such as MAD2L1, MAD2L2, and BUB3, are also significantly upregulated. While these genes typically function to ensure genomic stability, their overexpression in cancer can sometimes indicate an overwhelmed or faulty checkpoint system struggling to cope with rapid and often error-prone cell division, or even contribute to aberrant checkpoint signaling that favors tumor growth.
- Oncogenic Drive: The potent oncogene MYC and the E2F transcription factor family members (E2F4, TFDP1) are critical regulators of cell growth and proliferation. Their upregulation further supports an aggressive, pro-proliferative cellular state in tumor Intestinal Epithelial cells. MYC, in particular, is a well-known driver of cell cycle entry and progression [1].
- Coordinated Cell Cycle Progression: The involvement of components from various phases of the cell cycle (G1/S transition, DNA replication, mitosis) suggests a globally accelerated and deregulated cell cycle program rather than a specific bottleneck. The Anaphase-Promoting Complex (APC/C) components (ANAPC10, FZR1, CDC16, CDC26) are crucial for progression through and exit from mitosis, and their upregulation suggests an active mitotic phase.
Clinical or Translational Implications
These findings have significant implications for understanding colorectal cancer pathogenesis and identifying potential therapeutic strategies.
- Biomarker Potential: The consistently elevated expression of these cell cycle genes in tumor-derived Intestinal Epithelial cells suggests their utility as potential biomarkers for colorectal cancer presence, proliferation rate, or even disease aggressiveness. Monitoring their expression could assist in diagnosis, prognosis, or response to therapy.
- Therapeutic Targets: The identified genes represent a rich landscape of potential therapeutic targets. Inhibiting key cyclins (e.g., CCND1) or CDKs (e.g., CDK4/6 inhibitors are already used in other cancers) could effectively halt the uncontrolled proliferation of colorectal cancer cells [2]. Similarly, targeting components of the DNA replication machinery (MCM proteins) or mitotic regulators could selectively impair tumor growth [3].
- Insights into Drug Resistance: Understanding the specific cell cycle pathways predominantly activated in colorectal cancer could also inform strategies to overcome drug resistance or develop combination therapies that simultaneously target multiple points of cell cycle control.
---
References:
- MYC oncogene function: For an overview of MYC's role in cell growth and proliferation, refer to resources like GeneCards: https://www.genecards.org/cgi-bin/carddisp.pl?gene=MYC
- CDK inhibitors in cancer therapy: PubMed search for "CDK inhibitors cancer therapy": https://pubmed.ncbi.nlm.nih.gov/?term=CDK+inhibitors+cancer+therapy
- MCM proteins as cancer targets: PubMed search for "MCM proteins cancer drug target": https://pubmed.ncbi.nlm.nih.gov/?term=MCM+proteins+cancer+drug+target
20. Gene Ontology (GSA) Analysis of Intestinal Epithelial Cells in Colorectal Cancer
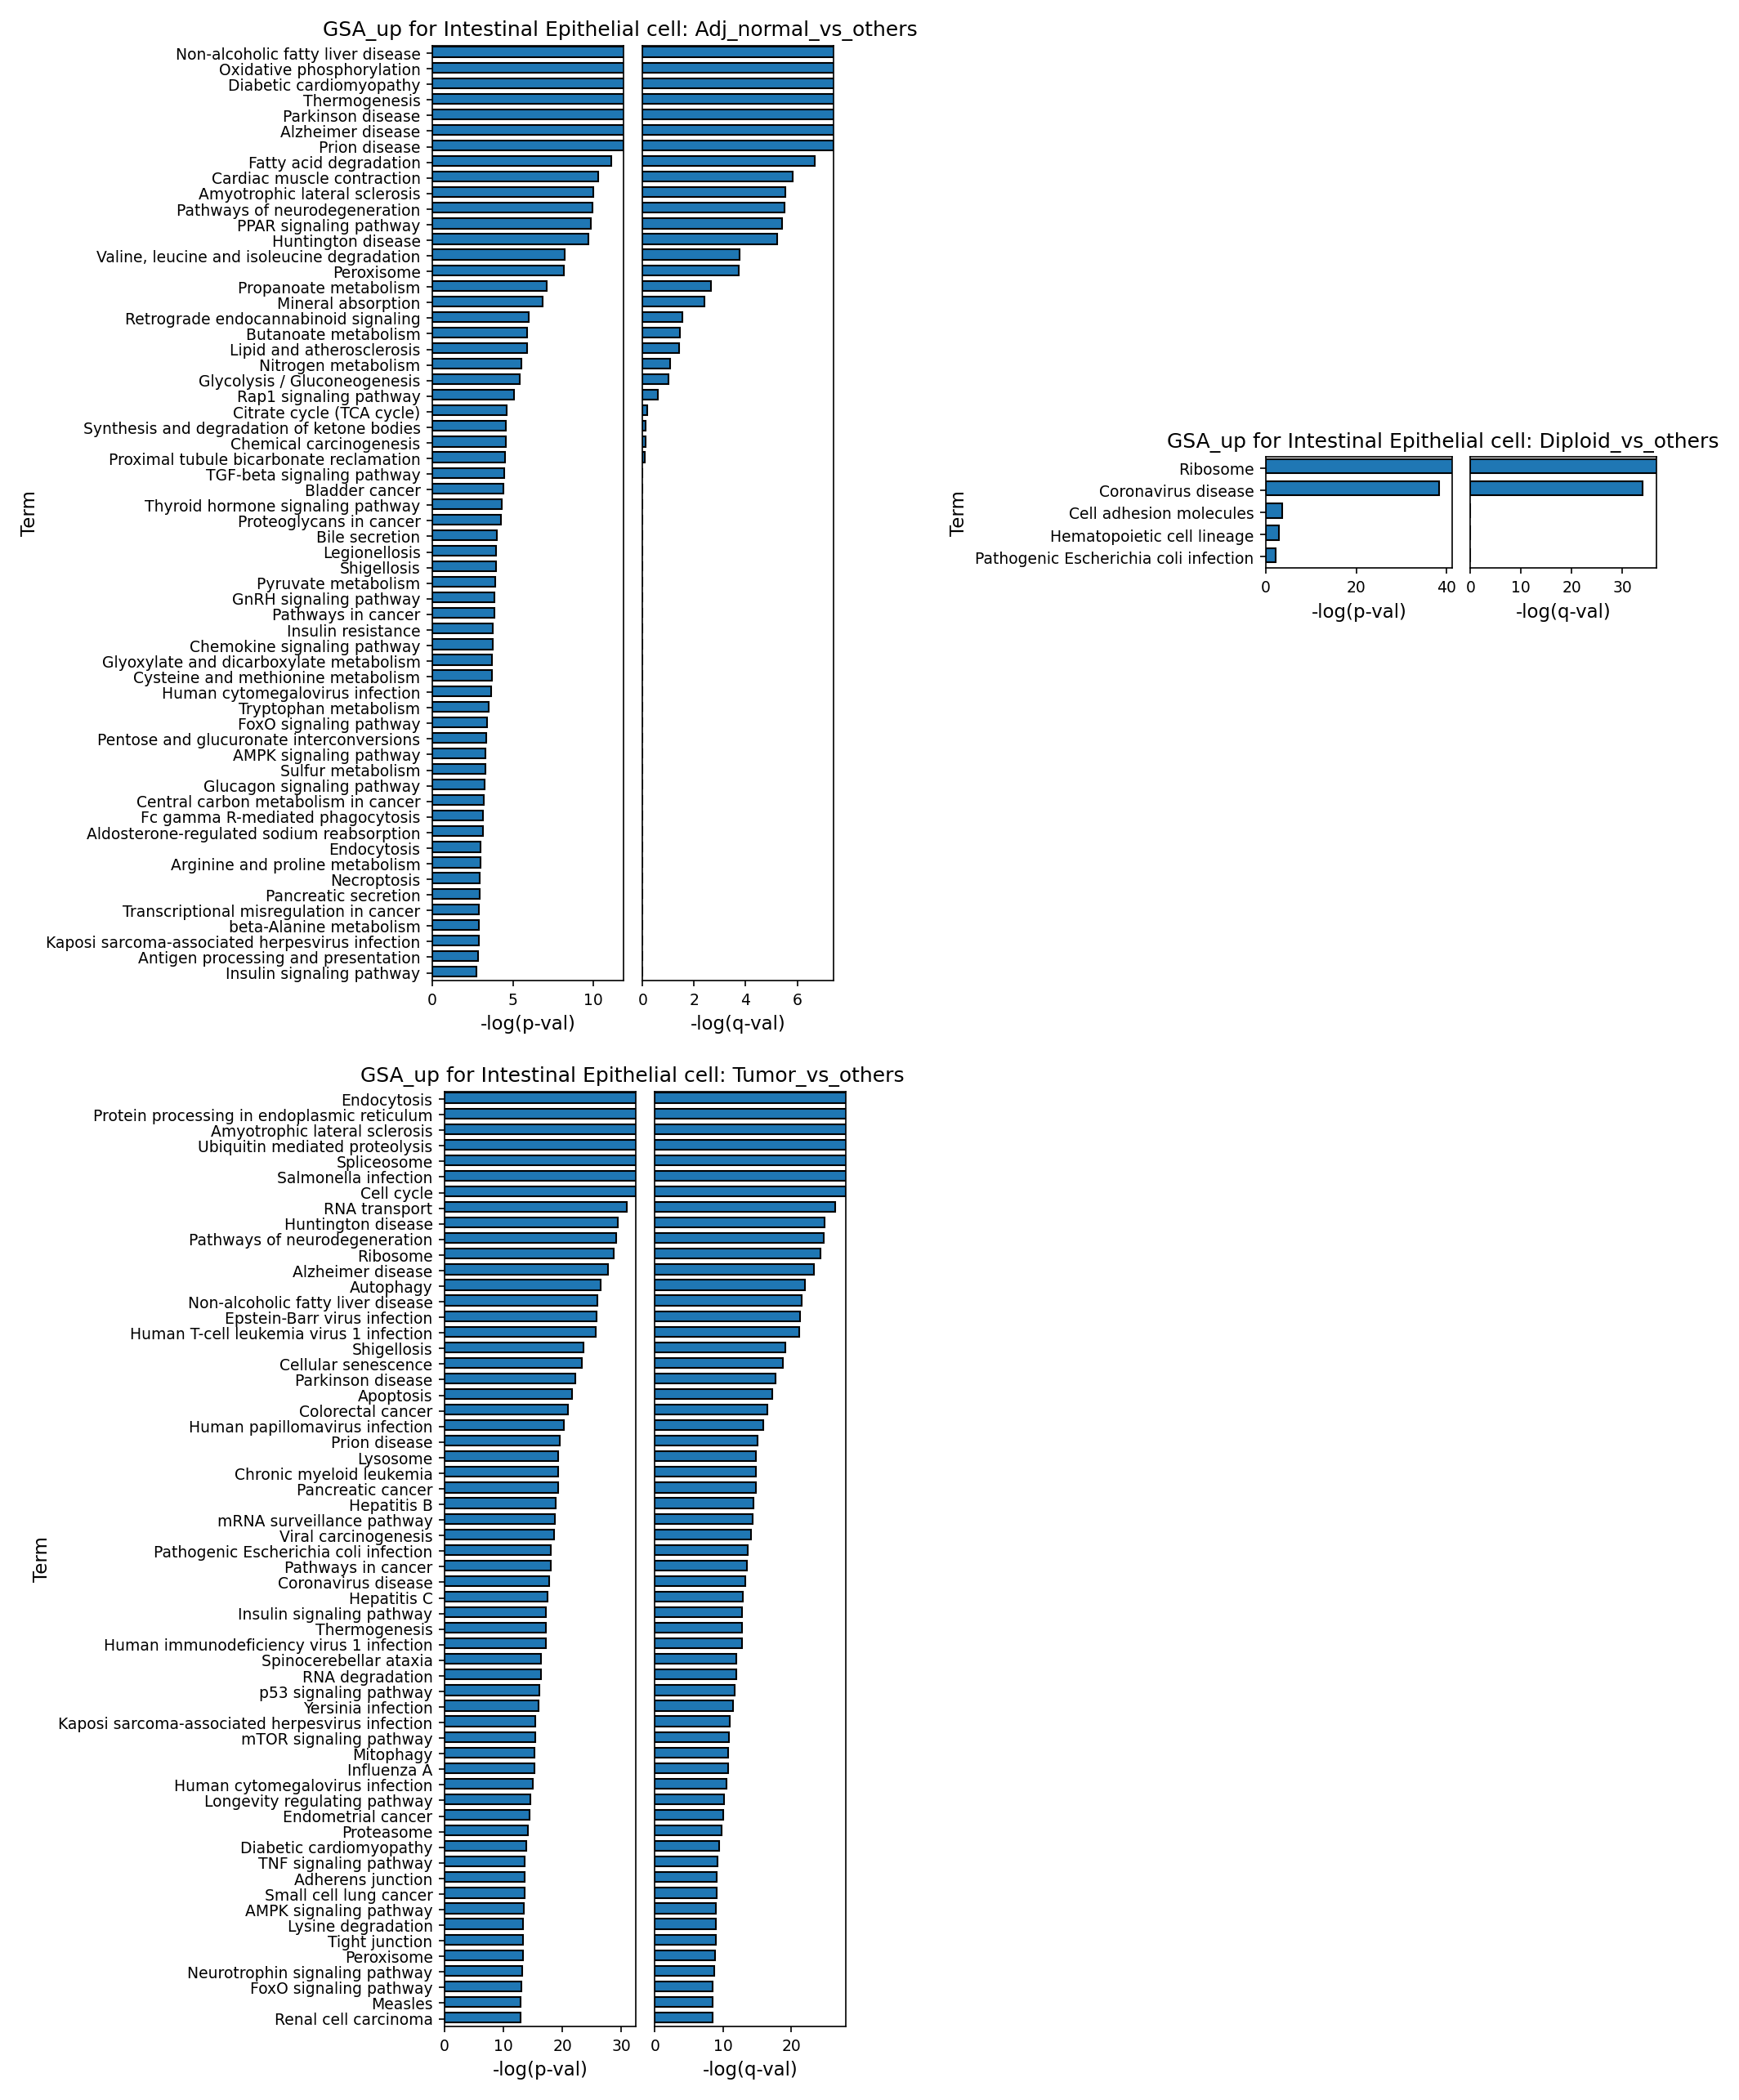
[Analysis Visualization Results]...
Analysis Overview
This analysis presents Gene Ontology (GSA) enrichment results for Intestinal Epithelial cells, a cell type identified as being of tumor origin. The results are visualized as bar plots, displaying significantly enriched pathways/terms (based on -log(p-val) and -log(q-val)) under three different comparison conditions: 'Adj_normal vs others', 'Diploid vs others', and 'Tumor vs others'. These comparisons aim to delineate the distinct biological processes active in normal, non-malignant (diploid), and cancerous (tumor) states of intestinal epithelial cells in the context of colorectal cancer.
Visual Summary
The provided bar plots illustrate the top enriched Gene Ontology terms, ranked by their statistical significance (-log(p-val) and -log(q-val)).
- GSA_up for Intestinal Epithelial cell: Adj_normal_vs_others
- This plot shows pathways upregulated in adjacent normal intestinal epithelial cells compared to other conditions (likely tumor cells of the same type or other cell types).
- Key enriched terms include "Non-alcoholic fatty liver disease," "Oxidative phosphorylation," "Diabetic cardiomyopathy," and various neurodegenerative disease pathways (e.g., "Parkinson's disease," "Alzheimer disease," "Prion disease," "Amyotrophic lateral sclerosis," "Pathways of neurodegeneration").
- Metabolic pathways like "Fatty acid degradation" and "PPAR signaling pathway" are also prominent.
- These terms show high significance, with -log(p-val) exceeding 10 for the top terms and -log(q-val) ranging up to ~7.
- GSA_up for Intestinal Epithelial cell: Diploid_vs_others
- This plot highlights pathways upregulated in diploid Intestinal Epithelial cells (typically non-malignant) when compared to other cell populations (likely including aneuploid cells).
- The most significantly enriched terms are "Ribosome" and "Coronavirus disease," followed by "Cell adhesion molecules," "Hematopoietic cell lineage," and "Pathogenic Escherichia coli infection."
- Significance levels are very high for "Ribosome" and "Coronavirus disease," with -log(p-val) above 30 and -log(q-val) above 30.
- GSA_up for Intestinal Epithelial cell: Tumor_vs_others
- This plot showcases pathways significantly upregulated in tumor-origin Intestinal Epithelial cells compared to other conditions (likely adjacent normal cells of the same type or other cell types).
- A broad array of terms related to fundamental cellular processes and various diseases are enriched. Top terms include "Endocytosis," "Protein processing in endoplasmic reticulum," "Ubiquitin mediated proteolysis," "Cell cycle," "RNA transport," and "Ribosome."
- Crucially, cancer-specific pathways such as "Colorectal cancer," "p53 signaling pathway," "mTOR signaling pathway," "Endometrial cancer," "Pancreatic cancer," and "Renal cell carcinoma" are highly enriched.
- Numerous neurodegenerative disease pathways (e.g., "Amyotrophic lateral sclerosis," "Alzheimer disease," "Parkinson disease," "Huntington disease") also appear, similar to the 'Adj_normal' plot.
- Infection-related pathways (e.g., "Salmonella infection," "Human T-cell leukemia virus 1 infection," "Shigellosis," "Human papillomavirus infection," "Epstein-Barr virus infection," "Hepatitis B," "Coronavirus disease") are also present.
- The significance is very strong, with many terms reaching -log(p-val) values above 20 and -log(q-val) above 15.
Biological Interpretation
The Gene Ontology analysis reveals distinct functional profiles for Intestinal Epithelial cells under different conditions, providing insights into the biology of colorectal cancer.
- Tumor-specific Pathways: The enrichment of "Cell cycle," "Protein processing in endoplasmic reticulum," "Ubiquitin mediated proteolysis," "Endocytosis," and "RNA transport" in tumor-origin Intestinal Epithelial cells reflects fundamental alterations required for uncontrolled proliferation and survival in cancer. Cancer cells typically exhibit high metabolic demands, rapid protein synthesis, increased protein turnover, and dysregulated cellular machinery. The direct enrichment of "Colorectal cancer" and other cancer-related pathways (e.g., p53 signaling, mTOR signaling) strongly validates the neoplastic nature of these cells and points to key drivers of tumorigenesis [PubMed Search: "Colorectal cancer pathways" OR "mTOR signaling cancer" OR "p53 pathway cancer"].
- Adjacent Normal Cell Signatures: The adjacent normal Intestinal Epithelial cells show strong enrichment for "Oxidative phosphorylation" and "Fatty acid degradation," suggesting an active metabolic state associated with energy production in healthy tissues. The consistent presence of "Non-alcoholic fatty liver disease" and several neurodegenerative disease pathways (e.g., "Parkinson's disease", "Alzheimer disease") in both 'Adj_normal' and 'Tumor' comparisons is intriguing. While these are primarily associated with neurological disorders, the underlying cellular mechanisms (e.g., mitochondrial dysfunction, oxidative stress, protein aggregation, inflammatory responses, autophagy) are broadly relevant to cellular stress and disease, including cancer development and progression [PubMed Search: "Mitochondrial dysfunction cancer" OR "Oxidative stress cancer"]. This could indicate shared cellular stress responses or protein quality control pathways that are either maintained in the adjacent normal tissue or become dysregulated during tumorigenesis.
- Diploid Cell Functions: The robust enrichment of "Ribosome" in diploid cells indicates a high capacity for protein synthesis, a hallmark of actively growing and healthy cells. The presence of "Cell adhesion molecules" underscores the importance of maintaining tissue integrity, a characteristic often lost in malignant cells. Enrichment for "Coronavirus disease" and "Pathogenic Escherichia coli infection" might reflect the baseline immune surveillance or inflammatory responses within the intestinal epithelium, which is constantly exposed to pathogens.
- Shared and Divergent Processes: While certain stress-related pathways (e.g., neurodegenerative disease pathways) appear in both adjacent normal and tumor cells, their specific context and functional implications likely differ. Tumor cells hijack and dysregulate these processes for their benefit (e.g., altered autophagy for survival), whereas in normal cells, they likely represent homeostatic or protective mechanisms. The clear distinction in cell cycle regulation and direct cancer pathways highlights the profound transformation from normal to malignant states.
Clinical or Translational Implications
The identified GO terms provide a molecular blueprint of colorectal cancer at the single-cell level, specifically within the tumor-origin Intestinal Epithelial cells.
- Therapeutic Targets: The upregulation of "Cell cycle" and "mTOR signaling pathway" in tumor cells points to established therapeutic targets in oncology. Agents targeting cell proliferation or mTOR activity could be effective. The widespread alterations in "Protein processing in endoplasmic reticulum" and "Ubiquitin mediated proteolysis" also suggest potential vulnerabilities, as these pathways are critical for cancer cell survival and adaptation to stress [UniProt Search: "Ubiquitin-proteasome system cancer"].
- Biomarkers: The distinct metabolic and stress-response signatures of adjacent normal cells could offer insights into pre-cancerous changes or protective mechanisms, potentially leading to novel diagnostic biomarkers or preventative strategies.
- Understanding Tumor Microenvironment: While this analysis focuses on epithelial cells, the enrichment of infection-related pathways (e.g., "Salmonella infection", "Pathogenic Escherichia coli infection") in both tumor and diploid cells suggests the influence of the gut microbiome on epithelial cell states, which is increasingly recognized as a factor in colorectal cancer development and progression [PubMed Search: "Gut microbiome colorectal cancer"].
- Prognostic Value: Understanding the specific pathways dysregulated in aneuploid vs. diploid cells could inform prognostic markers, distinguishing between less aggressive and more aggressive disease subsets.
21. Gene Set Enrichment Analysis Across Cell Types in Colorectal Cancer
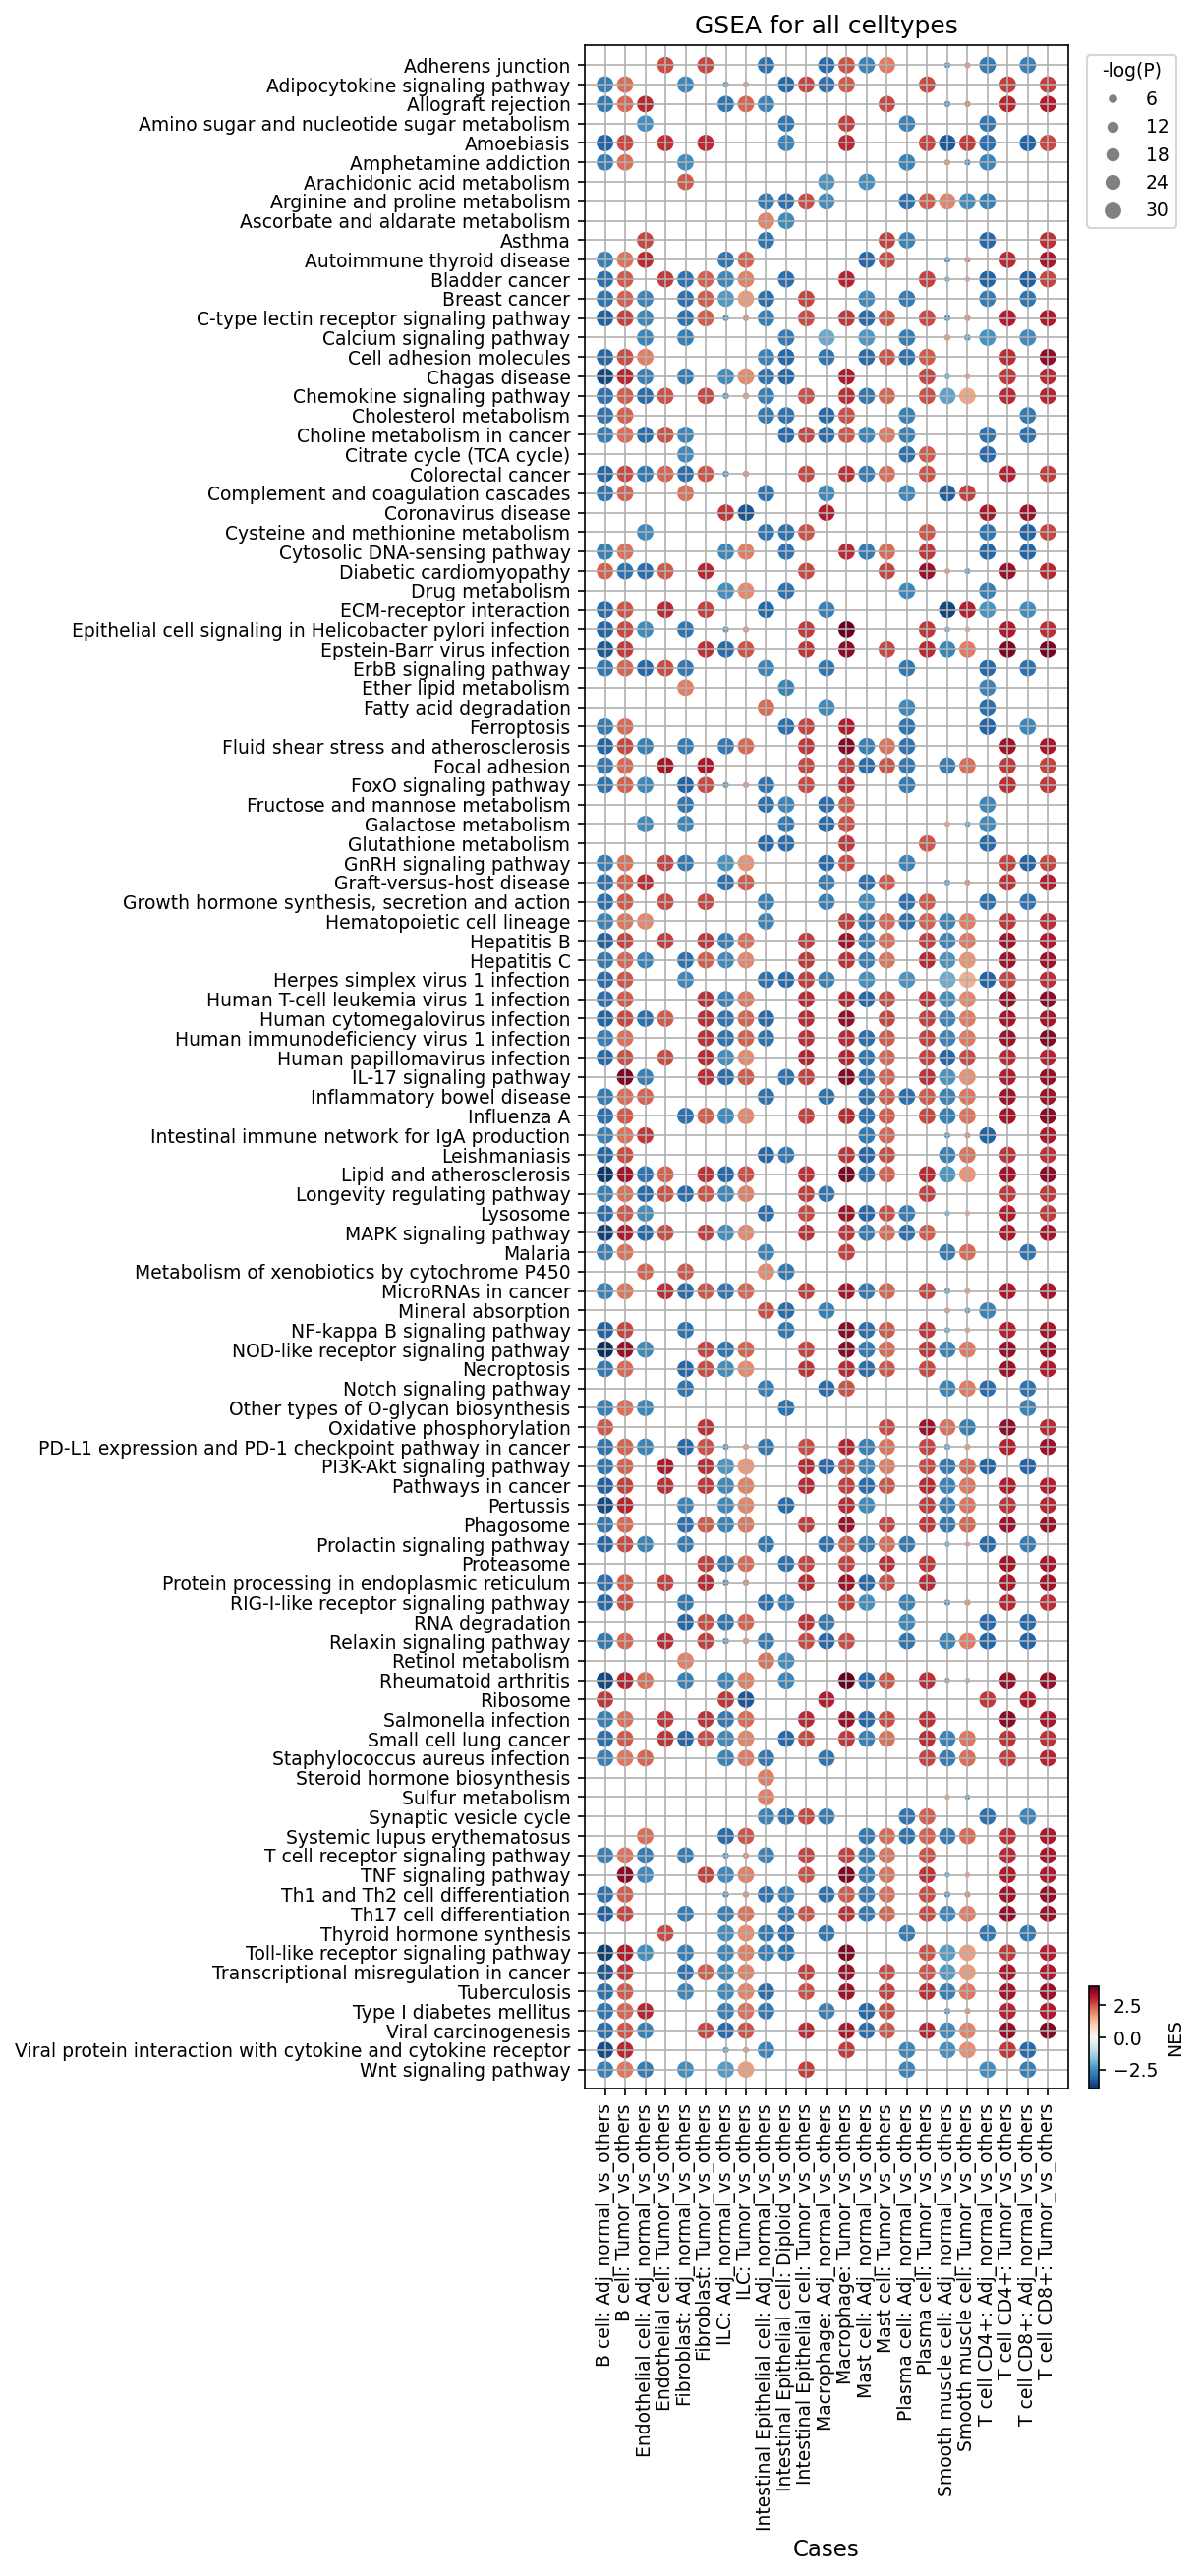
[Analysis Visualization Results]...
Analysis Overview
This analysis presents Gene Set Enrichment Analysis (GSEA) results as a dot plot, illustrating the enrichment of various biological pathways and gene sets across different cell types in colon tissue. The analysis compares gene expression profiles in cells from "Adj_normal" (adjacent normal) samples against all other cells, and "Tumor" samples against all other cells, for each identified celltype_minor (e.g., B cell, Macrophage, Intestinal Epithelial cell). The purpose is to identify differentially regulated biological processes within specific cell populations that characterize the colorectal cancer (CRC) tumor microenvironment compared to the adjacent normal tissue.
Visual Summary
The dot plot visualizes approximately 120 gene sets (y-axis) against various cell type and condition comparisons (x-axis). Each dot represents a specific gene set's enrichment in a given cell type and condition.
- Dot Color (NES): The color gradient, from red to blue, indicates the Normalized Enrichment Score (NES). Red dots (positive NES) signify gene sets that are significantly upregulated or enriched in the 'test' condition (e.g., "Tumor vs. others"). Blue dots (negative NES) indicate gene sets that are downregulated or depleted in the 'test' condition.
- Dot Size (-log(p-val)): The size of each dot is proportional to the -log10(p-value) of the enrichment, with larger dots representing higher statistical significance (smaller p-value).
- Key Patterns:
- A clear distinction in enriched pathways is observed between cells derived from "Adj_normal" and "Tumor" conditions for most cell types.
- Pathways directly linked to cancer, such as "Colorectal cancer", "Pathways in cancer", "Wnt signaling pathway", and "PI3K-Akt signaling pathway", are predominantly and significantly enriched (large red dots) in Intestinal Epithelial cells from the "Tumor" condition.
- Immune cell populations (e.g., Macrophage, T cell CD4+, T cell CD8+) within the tumor microenvironment exhibit unique enrichment patterns related to immune activation, inflammation, and immune evasion mechanisms.
- Metabolic reprogramming is evident, with several metabolic pathways showing differential enrichment across cell types and conditions.
Biological Interpretation
The GSEA results highlight significant shifts in biological processes specific to cell types within colorectal tumor tissue and its adjacent normal counterpart.
Intestinal Epithelial Cells
As the primary cell type of tumor origin, Intestinal Epithelial cells from tumor samples ("Intestinal Epithelial cell: Tumor_vs_others") show robust and significant enrichment (large red dots) for numerous pathways critical in colorectal carcinogenesis:
- Core Cancer Pathways: Strong enrichment of "Colorectal cancer", "Pathways in cancer", "Wnt signaling pathway", "PI3K-Akt signaling pathway", and "ErbB signaling pathway" confirms the dysregulation of fundamental growth, survival, and proliferation pathways characteristic of CRC [GeneCards: WNT signaling pathway].
- Transcriptional & Metabolic Reprogramming: "Transcriptional misregulation in cancer" and "MicroRNAs in cancer" are enriched, indicating broad regulatory changes. Metabolic pathways like "Choline metabolism in cancer", "Amino sugar and nucleotide sugar metabolism", and "Fatty acid degradation" show altered activity, consistent with the metabolic reprogramming (e.g., Warburg effect) frequently observed in cancer cells.
- Cell Adhesion & ECM Interaction: Pathways such as "ECM-receptor interaction", "Focal adhesion", "Cell adhesion molecules", and "Adherens junction" are enriched, reflecting the dynamic changes in cell-extracellular matrix interactions that facilitate tumor invasion and metastasis.
- Immune Evasion: Notably, "PD-L1 expression and PD-1 checkpoint pathway in cancer" shows enrichment in tumor epithelial cells, suggesting their active role in suppressing anti-tumor immune responses [PubMed search: PD-1 PD-L1 colorectal cancer].
Tumor Microenvironment Immune Cells
Immune cells within the tumor milieu display distinct functional states:
- Macrophages ("Macrophage: Tumor_vs_others"): Exhibit significant enrichment in "Phagosome", "Antigen processing and presentation", "Chemokine signaling pathway", "NF-kappa B signaling pathway", and "Toll-like receptor signaling pathway". These patterns are indicative of activated tumor-associated macrophages (TAMs), which often adopt pro-tumorigenic roles, including immune suppression and promoting angiogenesis [PubMed search: tumor associated macrophages colorectal cancer review].
- T Cells ("T cell CD4+: Tumor_vs_others", "T cell CD8+: Tumor_vs_others"): Show enrichment in "T cell receptor signaling pathway", "Chemokine signaling pathway", "TNF signaling pathway", "Th1 and Th2 cell differentiation", and "Th17 cell differentiation". This suggests active T cell responses within the tumor, but the concurrent enrichment of "PD-L1 expression and PD-1 checkpoint pathway in cancer" across T cells and other cell types implies ongoing immune checkpoint engagement, potentially limiting effective anti-tumor immunity.
- B Cells and Plasma Cells ("B cell: Tumor_vs_others", "Plasma cell: Tumor_vs_others"): Demonstrate activation, with B cells showing "B cell receptor signaling pathway" enrichment and Plasma cells exhibiting strong enrichment in "Protein processing in endoplasmic reticulum" and "Ribosome", consistent with active antibody production.
- Mast Cells ("Mast cell: Tumor_vs_others"): Reveal enriched "Fc epsilon RI signaling pathway", "Chemokine signaling pathway", and "Cytokine-cytokine receptor interaction", suggesting active mast cell participation, which can contribute to inflammation and tumor progression in CRC.
Stromal and Endothelial Cells
- Fibroblasts ("Fibroblast: Tumor_vs_others"): Show enrichment in "ECM-receptor interaction", "Focal adhesion", and "Wnt signaling pathway", consistent with the activation of cancer-associated fibroblasts (CAFs) that extensively remodel the tumor extracellular matrix and promote tumor growth and metastasis [PubMed search: cancer-associated fibroblasts colorectal cancer review].
- Endothelial Cells ("Endothelial cell: Tumor_vs_others"): Display enriched "ECM-receptor interaction", "Focal adhesion", and "PI3K-Akt signaling pathway", pointing towards active angiogenesis and altered vascular integrity crucial for tumor supply and dissemination.
Adjacent Normal Tissue
Cells from "Adj_normal_vs_others" generally show distinct or inverse enrichment patterns compared to their tumor counterparts, often lacking enrichment for cancer-promoting pathways and potentially highlighting pathways associated with normal tissue homeostasis.
Clinical or Translational Implications
The comprehensive GSEA results provide several clinically relevant insights for colorectal cancer:
- Targeted Therapies: The significant enrichment of oncogenic pathways like Wnt, PI3K-Akt, and ErbB signaling in tumor epithelial cells reaffirms their roles as critical drivers of CRC. These pathways represent established or emerging targets for specific pathway inhibitors, which could be explored for therapeutic intervention [GeneCards: PIK3CA].
- Immunotherapy Strategies: The widespread enrichment of "PD-L1 expression and PD-1 checkpoint pathway in cancer" across various tumor-associated cells (epithelial, T cells, macrophages) strongly supports the rationale for immune checkpoint blockade therapies in CRC. Understanding the specific cell types engaging this pathway can refine patient selection and combination strategies.
- Biomarker Discovery: Pathways distinctly activated or suppressed in tumor-associated cell types, but not in adjacent normal cells, could yield novel diagnostic or prognostic biomarkers. For example, specific metabolic pathway shifts or immune cell activation profiles could serve as indicators of disease status or treatment response.
- Understanding Disease Heterogeneity: The cell-type-specific pathway dysregulation highlights the complex, heterogeneous nature of the tumor microenvironment in CRC. This understanding is crucial for developing combination therapies that target both cancer cells and their supportive stromal and immune components.
22. Discussion
The integrated single-cell analysis of colorectal cancer tissue and adjacent normal controls reveals a profoundly remodeled tumor microenvironment, driven by distinct molecular and cellular alterations. Aneuploid Intestinal Epithelial cells consistently emerge as the central malignant population, characterized by widespread genomic instability, including recurrent amplifications of oncogenes such such as EGFR, MYC, ERBB2, and highly activated cell cycle pathways (e.g., CCND1, CDK4, MCM genes). Gene Ontology and GSEA further confirm the enrichment of core cancer pathways like Wnt, PI3K-Akt, and ErbB signaling in these tumor cells, alongside significant metabolic reprogramming.
The immune landscape undergoes a dramatic shift. Within the T cell compartment, there is a statistically significant increase in the proportions of immunosuppressive regulatory T cells (Tregs) and pro-inflammatory Th17, Th22, and Th9 cells in tumors, coupled with a reduction in naive T cells. This suggests an orchestrated shift towards an immunosuppressive and potentially pro-tumorigenic T cell environment. Macrophage populations also show a nuanced but significant shift; while Macrophage (M1) cells might still constitute a large proportion, there is a statistically significant increase in pro-tumorigenic Macrophage (M2B) and Macrophage (M2C) subsets, accompanied by a decrease in Macrophage (M1) and Macrophage (M2A) populations in the tumor, highlighting a functional polarization towards tumor-promoting phenotypes. These tumor-associated macrophages (TAMs) are further characterized by a unique surfaceome, with notable upregulation of FOLR2, MMP14, MRC1, TREM2, CD36, SIRPA, and NRP1, indicative of immunosuppressive, pro-angiogenic, and ECM-remodeling functions. Tumor-infiltrating CD4+ T cells also exhibit increased expression of immune checkpoints (CTLA4, TIGIT) and co-stimulatory receptors (TNFRSF18/GITR, ICOS), along with molecules like ENTPD1 (CD39) involved in adenosine-mediated immunosuppression.
Intercellular communication is dramatically reprogrammed in the tumor microenvironment. Extensive cell-cell interactions are observed involving aneuploid Intestinal Epithelial cells, macrophages, and T cells. Key axes include the PVR-TIGIT immune checkpoint, widespread TGF-beta signaling (especially the TGFB1-integrin_avb6_complex), SPP1-CD44, VEGF-VEGFR, and various integrin-mediated interactions. Cancer-associated fibroblasts (CAFs) also acquire a distinct surfaceome (e.g., PMEPA1, IL1R1, ITGA1, SLC2A3), contributing to chronic inflammation, ECM remodeling, and metabolic support for tumor growth. A notable observation is the enrichment of 'neurodegenerative disease' pathways in both adjacent normal and tumor epithelial cells in GSA, which, while not directly cancer-specific, suggests underlying shared cellular stress responses or protein quality control mechanisms that may be perturbed or co-opted in the context of malignancy. These comprehensive findings provide a multi-faceted view of colorectal cancer progression, highlighting the intricate interplay between malignant cells and their supportive stromal and immune compartments, and revealing numerous potential targets for therapeutic intervention.
Hypotheses:
- The observed increase in regulatory T cells (Tregs), Th17, Th22, and Th9 cells, coupled with a decrease in naive T cells, drives an immunosuppressive and pro-inflammatory T cell microenvironment that promotes colorectal cancer progression.
- The proportional increase of Macrophage (M2B) and Macrophage (M2C) subsets in tumors, along with their distinct surfaceome expression (e.g., FOLR2, MRC1, TREM2, CD36, SIRPA, NRP1), indicates a strong pro-tumorigenic and immunosuppressive polarization of tumor-associated macrophages in colorectal cancer.
- Upregulation of the PVR-TIGIT axis and robust TGF-beta signaling between tumor cells and immune/stromal cells are central mechanisms of immune evasion and stromal remodeling that drive colorectal cancer progression.
- The widespread activation of cell cycle pathways (e.g., CCND1, MYC, MCM genes) and recurrent genomic amplifications (EGFR, MYC, ERBB2) in aneuploid Intestinal Epithelial cells are fundamental to the uncontrolled proliferation and genomic instability characteristic of colorectal cancer malignancy.
- Cancer-associated fibroblasts acquire a distinct surfaceome (e.g., PMEPA1, IL1R1, ITGA1, SLC2A3) that actively contributes to ECM remodeling, chronic inflammation, and metabolic support for tumor growth and immune evasion.
Potential therapeutic targets:
- CEACAM5 (Carcinoembryonic Antigen-related Cell Adhesion Molecule 5): CEACAM5 is highly expressed on aneuploid Intestinal Epithelial tumor cells and involved in cell adhesion, signal transduction, and promoting tumor cell proliferation and metastasis. Evidence: Strong upregulation in tumor epithelial cells observed in the marker expression dot plot (Section 15); implicated in prominent homotypic tumor cell interactions (Section 12); established diagnostic and prognostic biomarker for CRC. Validation: Immunohistochemistry (IHC) and immunofluorescence (IF) on primary CRC tissue sections to confirm protein expression and localization. Efficacy testing of CEACAM5-targeted antibody-drug conjugates (ADCs) in patient-derived xenograft or organoid models of CRC.
- CD47-SIRPA Axis: This axis mediates a 'don't eat me' signal, allowing cancer cells to evade phagocytosis by macrophages. CD47 (on tumor cells) and SIRPA (on macrophages) are both significantly upregulated in the tumor microenvironment. Evidence: CD47 is highly expressed on Intestinal Epithelial tumor cells (Section 15), and SIRPA is highly expressed on tumor-associated macrophages (Section 16). This interaction is a well-documented immune evasion mechanism in cancer. Validation: Functional *in vitro* phagocytosis assays using patient-derived tumor cells and macrophages with anti-CD47 or anti-SIRPA antibodies. *In vivo* efficacy studies of anti-CD47 or anti-SIRPA therapies, alone or in combination with other immunotherapies, in CRC animal models.
- TIGIT (on T cells) / PVR (on tumor cells): TIGIT is an inhibitory receptor on T cells that, upon binding to PVR on tumor cells, suppresses T cell activation and effector functions, contributing to immune evasion. Evidence: TIGIT is significantly upregulated in tumor-infiltrating CD4+ T cells (Section 18). The PVR-TIGIT axis is identified as a prominent tumor-immune cell interaction (Section 12), indicating its active role in the immunosuppressive tumor microenvironment. Validation: Evaluate the efficacy of anti-TIGIT monoclonal antibodies, as monotherapy or in combination with other immune checkpoint inhibitors (e.g., anti-PD-1), in preclinical CRC models. Assess T cell proliferation, cytokine production, and tumor regression.
- TGF-beta Signaling Pathway (e.g., via TGFB1, TGFBRs, Integrin αVβ6): TGF-beta is a pleiotropic cytokine that drives immunosuppression, fibrosis, epithelial-mesenchymal transition (EMT), and angiogenesis in the tumor microenvironment, promoting tumor progression. Evidence: Strong TGFB1-TGFBR interactions, particularly the TGFB1-integrin_avb6_complex, are prominently observed between macrophages and aneuploid Intestinal Epithelial cells in the tumor (Section 13). TGFB1-TGFBR3 interactions also occur among endothelial cells (Section 14). Validation: Test the therapeutic potential of TGF-beta signaling inhibitors (e.g., TGF-beta receptor kinase inhibitors or anti-TGF-beta antibodies) or Integrin αVβ6 inhibitors, in combination with immunotherapies, to counteract immunosuppression and fibrosis in CRC models.
- IL1R1 (on Fibroblasts) / IL-1β: IL1R1 is highly expressed on cancer-associated fibroblasts (CAFs) in the tumor, making them responsive to pro-inflammatory IL-1β. This signaling contributes to chronic inflammation, angiogenesis, and immune suppression within the tumor microenvironment. Evidence: IL1R1 is significantly upregulated in tumor fibroblasts compared to adjacent normal fibroblasts (Section 17). IL-1β signaling through IL1R1 is a known driver of pro-tumorigenic inflammation and CAF activation. Validation: Assess the anti-tumor effects of IL-1R antagonists (e.g., Anakinra) or anti-IL-1β antibodies (e.g., Canakinumab) in preclinical CRC models. Monitor their impact on CAF activation, cytokine secretion, and tumor growth, especially in combination with other therapies.
Follow-up validation ideas:
- Quantify and localize T cell subsets (e.g., Tregs, Th17) and macrophage subsets (e.g., M2B, M2C) in primary CRC tissue sections versus adjacent normal tissue using multiplex immunofluorescence or flow cytometry with specific surface markers (e.g., FOXP3, RORγt, FOLR2, MRC1).
- Perform spatial transcriptomics or proteomics to map the precise localization of key immune (Tregs, M2B/C macrophages), stromal (CAFs), and tumor epithelial cell populations, along with their interacting ligand-receptor pairs (e.g., TIGIT, PVR, TGFB1, CEACAM5, CD47), within the tumor microenvironment.
- Conduct *in vitro* co-culture experiments with patient-derived tumor organoids and autologous immune cells, assessing T cell proliferation, cytokine production, and cytotoxicity in the presence or absence of specific immune checkpoint blockade (e.g., anti-TIGIT, anti-CTLA4) or TGF-beta inhibitors.
- Investigate the impact of inhibiting CAF-specific surface markers (e.g., IL1R1, ITGA1, SLC2A3) or their associated signaling (e.g., IL-1β blockade, integrin inhibitors) on CAF activation, ECM production, and their ability to support tumor cell growth/invasion in 3D co-culture models or patient-derived xenografts.
- Utilize CRISPR/shRNA screens in CRC cell lines or organoids to functionally validate the roles of amplified oncogenes (EGFR, MYC, ERBB2) and upregulated cell cycle genes (CCND1, CDK4) in tumor cell proliferation and survival.
- Confirm specific genomic amplifications (e.g., EGFR, MYC, ERBB2) in malignant epithelial cells using fluorescence *in situ* hybridization (FISH) or comparative genomic hybridization (CGH) on tumor tissue sections to assess spatial heterogeneity and validate CNV calls.
Limitations:
This report is based on a single-cell RNA-seq dataset, providing a snapshot of cellular states and interactions at one time point, and may not fully capture dynamic changes over time or in response to therapy. Cell type and CNV inferences rely on computational algorithms and marker gene expression, requiring orthogonal validation. While UMAPs visualize clustering, comprehensive spatial organization within tissues is not fully represented. The observed patient-to-patient heterogeneity necessitates larger cohorts for generalizable findings and the establishment of robust prognostic or predictive biomarkers. All findings represent correlations, and their causal roles in colorectal cancer progression require further experimental validation.
23. Query List
- Show and save UMAPs for condition, sample, major cell type, minor cell type, ploidy_dec, and celltype_subset in two columns.
- Show major cell type scores on UMAP and save the result.
- Show and save a marker expression dot plot for celltype_subset. SET target_cell = None and var_group_rotation = 45. Leave all other arguments at their default values.
- Select Intestinal Epithelial cells (tumor-origin cells), show a CNV heatmap grouped by sample together with a summary of regions with significantly amplified copy numbers, and save the results.
- Show and save UMAPs of CNV patterns colored by major cell type, minor cell type, ploidy results, condition, and sample in two columns.
- Show and save a population bar plot of minor cell types.
- Show and save a population bar plot of T cell subsets.
- Show and save box plots of T cell subset populations with statistically significant differences between conditions, if any. Choose ncols based on the total number of panels.
- Show and save a population bar plot of macrophage subsets.
- Show and save box plots of macrophage subset populations with statistically significant differences between conditions, if any. Choose ncols based on the total number of panels.
- Select Intestinal Epithelial cells (tumor-origin cells), show their ploidy populations as a bar plot, and save the result.
- Show and save cell-cell interaction patterns involving Intestinal Epithelial cells (tumor-origin cells), fibroblasts, macrophages, T cells, and other relevant cell types. Select at most 80 cell-cell interactions per group.
- Select only genes associated with immune checkpoint and cell cycle pathways, show cell-cell interactions for these genes, and save the result.
- Find cell-cell interactions involving major immune and stromal cells that differ significantly between conditions, show them as a dot plot, and save the result. Set max_n_items_per_group to 60. For each interaction identified under each condition, using the provided dataset context, describe the associated signaling pathways and mechanisms, its potential as a therapeutic target, and relevant therapeutic agents.
- Show marker expressions for Intestinal Epithelial cells (tumor-origin cells) in a dot plot, and save the result. Use only surfaceome markers, with at most 60 markers per condition. For the markers identified under each condition, distinguish between established therapeutic targets and less well-characterized markers with potential as therapeutic targets. For each marker, using the provided dataset context, describe the associated signaling pathways and mechanisms, relevant therapeutic agents, and supporting evidence.
- Show marker expressions for macrophages in a dot plot, and save the result. Use only surfaceome markers, with at most 40 markers per condition. For each marker identified under each condition, using the provided dataset context, describe the associated signaling pathways, the role of the corresponding cell type in the tumor microenvironment, the marker’s potential as a therapeutic target, relevant therapeutic agents, and other pertinent information.
- Show marker expressions for fibroblasts in a dot plot, and save the result. Use only surfaceome markers, with at most 40 markers per condition. For each marker identified under each condition, using the provided dataset context, describe the associated signaling pathways, the role of the corresponding cell type in the tumor microenvironment, the marker’s potential as a therapeutic target, relevant therapeutic agents, and other pertinent information.
- Show marker expressions for T cell CD4+ cells in a dot plot, and save the result. Use only surfaceome markers, with at most 40 markers per condition. For each marker identified under each condition, using the provided dataset context, describe the associated signaling pathways, the role of the corresponding cell type in the tumor microenvironment, the marker’s potential as a therapeutic target, relevant therapeutic agents, and other pertinent information.
- Among cell cycle pathway genes, select those with statistically significant expression differences between conditions in Intestinal Epithelial cells (major disease-related cells), show box plots, and save the result. Set max_n_items_to_plot to 24 and choose ncols based on the total number of panels for an an overall width-to-height ratio of approximately 2:3.
- Show and save Gene Ontology (GSA) analysis results for Intestinal Epithelial cells (tumor-origin cells) as a bar plot.
- Show Gene Set Enrichment Analysis results as a dot plot, and save it. Set the color map to RdBu_r, n_pws_to_show to 120, and target_cells to None.